Acromegaly
Clinical Snapshot
Acromegaly is the clinical syndrome of chronic GH and IGF-1 excess in an adult with fused epiphyses. More than 95% of cases are caused by a benign GH-secreting pituitary somatotroph adenoma; GH pulses stimulate hepatic and peripheral IGF-1 production, and it is IGF-1 — not GH itself — that drives most of the syndrome's tissue growth and metabolic effects and that serves as the key biomarker for both diagnosis and ongoing monitoring, since a single random GH level is uninterpretable given GH's pulsatile, minute-to-minute secretion pattern.[1] The same pathophysiology occurring before epiphyseal closure produces gigantism (linear overgrowth) rather than acromegaly — a pediatric distinction covered in Special Populations.
Onset is insidious: facial and acral (hand/foot) changes progress so gradually that patients, families, and even treating clinicians often do not notice them, and diagnosis is typically made 7-10 years after the biological onset of disease — frequently only after a systemic complication (new diabetes, sleep apnea, treatment-resistant hypertension, or an incidental pituitary mass on imaging for another reason) prompts the workup that finally connects the dots. Acromegaly is disease-modifying rather than curable for many patients: transsphenoidal surgery achieves biochemical remission in a majority of microadenomas but a minority of larger or invasive macroadenomas, so a substantial proportion of patients need lifelong medical therapy, and every patient — controlled or not — needs lifelong monitoring for the complications that drive most of the disease's excess morbidity and mortality.[1] The single most useful thing a pharmacist can track at every visit is whether IGF-1 is normalized for the patient's age and sex, since biochemical control is what predicts reduced complication risk and improved life expectancy.
Recognize the Condition
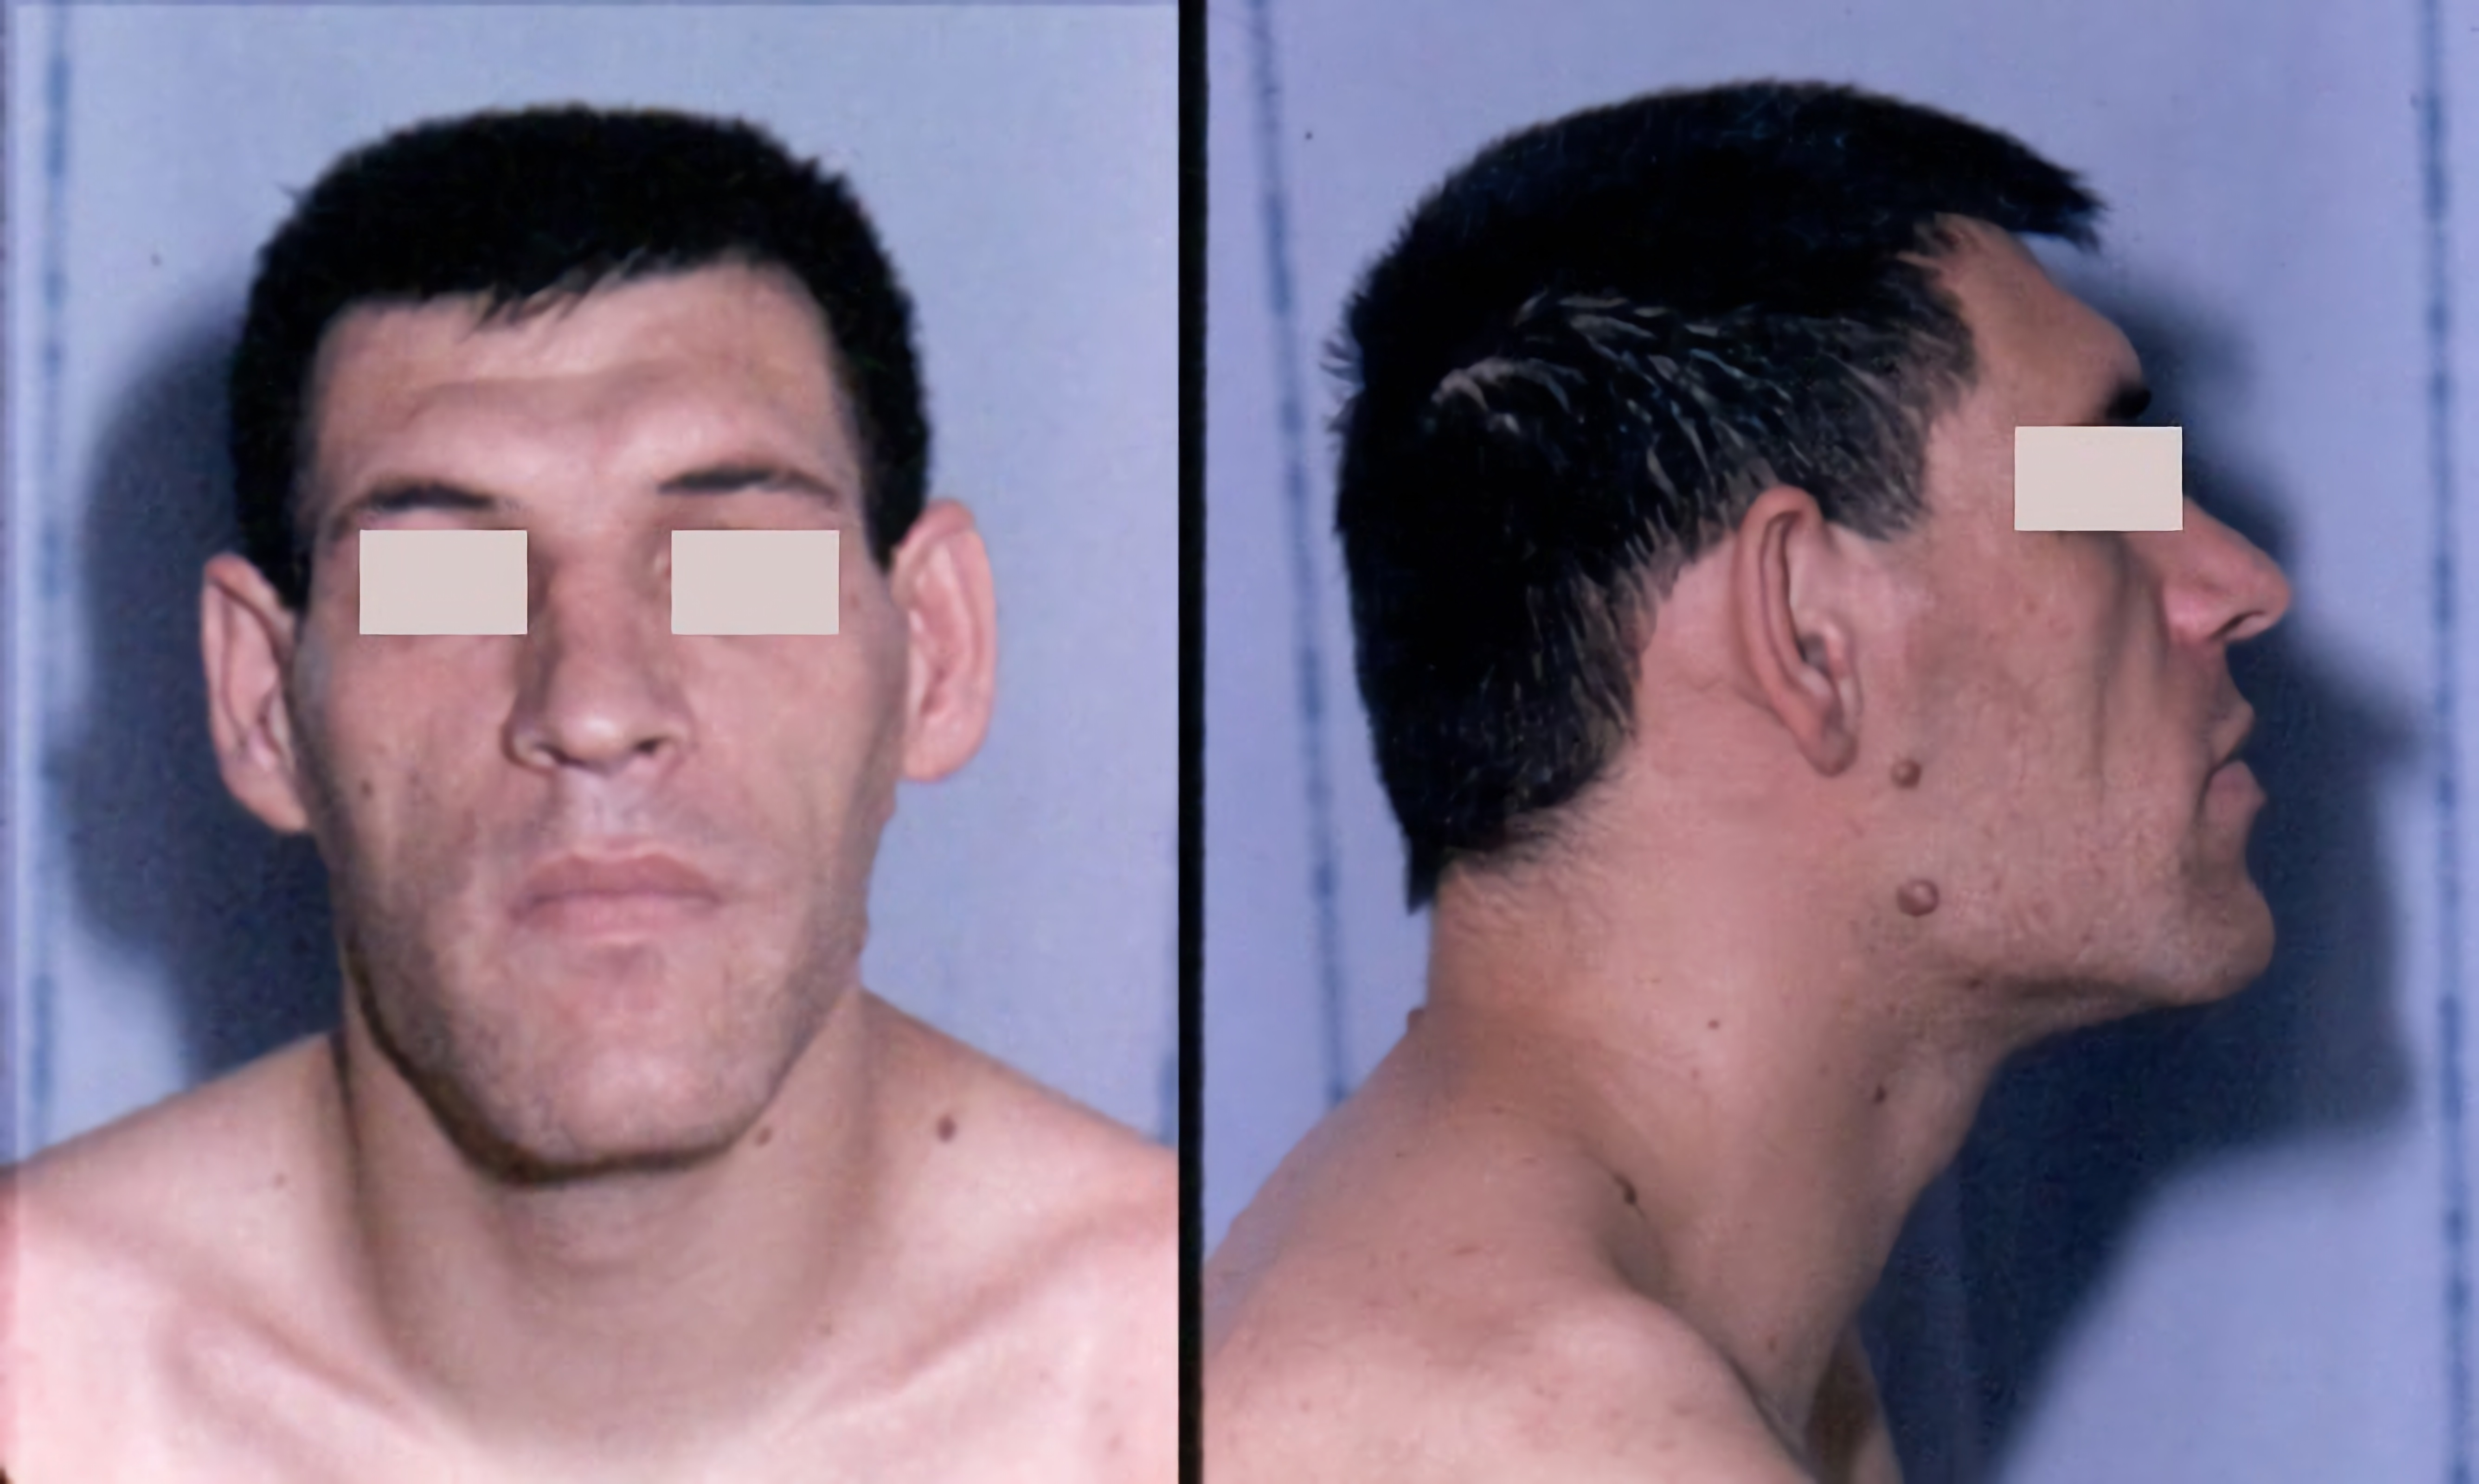
What slowly changes, and what it does systemically
Craniofacial and acral (hand/foot) changes — the visual clue
Frontal bossing (a protruding brow), enlargement of the nose, lips, and tongue (macroglossia), skin thickening and oiliness, widened spacing between the teeth, and prognathism — forward growth of the mandible producing an undershot jaw and malocclusion, often what finally prompts a dental or orthodontic referral that leads to diagnosis. Hands and feet enlarge and thicken (patients often notice their ring or shoe size has increased over several years), and skin tags are common. These changes are best appreciated by comparing old photographs over years, not by a single examination.
Systemic complications — what actually drives morbidity and mortality
Acromegalic cardiomyopathy (biventricular hypertrophy progressing to diastolic and eventually systolic dysfunction if uncontrolled), treatment-resistant hypertension, obstructive sleep apnea from soft-tissue overgrowth of the upper airway and macroglossia (present in more than half of patients), insulin resistance and diabetes, an increased risk of colon polyps and colorectal cancer, degenerative arthropathy from cartilage and soft-tissue overgrowth (which can persist even after biochemical control), carpal tunnel syndrome, goiter and thyroid nodules, and — from the tumor itself — headache, visual field defects from optic chiasm compression, and hypopituitarism from compression of normal pituitary tissue.[2]
Risk Factors
- A sporadic GH-secreting pituitary somatotroph adenoma — the cause in more than 95% of cases, with no identifiable predisposing lifestyle factor.
- Multiple endocrine neoplasia type 1 (MEN1) — pituitary adenoma alongside parathyroid and pancreatic neuroendocrine tumors.
- Familial isolated pituitary adenoma (FIPA), often linked to an AIP gene mutation, particularly when acromegaly presents at a young age or with a family history of pituitary adenoma.
- McCune-Albright syndrome or Carney complex — rare genetic syndromes that can include GH-secreting pituitary disease among their features.
- Extremely rare: ectopic growth-hormone-releasing hormone (GHRH) secretion from a neuroendocrine tumor causing pituitary somatotroph hyperplasia, or, rarer still, ectopic GH secretion from a non-pituitary tumor.[1]
Red Flags & Refer
Refer or escalate urgently for any of the following:
- Pituitary apoplexy — sudden severe headache, visual loss, ophthalmoplegia (double vision from a compressed cranial nerve), or altered consciousness in a patient with a known or suspected pituitary adenoma. This is a neurosurgical and endocrine emergency (acute hemorrhage or infarction of the tumor, with a real risk of acute adrenal insufficiency) — arrange emergency transport immediately, do not wait for a scheduled endocrinology appointment.
- A new visual field defect, classically bitemporal hemianopia from optic chiasm compression, in a patient with a known or newly suspected pituitary mass.
- Symptoms suggesting acute hypopituitarism (fatigue, hypotension, hyponatremia) in a patient with a large tumor or recent pituitary surgery — mass effect or surgery itself can compress or damage normal pituitary tissue.
- Severe, poorly controlled obstructive sleep apnea (witnessed apneas, marked daytime somnolence, or documented hypoxia) — needs prompt sleep medicine assessment given the added cardiovascular risk on top of acromegalic cardiomyopathy.
- Symptoms of decompensated heart failure in a patient with known or suspected acromegalic cardiomyopathy.
Also refer to endocrinology (and neurosurgery, if a pituitary mass is confirmed) for any newly suspected diagnosis — biochemical confirmation, pituitary imaging, and surgical planning should not be managed outside specialist care — as well as for persistent disease after surgery, or any patient being considered for medical therapy escalation or radiotherapy.
Assessment & Diagnosis
Screening test
Measure IGF-1 against an age- and sex-matched reference range — this is the preferred first test. A single random GH level is not useful for screening: GH is secreted in pulses throughout the day and a normal random value does not exclude acromegaly, while a modestly elevated one does not confirm it.[1]
Confirmatory test
An elevated or equivocal IGF-1 in a patient with a compatible clinical picture is confirmed with a 75 g oral glucose tolerance test (OGTT), measuring GH at baseline and every 30 minutes for 2 hours. Failure of GH to suppress below the assay-specific cutoff (commonly under 1 ng/mL, or under 0.4 ng/mL with newer ultrasensitive assays) confirms the diagnosis. A normal suppression response effectively excludes acromegaly in a patient not already on somatostatin analog therapy (which itself can blunt the OGTT response and make the test unreliable).[1]
After biochemical confirmation
- Pituitary MRI with contrast to localize and characterize the adenoma (size, cavernous sinus invasion, proximity to the optic chiasm) and guide surgical planning.
- Formal visual field testing for any tumor abutting or compressing the optic chiasm.
- A full pituitary hormone panel (prolactin, TSH/free T4, LH/FSH with testosterone or estradiol, morning cortisol or ACTH stimulation testing as indicated) — to identify prolactin co-secretion (common, since somatotroph and lactotroph cells share a lineage) and any coexisting hypopituitarism from mass effect.
- Baseline complication screening — echocardiogram, a sleep study if symptoms suggest sleep apnea, fasting glucose/HbA1c, and colonoscopy — since these findings shape both the urgency of treatment and the long-term monitoring plan (see Monitoring & Follow-Up).[2]
Treatment Targets
- Normalize IGF-1 for the patient's age and sex — the primary biochemical control target.[3]
- Achieve a GH nadir under 1 ng/mL on OGTT where the test remains interpretable (not a valid marker in a patient on pegvisomant — see Special Populations/Common Errors).
- Control or reverse mass effect — relieve visual field compromise, resolve headache, and preserve or restore normal pituitary function.
- Prevent, detect early, or manage the systemic complications: cardiomyopathy, hypertension, sleep apnea, diabetes, colon polyps, and arthropathy.
- Avoid iatrogenic hypopituitarism from treatment itself (surgery or radiotherapy), and replace any hormone deficiency promptly when it occurs.
- Restore quality of life and reduce the excess mortality risk associated with sustained, uncontrolled disease.
Choose Initial Treatment
Surgery first, for essentially all surgically accessible tumors
1st line Transsphenoidal resection by an experienced pituitary neurosurgeon is first-line treatment for microadenomas and non-invasive macroadenomas — it is the only treatment that can produce a durable biochemical cure, and it is also the fastest way to relieve mass effect (visual field compromise, headache).[1]
Alternative / adjunct For large or cavernous-sinus-invasive macroadenomas, a poor surgical candidate, or a patient who declines surgery, start a first-generation somatostatin analog (octreotide LAR or lanreotide) as primary medical therapy. Pre-operative medical cytoreduction to shrink a very large tumor or improve cardiopulmonary status before anesthesia can be considered for select high-risk patients, though it is not a routine step for most patients and should not delay surgery when surgery is otherwise appropriate.[4]
Special situation Reassess IGF-1 approximately 12 weeks after surgery. Persistent biochemical disease is common after large or invasive tumors and moves the patient to the medical therapy escalation pathway in the Clinical Decision Algorithm rather than being treated as a surgical failure requiring immediate reoperation in most cases.
Non-Pharmacologic Treatment
- Endoscopic transsphenoidal surgery — outcomes are strongly volume-dependent; referral to a high-volume pituitary surgical center meaningfully improves remission rates and lowers complication risk compared with an occasional pituitary operator.[1]
- Stereotactic radiosurgery (preferred over conventional fractionated radiotherapy where the tumor geometry allows) for residual or recurrent disease not controlled by surgery plus optimized medical therapy. Its GH/IGF-1-lowering effect is delayed, often by several years, so medical therapy is continued during this interval, and lifelong monitoring for radiotherapy-induced hypopituitarism is required even after the tumor itself is controlled.[1]
- Continuous positive airway pressure (CPAP) for confirmed obstructive sleep apnea — treat this in parallel with definitive GH/IGF-1-lowering therapy, not instead of it, since airway soft-tissue overgrowth may only partially reverse with biochemical control.
- Coordinated, multidisciplinary follow-up (endocrinology, neurosurgery, cardiology, sleep medicine, and dentistry/orthodontics as needed) — this is a lifelong-monitoring condition even in patients who achieve biochemical remission.
- Patient education on the rationale for lifelong complication screening, since many of the downstream risks (cardiac, colonic, metabolic) are asymptomatic until advanced.
Special Populations
Pregnancy
Acromegaly in pregnancy is uncommon, and monitoring is genuinely different: the placenta produces its own GH variant (placental GH-V), and IGF-1 rises physiologically through pregnancy, so IGF-1 and GH are not reliable disease markers during pregnancy — follow the patient clinically (symptoms, visual fields for a large tumor) rather than by biochemistry. Medical therapy is generally held during pregnancy given limited safety data for somatostatin analogs and pegvisomant in this setting, unless tumor mass effect genuinely requires ongoing treatment; among the available options, cabergoline has the most reassuring human pregnancy safety experience (from its much larger prolactinoma-in-pregnancy dataset) and may be preferred if treatment cannot be safely paused. Involve maternal-fetal medicine and endocrinology jointly.[1]
Pediatrics
GH excess before epiphyseal fusion produces gigantism — linear overgrowth in height, in addition to the same soft-tissue and organ changes seen in adults — rather than isolated acromegaly. The underlying pathophysiology, diagnostic approach (IGF-1 screening, OGTT confirmation using pediatric reference ranges, pituitary MRI), and surgery-first treatment sequence are the same as in adults.
Older adults
Baseline cardiovascular and metabolic comorbidity burden is typically higher, making complete cardiac and sleep apnea workup before surgery more consequential, not less — do not skip baseline echocardiography or sleep screening in an older patient because comorbidities seem to already explain the symptoms.
Hepatic and renal considerations
Pegvisomant carries a real hepatotoxicity risk and needs more frequent liver enzyme monitoring, particularly during the first 6 months and after any dose increase; avoid it in a patient with significant active hepatic impairment. Somatostatin analogs do not require routine dose adjustment for renal impairment but should still be used with the same monitoring as in any patient.
Drug interactions
Somatostatin analogs (octreotide, lanreotide, pasireotide) suppress insulin and glucagon secretion and can cause either hyperglycemia or hypoglycemia — anticipate the need to adjust diabetes medications, more so with pasireotide. They also slow gallbladder motility and increase cholelithiasis risk (periodic ultrasound if symptomatic), and can cause bradycardia — use added caution with concurrent beta-blockers or other bradycardia-inducing drugs. Pegvisomant improves insulin sensitivity as GH excess resolves, often requiring a reduction in insulin or sulfonylurea dose to avoid hypoglycemia. Cabergoline should not be combined with other ergot-derived medications, and its efficacy is reduced by concurrent dopamine-antagonist drugs (e.g., some antipsychotics, metoclopramide).
Monitoring & Follow-Up
- IGF-1 approximately every 12 weeks during medical therapy initiation or dose titration, then every 6-12 months once the patient is stable and biochemically controlled.[3]
- Pituitary MRI — first around 12 weeks after surgery, then per residual-tumor risk; continue periodic MRI in any patient on pegvisomant even once IGF-1 is normalized, since pegvisomant has no direct anti-tumor effect and biochemistry alone will not detect tumor regrowth.
- Echocardiogram at baseline and as clinically indicated; more frequent monitoring is reasonable in a patient on higher-dose cabergoline given the valvulopathy risk at acromegaly-level dosing.
- Sleep apnea screening/re-screening based on symptoms, since airway soft-tissue changes may only partially reverse with biochemical control.
- Fasting glucose or HbA1c at baseline and periodically, with closer monitoring in a patient on pasireotide given its materially higher hyperglycemia risk.
- Colonoscopy at diagnosis (particularly age 40 and over) with repeat interval individualized to findings and ongoing biochemical control — more frequent surveillance for a patient with prior polyps or persistently uncontrolled disease.[2]
- Annual visual field testing for any patient with a history of chiasmal involvement.
- Liver enzymes for a patient on pegvisomant — baseline, then periodically (more frequently in the first 6 months and after any dose increase).
- Periodic full pituitary function panel to detect treatment- or tumor-related hypopituitarism, with prompt hydrocortisone, levothyroxine, or sex hormone replacement as needed.
- Ongoing assessment of joint symptoms — acromegalic arthropathy can persist and progress even after the underlying GH/IGF-1 excess is controlled.
Common Errors to Avoid
- Relying on a single random GH level to screen for or rule out acromegaly — GH's pulsatile secretion makes this uninterpretable; use IGF-1 first.
- Using GH to monitor treatment response in a patient on pegvisomant — it blocks the GH receptor rather than lowering GH secretion, so GH levels are not a valid marker on this drug; use IGF-1.
- Assuming a normalized IGF-1 on pegvisomant means the tumor itself is controlled — it has no direct anti-tumor effect, so periodic MRI is still required.
- Not screening for complications (cardiac, sleep apnea, glucose, colon) at diagnosis and assuming they will simply resolve once GH/IGF-1 is controlled — some, particularly arthropathy, can persist regardless.
- Treating an isolated elevated IGF-1 or GH found incidentally without confirmatory OGTT and clinical correlation.
- Declaring somatostatin analog therapy a failure before the dose has actually been titrated to its effective range over an adequate trial period (about 3 months).
- Missing pituitary apoplexy or acute hypopituitarism as an emergency in a patient with a known pituitary adenoma who develops sudden headache, visual change, or hypotension.
- Overlooking cabergoline's valvulopathy risk at the higher doses used in acromegaly (compared with typical prolactinoma dosing) and skipping baseline/periodic echocardiography.
- Not considering combination medical therapy (SSA plus pegvisomant, or plus cabergoline) before escalating straight to radiotherapy.
- Interpreting IGF-1 and GH by adult reference ranges in a pregnant patient — both rise physiologically in pregnancy and are not reliable disease markers in that setting.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation. Select any linked drug name to open its complete Pharmasist Drug Database page.
Somatostatin analogs — first generation (1st-line medical therapy)
Both agents are equally reasonable first choices; selection often comes down to injection preference and local administration logistics.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Octreotide | Short-acting, subcutaneous: 50-100 mcg SC 2-3 times daily initially, titrated to effect (up to 500 mcg/dose) Long-acting release (LAR) depot: 20 mg IM (deep gluteal) every 4 weeks; after about 3 months, titrate to 10-30 mg q4wk based on IGF-1 | GI upset (usually transient), cholelithiasis with long-term use, hyperglycemia or hypoglycemia, bradycardia, local injection-site reactions. | Additive bradycardia with beta-blockers or other bradycardia-inducing drugs; can alter insulin/oral hypoglycemic requirements; may reduce cyclosporine absorption. | The short-acting subcutaneous formulation can bridge initial titration or manage breakthrough symptoms; the LAR depot requires clinician reconstitution and administration and is not for patient self-injection. |
| Lanreotide | Extended-release depot, subcutaneous: 90 mg deep SC every 4 weeks; titrate 60-120 mg based on IGF-1 response | Same class effects as octreotide: GI upset, cholelithiasis, glycemic changes, bradycardia, injection-site nodules. | Same as octreotide. | The extended-release gel formulation can be self-administered by the patient or a trained caregiver, unlike octreotide LAR. The dosing interval can often be extended to every 6-8 weeks once the patient is well controlled. |
Somatostatin analog — second generation / multireceptor (SSA-resistant disease)
Reserve for disease genuinely resistant to an optimized trial of a first-generation SSA, given its materially higher hyperglycemia risk.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Pasireotide | Long-acting depot, intramuscular: 40 mg IM every 4 weeks; titrate 20-60 mg based on IGF-1 response | New or worsening hyperglycemia/diabetes is substantially more common than with first-generation SSAs (this is the dose-limiting adverse effect), plus the same class effects as octreotide/lanreotide. | Same bradycardia and glycemic-control interactions as octreotide/lanreotide, with a materially higher net effect on glucose. | Check HbA1c before starting and monitor glucose closely after any switch to or dose increase of this agent; anticipate the need to start or intensify diabetes therapy. |
Growth hormone receptor antagonist
Blocks the GH receptor rather than lowering GH secretion — GH levels are not a valid marker of response on this drug; use IGF-1 only.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Pegvisomant | Loading dose: 40 mg SC once Maintenance: 10 mg SC once daily; titrate by 5 mg increments every 4-6 weeks based on IGF-1, to a usual maximum of 30 mg/day | Hepatotoxicity (transaminase elevation) — the main safety concern requiring monitoring; injection-site lipohypertrophy with long-term use. | Improves insulin sensitivity as GH excess resolves — insulin or sulfonylurea doses often need reducing to avoid hypoglycemia. | No direct anti-tumor effect — continue periodic pituitary MRI even when IGF-1 normalizes. Baseline liver enzymes, then periodically (more frequently in the first 6 months and after any dose increase). |
Dopamine agonists
The least effective medical option used alone; most useful for mild residual IGF-1 elevation, prolactin co-secretion, or as an add-on to a somatostatin analog or pegvisomant.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Cabergoline | Adults: 0.5 mg PO 1-2 times weekly initially; titrate up to 1-3 mg/week (occasionally higher) based on IGF-1 response | Nausea, orthostatic hypotension, impulse control disorders (compulsive gambling, hypersexuality) with long-term use, and cardiac valvulopathy at the higher cumulative doses used in acromegaly. | Avoid combining with other ergot-derived drugs; efficacy is reduced by concurrent dopamine-antagonist drugs (e.g., some antipsychotics, metoclopramide). | Baseline and periodic echocardiogram given the higher doses used in acromegaly compared with typical prolactinoma dosing. |
| Bromocriptine | Adults: 1.25-2.5 mg PO daily initially, titrated as needed and tolerated | Nausea, orthostatic hypotension, and impulse control disorders; generally less well tolerated than cabergoline. | Avoid combining with other ergot-derived drugs; efficacy is reduced by concurrent dopamine-antagonist drugs. | An older, less potent dopamine agonist option now used less often than cabergoline given its less convenient dosing schedule and lower efficacy in acromegaly. |
Combination medical therapy
A reasonable escalation option before moving to radiotherapy — see Clinical Decision Algorithm, Algorithm C.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Somatostatin analog + pegvisomant (combination) | octreotide LAR or lanreotide, dose per monotherapy table + pegvisomant, dose per monotherapy table (often at a lower maintenance dose than pegvisomant monotherapy) | Combined adverse-effect profile of both components — monitor for both hepatotoxicity (pegvisomant) and glycemic/gallbladder effects (SSA). | As per each individual component above. | Used for inadequate response to an optimized SSA dose alone; IGF-1 remains the marker followed, since GH is not interpretable once pegvisomant is on board. |
References
- Acromegaly: An Endocrine Society Clinical Practice Guideline — The Journal of Clinical Endocrinology & Metabolism, Endocrine Society (Katznelson L, Laws ER Jr, Melmed S, Molitch ME, Murad MH, Utz A, Wass JAH). J Clin Endocrinol Metab 2014;99(11):3933-3951
- A Consensus on the Diagnosis and Treatment of Acromegaly Complications — Pituitary, Acromegaly Consensus Group (Melmed S, Casanueva FF, Klibanski A, Bronstein MD, Chanson P, Lamberts SW, Strasburger CJ, Wass JAH, Giustina A). Pituitary 2013;16(3):294-302
- Consensus on Criteria for Acromegaly Diagnosis and Remission — Pituitary (Giustina A, Biermasz N, Casanueva FF, et al.). Pituitary 2024;27(1):7-22
- A Pituitary Society Update to Acromegaly Management Guidelines — Pituitary (Fleseriu M, Biller BMK, Freda PU, et al.). Pituitary 2021;24(1):1-13
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.