Allergic Conjunctivitis
Clinical Snapshot
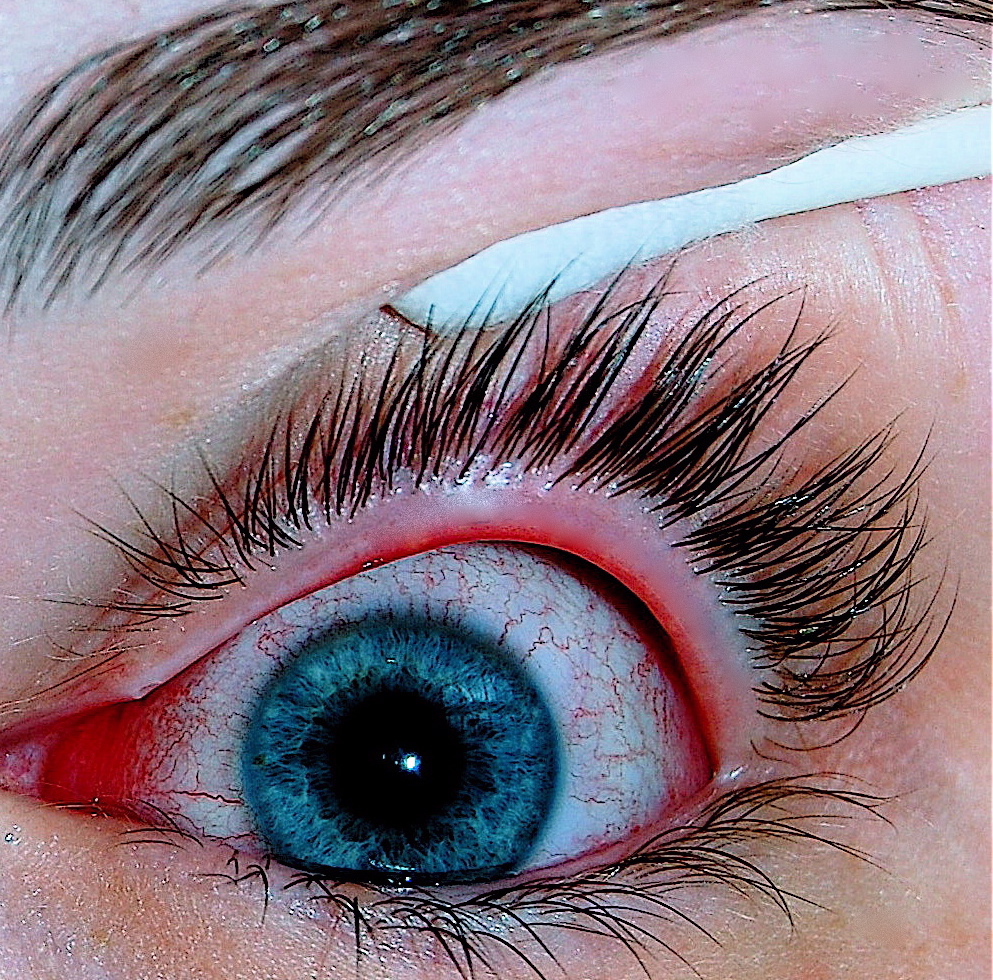
Allergic conjunctivitis is a bilateral conjunctival reaction to an environmental or contact allergen, and one of the most common causes of a red, irritated eye.[1] Itching is the dominant symptom — if a patient with a red eye does not report itching, seriously reconsider allergic conjunctivitis as the cause. The essential first task is not treating the itch — it is confirming this is conjunctivitis and not a sight-threatening red-eye mimic (angle-closure glaucoma, iritis/uveitis, scleritis, keratitis), and recognizing when allergic eye disease is severe enough (vernal or atopic keratoconjunctivitis) to threaten the cornea and need specialist-directed therapy.[2]
Recognize the Condition
Typical (seasonal/perennial) allergic conjunctivitis
Bilateral, itch-predominant, watery/stringy mucoid discharge, chemosis (conjunctival swelling), and lid edema. Often seasonal (pollen) or perennial (dust mite, pet dander), or triggered by a known contact allergen or contact lens wear (giant papillary conjunctivitis). Usually a history of atopy, other allergies, or asthma/eczema.
Severe allergic eye disease (vernal and atopic keratoconjunctivitis)
Vernal keratoconjunctivitis
A severe, chronic allergic eye disease predominantly affecting children and young adults (more common in males, warmer climates), with giant papillae on the upper tarsal conjunctiva, thick ropy mucoid discharge, and a real risk of corneal involvement (shield ulcer) if inadequately treated.
Atopic keratoconjunctivitis
A severe, chronic allergic eye disease in adults with atopic dermatitis, again with real potential for corneal scarring and vision loss if undertreated — both vernal and atopic keratoconjunctivitis are a different severity tier from typical seasonal allergic conjunctivitis and need specialist involvement.
Risk Factors
- History of atopy — asthma, eczema, allergic rhinitis, or other known allergies.
- Seasonal pollen exposure, or perennial exposure to dust mite/pet dander/mould.
- Contact lens wear (giant papillary conjunctivitis) or known contact allergen exposure (cosmetics, preservatives in eye drops).
- Personal history of atopic dermatitis (risk factor for atopic keratoconjunctivitis specifically).
- Male sex, younger age, and warmer climate (risk factors for vernal keratoconjunctivitis specifically).
Red Flags & Refer
Refer immediately to an ophthalmologist (or an optometrist if one is not available) for any of the following:
- Marked redness concentrated at the corneoscleral junction (limbal/ciliary injection), especially if one-sided.
- White corneal opacity or haze.
- Moderate-to-severe pain or photophobia not relieved by a test dose of topical anesthetic.
- Reduced visual acuity.
- A contact-lens wearer with suspected corneal infiltrate/ulcer.
- Suspected vernal or atopic keratoconjunctivitis (giant papillae, thick ropy discharge, photophobia, or any corneal involvement) — these need specialist-directed therapy, not standard over-the-counter allergy eye drops, given the real risk of permanent corneal scarring.[3]
Assessment & Diagnosis
Differentiating bacterial, viral, and allergic conjunctivitis, and blepharitis
These four conditions are the most commonly confused causes of a red, irritated eye in community practice. Distinguishing them correctly determines whether the patient needs an antibiotic, supportive care, an antihistamine, or eyelid hygiene — and getting it wrong means either an unnecessary antibiotic or a missed diagnosis.



| Feature | Bacterial conjunctivitis | Viral conjunctivitis | Allergic conjunctivitis | Blepharitis |
|---|---|---|---|---|
| Laterality | Often one eye first, may spread to the other | Usually starts in one eye, spreads to the other within days | Bilateral, essentially always | Bilateral, essentially always |
| Discharge | Purulent, thick, yellow-green; lids stuck together on waking | Watery to mucoid; no true pus | Watery, stringy/mucoid | Greasy debris and crusting at the lash base, not a true discharge |
| Itching | Minimal or absent | Mild, if present | The dominant symptom — if the patient does not report itching, reconsider allergic conjunctivitis | Mild irritation/burning more than itching |
| Associated findings | May follow otitis media in children; no preauricular node in most cases | Preauricular lymph node, recent URTI, conjunctival membranes, subconjunctival hemorrhage | Chemosis (conjunctival swelling), lid edema, history of atopy/seasonal pattern | Lash crusting, missing/misdirected lashes, recurrent styes, meibomian gland dysfunction |
| Typical course | Self-limited over 1-2 weeks even without treatment; antibiotics modestly shorten this | Self-limited over 1-3 weeks; highly contagious for the first 3-7 days | Persists as long as allergen exposure continues; recurs seasonally | Chronic, relapsing; managed rather than cured |
| 1st-line management | Often no treatment needed; a topical antibiotic modestly shortens recovery | Supportive care only — cold compresses, lubricants | Remove/avoid the allergen; topical antihistamine/mast-cell stabilizer | Lid hygiene: warm compresses plus lid margin cleansing |
History
- Itching versus pain/photophobia — itching should dominate the history in true allergic conjunctivitis.
- Seasonal pattern, known triggers, or contact lens wear.
- Personal or family history of atopy — asthma, eczema, allergic rhinitis.
- Any thick, ropy discharge or photophobia, which raises concern for vernal/atopic keratoconjunctivitis rather than typical seasonal disease.
Examination
- Best corrected visual acuity.
- Inspect for chemosis, lid edema, and papillary reaction; evert the upper lid to look for giant papillae if vernal keratoconjunctivitis is suspected.
- Fluorescein staining if corneal involvement (shield ulcer) is possible.
- Bilateral findings support allergic conjunctivitis — unilateral redness should prompt reconsideration of the diagnosis.
Treatment Targets
- Control itching and inflammation.
- Identify and reduce allergen exposure.
- Prevent corneal complications in severe (vernal/atopic) disease.
- Provide symptomatic relief.
Choose Initial Treatment
1st line, typical seasonal/perennial disease allergen avoidance plus a topical antihistamine/mast-cell stabilizer (e.g., olopatadine or ketotifen) — most patients respond well to this combination.
Vernal or atopic keratoconjunctivitis needs specialist-directed therapy — this may include a short, supervised course of a topical corticosteroid for flares, or a topical immunomodulator (cyclosporine, lifitegrast) for chronic control, given the real corneal risk of undertreated disease.
Do not use an ophthalmic corticosteroid outside specialist supervision — real efficacy for allergic flares, but long-term use raises glaucoma/cataract risk and needs monitoring.
Non-Pharmacologic Treatment
- Identify and avoid/reduce the specific allergen where possible — pollen, dust mite, pet dander, a specific cosmetic or contact lens solution.
- Cold compresses for symptomatic relief.
- Stop wearing contact lenses during a flare; consider a different lens type or care solution if giant papillary conjunctivitis related to lens wear is suspected.
- Avoid eye rubbing — worsens mast-cell degranulation and can contribute to mechanical corneal irritation.
- Preservative-free artificial tears can help dilute and flush allergen from the ocular surface.
Special Populations
Pregnancy/breastfeeding
Topical ophthalmic antihistamines/mast-cell stabilizers have minimal systemic absorption. Discuss any topical corticosteroid or immunomodulator use with the prescriber managing the pregnancy.
Children
Vernal keratoconjunctivitis predominantly affects children and young adults and needs ophthalmology co-management given the corneal risk — do not manage as simple seasonal allergic conjunctivitis.
Contact lens wearers
Giant papillary conjunctivitis related to lens wear or lens-care solution needs the trigger identified and modified (different lens material, care system, or wear schedule), not just symptomatic antihistamine treatment alone.
Monitoring & Follow-Up
Reassess if symptoms do not improve within 1-2 weeks of allergen avoidance plus topical therapy. Seasonal disease should improve as allergen exposure declines; perennial or unusually severe/persistent disease warrants reconsidering vernal or atopic keratoconjunctivitis and referring for specialist assessment.
Common Errors to Avoid
- Prescribing a topical antibiotic for allergic conjunctivitis — does not treat an allergic reaction and delays correct management.
- Missing vernal or atopic keratoconjunctivitis by treating a child or atopic adult with severe, chronic disease the same as typical seasonal allergic conjunctivitis.
- Using an ophthalmic corticosteroid for routine allergic conjunctivitis without specialist supervision — real efficacy, but long-term risk of glaucoma/cataracts requires monitoring.
- Overusing ophthalmic vasoconstrictors/decongestants for allergic redness — causes rebound hyperemia and tachyphylaxis; limit to occasional, short-term use.[4]
- Not asking specifically about itching — the single most useful symptom for distinguishing allergic from bacterial/viral conjunctivitis.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Ophthalmic antihistamines and mast-cell stabilizers
1st line for typical seasonal/perennial allergic conjunctivitis.
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Olopatadine | 0.1%: 1-2 drops Q6-8H 0.2%: 1 drop daily 0.7%: 1 drop daily | Minor stinging on instillation | Mast-cell-stabilizing properties. |
| Ketotifen | All ages: 1 drop Q8-12H | Minor stinging on instillation | Also available as a medication-releasing daily disposable contact lens. |
| Bepotastine besilate | All ages: 1 drop BID | Minor stinging; mild/transient taste disturbance | Mast-cell-stabilizing properties. |
| Sodium cromoglycate | All ages: 1-2 drops 4-6 times/day | Minor stinging on instillation | Does not provide immediate relief — may take 2-3 days to see improvement. |
| Lodoxamide | All ages: 1-2 drops QID | Minor stinging on instillation | Does not provide immediate relief — may take 2-3 days to see improvement. Specifically indicated for vernal keratoconjunctivitis. |
Ophthalmic NSAIDs
Ketorolac has specific labelling for seasonal allergic conjunctivitis itching in some formulations.
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Ketorolac tromethamine | All ages: 1 drop QID (0.4-0.5%) or BID (0.45%) | Mild-moderate stinging; epitheliopathy/ulceration with prolonged frequent use |
Ophthalmic corticosteroids
For flares of vernal/atopic keratoconjunctivitis, specialist-directed only, short-term (typically ≤2 weeks) with monitoring — long-term use raises glaucoma/cataract risk.
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Loteprednol | All ages: 1 drop TID-QID for up to 14 days | Minor stinging; glaucoma/cataracts with long-term use | May be less likely to raise intraocular pressure than other topical corticosteroids — often preferred for allergic flares. |
| Fluorometholone | All ages: 1-2 drops BID-QID | Minor stinging; glaucoma/cataracts with long-term use | May be less likely to raise intraocular pressure than other corticosteroids. |
Ophthalmic immunomodulators
For chronic control of vernal/atopic keratoconjunctivitis — specialist-directed; full response may take weeks to months.
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Cyclosporine ophthalmic | All ages: 1 drop BID | Ocular burning/pain on instillation | Allow 15 minutes before/after ocular lubricants. Response may take up to 3 months. |
| Lifitegrast | All ages: 1 drop BID | Eye irritation/pain, transient blurred vision, dysgeusia | Some patients notice initial relief after 2 weeks; full response may take months. |
References
- Conjunctivitis: a systematic review of diagnosis and treatment — JAMA (Azari AA, Barney NP). JAMA 2013;310(16):1721-1729
- Bedside diagnosis of the 'red eye': a systematic review — American Journal of Medicine (Narayana S, McGee S). Am J Med 2015;128(11):1220-1224
- Vernal keratoconjunctivitis: a review — Clinical and Experimental Ophthalmology (Leonardi A). Clin Exp Ophthalmol 2013;41(5):481-491
- Low-dose brimonidine for relief of ocular redness: integrated analysis of four clinical trials — Clinical and Experimental Optometry (Ackerman SL, Torkildsen GL, McLaurin E, et al.). Clin Exp Optom 2019;102(2):131-139
- Conjunctivitis Preferred Practice Pattern — American Academy of Ophthalmology (Hoskins Center for Quality Eye Care, PPP Cornea/External Disease Committee). 2023 update, published 2024
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.