Anaphylaxis
Clinical Snapshot
Anaphylaxis is a serious, systemic hypersensitivity reaction that is usually rapid in onset and may cause death.[1] It is a clinical diagnosis made at the bedside — treatment must never wait for laboratory confirmation. Intramuscular epinephrine is the only first-line treatment and the sole intervention proven to reduce mortality; no other drug reverses anaphylaxis, and antihistamines and corticosteroids are adjuncts only, never substitutes.[2]
Up to 10-20% of anaphylactic reactions occur with no skin or mucosal involvement at all, which is a leading cause of missed or delayed diagnosis and a contributor to fatal cases.[1] Pharmacists are frequently the first point of contact for a patient developing a reaction after starting a new medication, being stung, or eating a food allergen — prompt recognition and immediate epinephrine, not "wait and see," is what prevents death. Food is the leading trigger in children, while medications and insect venom are more common triggers in adults.[3]
Recognize the Condition

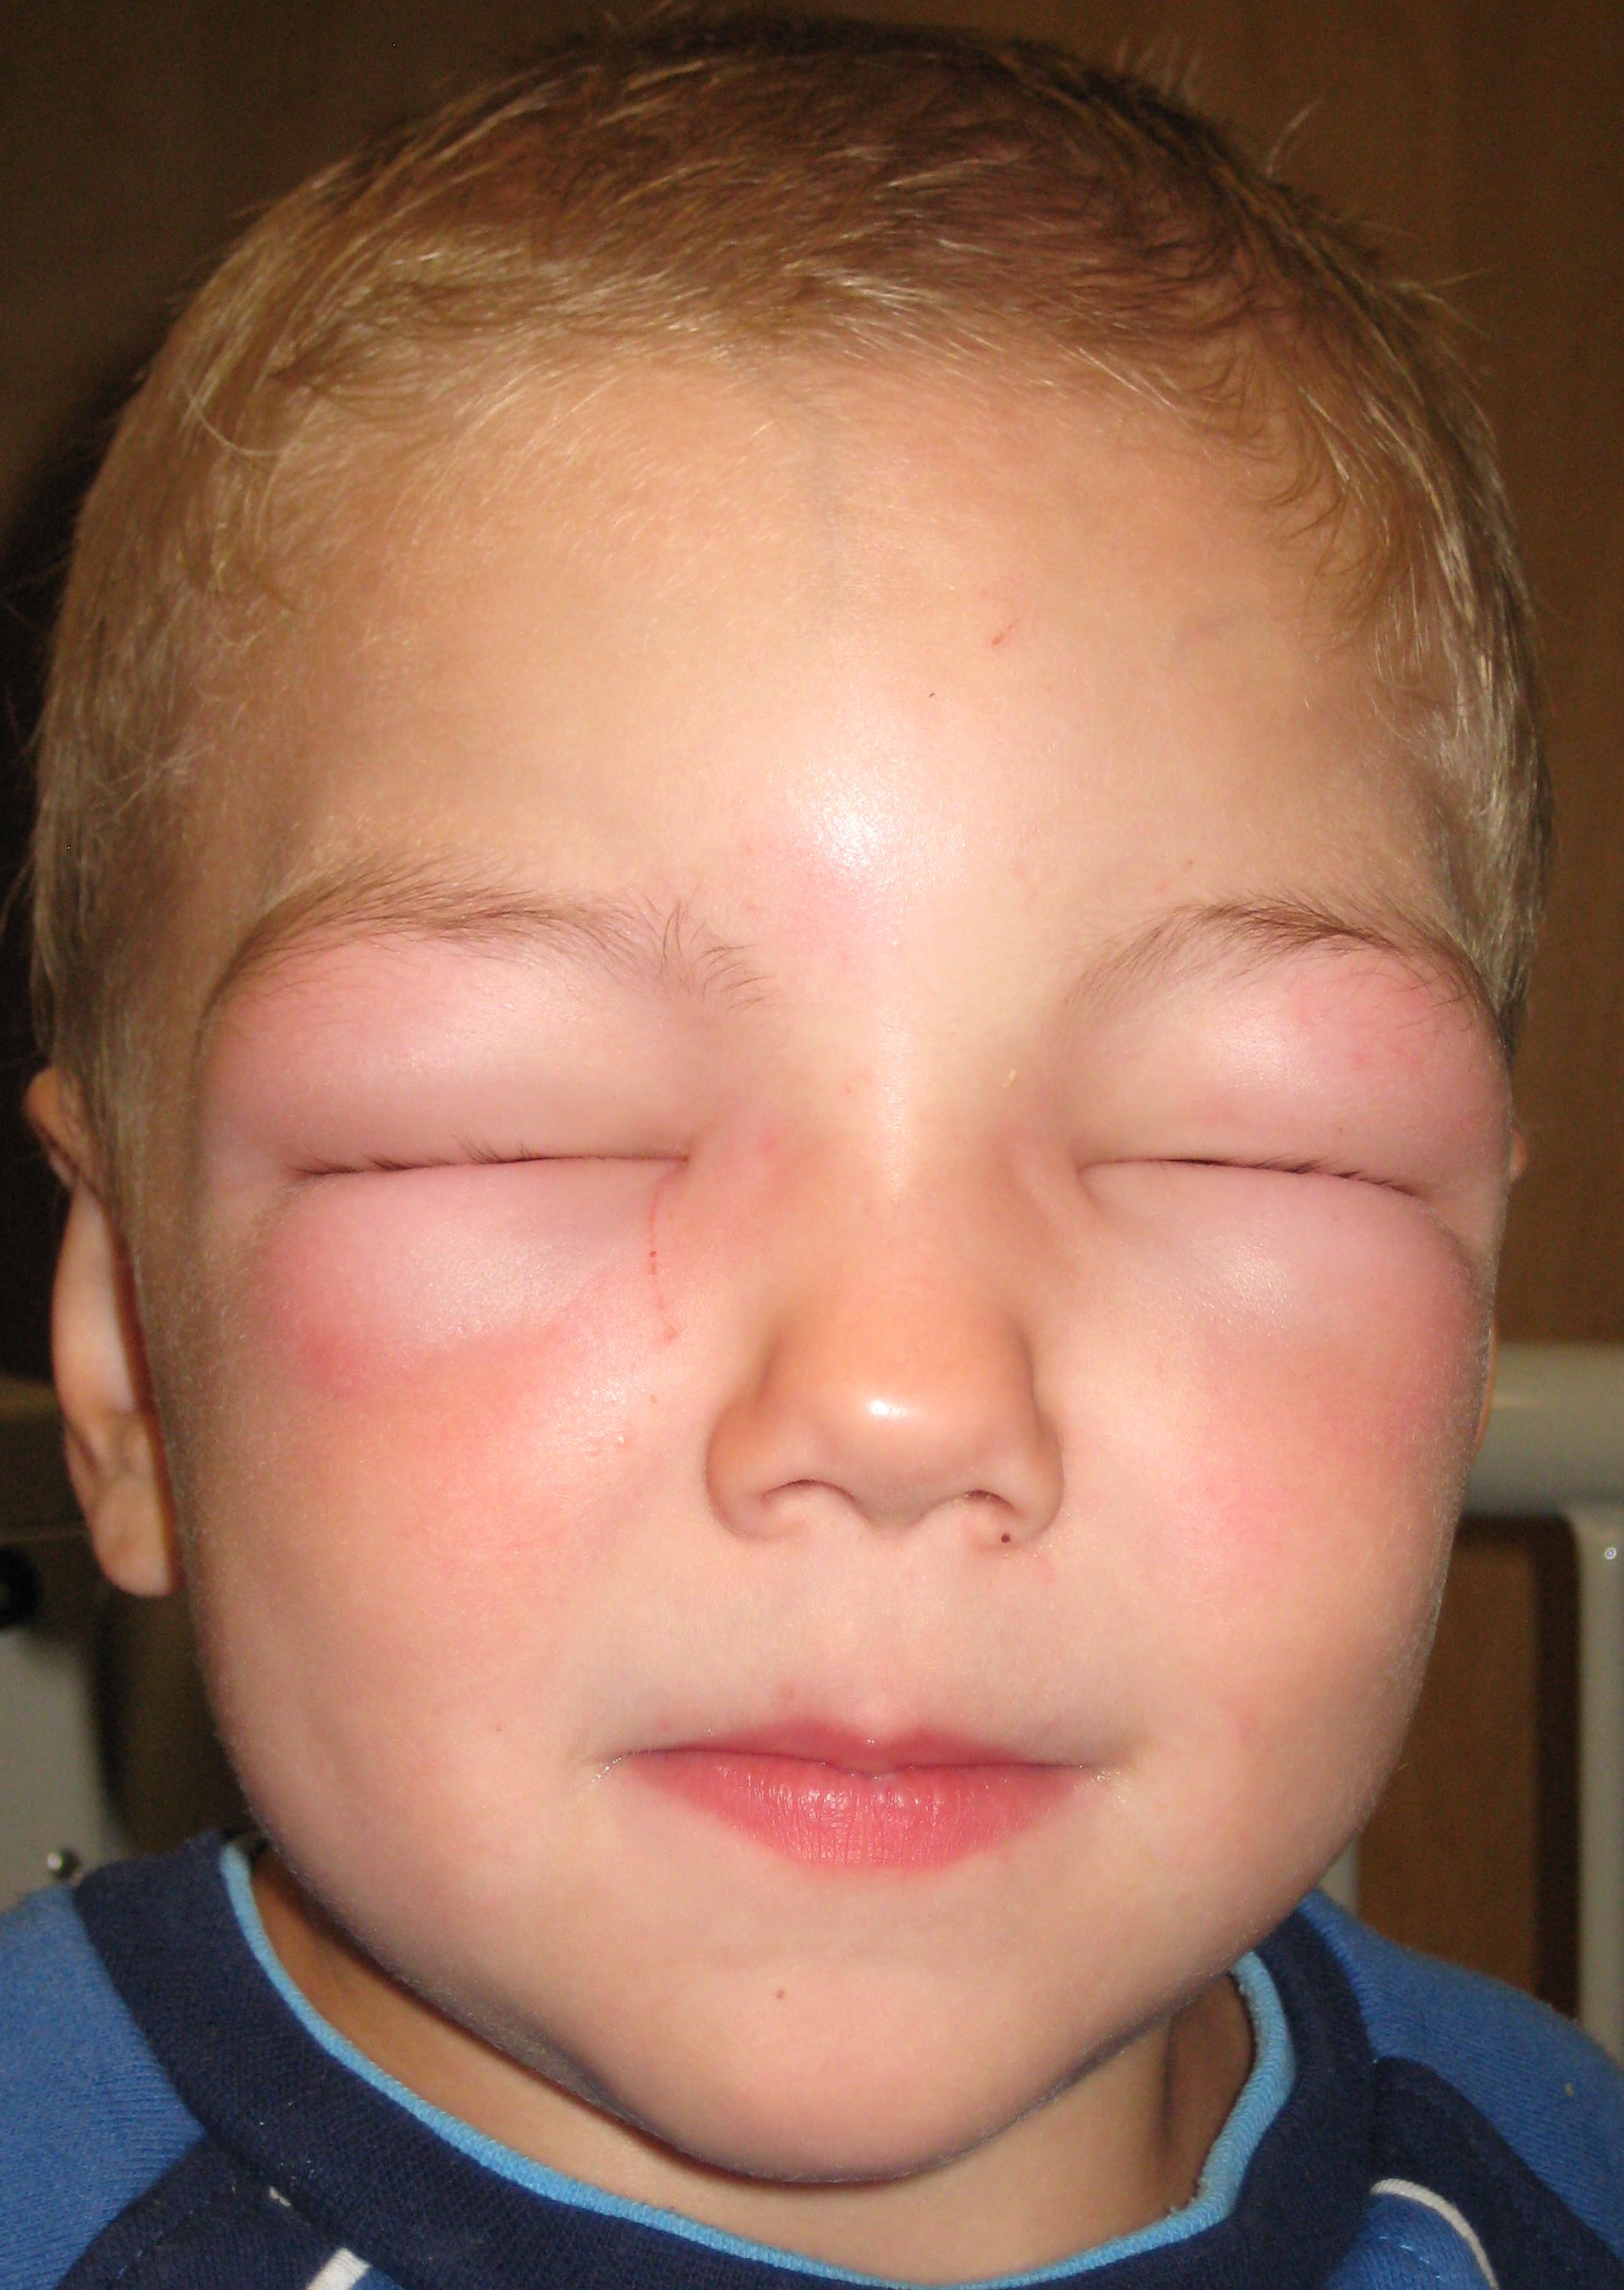
Recognize anaphylaxis by organ system
Onset is typically minutes to a few hours after exposure. Two or more systems involved rapidly after a likely allergen — or even a single severe respiratory or cardiovascular symptom after a known/probable allergen exposure — both meet diagnostic criteria; see Assessment & Diagnosis.
Skin / mucosal (present in roughly 80-90% of reactions)
Generalized hives (urticaria), flushing, pruritus, and swelling of the lips, tongue, or uvula (angioedema).
Respiratory
Dyspnea, wheeze/bronchospasm, cough, stridor, hoarseness or vocal change, a sensation of throat closing, and hypoxemia — the leading cause of anaphylaxis death.
Cardiovascular
Hypotension, tachycardia, dizziness, syncope, and collapse — the second leading cause of anaphylaxis death, from distributive shock.
Gastrointestinal
Severe crampy abdominal pain and repetitive vomiting — especially significant after exposure to a non-food allergen such as a sting or a medication.
Other
A sense of impending doom, uterine cramping, and — in infants, who cannot report symptoms — irritability, sudden behaviour change, drooling, or feeding refusal in place of a clearly reportable complaint.
Do not require skin or mucosal findings to diagnose anaphylaxis. A patient with only sudden hypotension, bronchospasm, or laryngeal symptoms after a known or highly probable allergen exposure still meets diagnostic criteria and needs immediate epinephrine.[1]
Risk Factors
- Previous anaphylaxis of any severity or cause — the single strongest predictor of a future episode.
- Known food, drug (especially antibiotics and NSAIDs), or insect-venom (hymenoptera) allergy.
- Poorly controlled asthma or any underlying reactive airway disease — a major risk factor for a severe or fatal reaction.[1]
- Mastocytosis, another clonal mast cell disorder, or an elevated baseline serum tryptase — anaphylaxis can be the first presentation of an underlying mast cell disorder.[1]
- Cardiovascular disease.
- Concurrent beta-blocker or ACE-inhibitor use, which can blunt the response to epinephrine and worsen reaction severity.[1]
- Cofactors that lower the reaction threshold or amplify severity for a given exposure: physical exercise (including food-dependent, exercise-induced anaphylaxis), acute infection, alcohol intake, sleep deprivation, psychological stress, NSAID use, and the perimenstrual period.[1]
- Age extremes — infants and young children may be unable to report symptoms; older adults have less cardiovascular reserve to compensate for distributive shock.
- A prior biphasic reaction, or a reaction that required more than 1 dose of epinephrine — both predict a more severe course on re-exposure.
Red Flags & Refer
Any confirmed or strongly suspected anaphylaxis is itself the red flag — this is a call-911, epinephrine-now emergency. There is no mild version of this condition that can be watched instead of treated.[2]
- Stridor, hoarseness, or a sensation of the throat/airway closing — impending upper airway obstruction; escalate to airway-capable emergency care immediately.
- Hypotension, syncope, or any sign of shock.
- Severe or rapidly progressive respiratory distress.
- No improvement, or worsening, after 1-2 doses of IM epinephrine — escalate to a monitored emergency setting for IV epinephrine infusion and advanced management.
- Cardiac or respiratory arrest — begin CPR immediately and continue epinephrine dosing per ACLS/PALS protocol.
- Anaphylaxis in pregnancy — manage with the same urgency, positioned on the left side, with combined obstetric involvement given the risk to placental perfusion from maternal hypotension.[1]
- Every patient who has had anaphylaxis, even a single mild episode, should be referred to an allergist for trigger confirmation and long-term risk-reduction planning — this is not optional follow-up.[1]
Assessment & Diagnosis
Anaphylaxis is a clinical diagnosis made at the bedside — treatment must never wait for laboratory confirmation. Anaphylaxis is highly likely when any 1 of the following 3 classic criteria is fulfilled:[3]
| Criterion | Definition |
|---|---|
| 1 | Acute onset of an illness (minutes to several hours) with involvement of the skin, mucosal tissue, or both (e.g., generalized hives, pruritus or flushing, swollen lips/tongue/uvula) AND at least 1 of: respiratory compromise (dyspnea, wheeze/bronchospasm, stridor, reduced peak flow, hypoxemia); reduced blood pressure or associated end-organ dysfunction (hypotonia, syncope, incontinence); or severe gastrointestinal symptoms (severe crampy abdominal pain, repetitive vomiting), especially after a non-food allergen. |
| 2 | Two or more of the following occurring rapidly (minutes to hours) after exposure to a likely allergen for that patient: skin/mucosal involvement; respiratory compromise; reduced blood pressure or end-organ dysfunction; or persistent gastrointestinal symptoms. |
| 3 | Reduced blood pressure after exposure to a known allergen for that patient — adults: systolic BP under 90 mmHg, or a decrease of more than 30% from that person's baseline; infants and children: an age-specific low systolic BP, or a decrease of more than 30% from baseline. |
The World Allergy Organization's 2020 update simplifies this to 2 criteria for teaching purposes — combining criteria 1 and 2 above, and explicitly stating that acute hypotension, bronchospasm, or laryngeal involvement after a known or highly probable allergen exposure counts as anaphylaxis even with no skin involvement at all, since skin signs are absent in 10-20% of reactions and their absence has contributed to missed, fatal anaphylaxis.[1] Both frameworks describe the same clinical reality — do not wait for multi-system involvement or skin findings before treating a presentation that is otherwise consistent with anaphylaxis.
Differential diagnosis
Consider vasovagal syncope (pale and bradycardic, not flushed and tachycardic, and normo/hypertensive once supine), an acute asthma exacerbation without other features, a panic/anxiety attack, vocal cord dysfunction, hereditary or ACE-inhibitor-associated angioedema (no urticaria, no hypotension), scombroid poisoning (histamine toxicity from spoiled fish — usually affects multiple diners from the same meal at once), carcinoid syndrome, and other forms of shock (cardiogenic, hypovolemic, septic).[1] When the presentation is genuinely ambiguous, treating empirically with epinephrine is the safer error.
Confirmatory testing
Serum tryptase can support the diagnosis retrospectively: draw as soon as feasible after reaction onset (tryptase rises within 15 minutes to 3 hours and peaks at 1-2 hours), and again for a true baseline at least 24 hours after full resolution. A normal tryptase drawn during the reaction does not rule out anaphylaxis — this is common with food-triggered reactions — but a peak substantially above baseline supports the diagnosis and should prompt investigation for an underlying mast cell disorder.[1] Tryptase results should never delay treatment and rarely change acute management.
Treatment Targets
- Reverse the reaction and prevent death — the only intervention that reliably does this is prompt intramuscular epinephrine.
- Maintain a patent airway, adequate breathing, and adequate circulation until the reaction resolves.
- Prevent progression to, and promptly detect, a biphasic reaction.
- Before discharge, put in place everything needed to reduce the risk and severity of the next episode — an epinephrine autoinjector prescription with hands-on training, a written action plan, and an allergist referral.
Choose Initial Treatment
Epinephrine — give immediately, do not wait
1st line, every patient intramuscular epinephrine 0.01 mg/kg of a 1 mg/mL (1:1000) solution, to a maximum single dose of 0.5 mg, injected into the mid-anterolateral thigh (vastus lateralis) — the only site with evidence supporting fast, reliable absorption.[3] Give it at the first sign of anaphylaxis; do not wait to see if symptoms progress, and do not give an antihistamine first.[4]
Repeat every 5-15 minutes if symptoms are not resolving. Do not withhold a repeat dose out of concern for epinephrine's transient side effects (tremor, pallor, anxiety, palpitations) — these are expected and self-limited at IM doses.[1]
Do not give epinephrine subcutaneously — the intramuscular route achieves a faster, higher, more reliable peak plasma concentration. Do not give an IV bolus outside a monitored resuscitation setting — IV bolus epinephrine carries a real risk of dangerous arrhythmia and is reserved for refractory anaphylaxis under continuous cardiac monitoring (see Treatment Failure).[1]
Position, oxygen, and fluids — simultaneously, not sequentially
Call emergency services (911) at the same time epinephrine is given, not after. Position the patient supine; allow a sitting position if there is respiratory distress; if pregnant, position on the left side (semi-recumbent) to avoid aortocaval compression; if unconscious or vomiting, use the recovery position. Never have the patient stand or walk while hypotensive — a sudden postural change can precipitate fatal "empty ventricle" cardiovascular collapse.[1] Remove or stop the trigger where feasible (e.g., stop an infusion). Give high-flow oxygen to any patient with respiratory distress or receiving repeat epinephrine doses, and start an IV crystalloid bolus for hypotension.[1]
Second-line adjuncts — adjunct only, never a substitute or a reason to delay epinephrine
Adjunct, cutaneous symptoms a second-generation oral antihistamine (e.g., cetirizine) is preferred over a first-generation agent (e.g., diphenhydramine) whenever an oral route is workable, since sedating first-generation agents can mask a worsening level of consciousness; antihistamines relieve itch/hives but do not reverse airway obstruction, bronchospasm, or hypotension.[4]
Adjunct, bronchospasm inhaled short-acting beta-2 agonist (salbutamol) for wheeze/bronchospasm not fully relieved by epinephrine.[1]
Adjunct, evidence for benefit is weak a corticosteroid (IV methylprednisolone or hydrocortisone, or an oral option) is commonly given with the goal of preventing protracted symptoms or a biphasic reaction, but current evidence does not reliably support either benefit, and routine use is increasingly considered optional rather than mandatory — never delay the epinephrine dose to obtain or administer a corticosteroid.[1]
Special situation IV glucagon for hypotension refractory to epinephrine, particularly in a patient taking a beta-blocker whose response to epinephrine may be blunted.[1]
Non-Pharmacologic Treatment
- Call emergency services (911) immediately, simultaneously with — not after — giving epinephrine.
- Remove or stop ongoing exposure to the trigger where feasible (e.g., stop an infusion; remove an insect stinger by scraping rather than pinching it).
- Position appropriately: supine for most patients; sitting if in respiratory distress; on the left side (semi-recumbent) if pregnant; recovery position if unconscious or vomiting. Never have the patient sit up suddenly or stand while hypotensive.[1]
- Give high-flow oxygen (ideally by non-rebreather mask) to any patient with respiratory distress or receiving repeat epinephrine doses.[1]
- Start an IV crystalloid bolus for hypotension once IV access is available.
- Begin CPR immediately if the patient loses pulses or stops breathing, continuing per ACLS/PALS protocol alongside epinephrine dosing.
- Monitor blood pressure, heart rate, oxygen saturation, respiratory status, and mental status at frequent, regular intervals throughout treatment and the observation period that follows.[1]
Special Populations
Pregnancy
Manage with the same urgency and the same first-line drug — epinephrine is not contraindicated in pregnancy, and untreated maternal anaphylaxis is a far greater risk to the fetus than treated anaphylaxis. Position the patient on the left side (semi-recumbent) rather than supine, to avoid aortocaval compression and preserve placental perfusion, and involve obstetric care alongside standard resuscitation.[1]
Infants and young children
Anaphylaxis is harder to recognize in infants, who cannot report symptoms — irritability, sudden behaviour change, drooling, or feeding refusal may be the only clue alongside more typical signs. Food (especially cow's milk, egg, and peanut) is the leading trigger in this age group. Weight-based autoinjector selection is inherently imprecise below 25 kg with currently available fixed doses (see Drug Tables), but the consequences of withholding epinephrine — progression, biphasic reaction, death — far outweigh the mild, transient adverse effects of a modestly higher-than-calculated dose, so err toward treating.[2]
Beta-blocker or ACE-inhibitor use
Both drug classes can blunt the response to epinephrine and are associated with more severe reactions; neither is a reason to withhold or under-dose epinephrine.[1] If hypotension is refractory to repeated epinephrine dosing in a patient on a beta-blocker, give IV glucagon, which acts independently of the beta-adrenergic receptor.
Cardiovascular disease
Pre-existing cardiovascular disease does not forbid epinephrine use in anaphylaxis — no other drug has its life-saving effect, and the risk of withholding it exceeds the cardiac risk of standard IM dosing. Reserve extra caution for the IV route, which carries materially higher cardiovascular risk than IM and should only be used in a monitored setting.[3]
Mastocytosis and other mast cell disorders
Patients with mastocytosis or another clonal mast cell disorder are at higher risk of severe — including venom-triggered — anaphylaxis, and anaphylaxis can be the first sign of the underlying disorder. An elevated baseline (not just peak) serum tryptase should prompt investigation for an underlying mast cell disorder and allergist referral.[1]
Idiopathic anaphylaxis
No trigger is identified in roughly 1 in 10 to 1 in 5 carefully worked-up cases, after a detailed history, examination for cutaneous mastocytosis, skin testing, and allergen-specific IgE testing have all failed to reveal a cause. Idiopathic anaphylaxis is treated identically to IgE-mediated anaphylaxis and still requires an epinephrine autoinjector prescription and allergist follow-up.[1]
Food, drug, venom, and exercise-induced triggers
Food is the leading trigger in children; medications and insect venom are more common triggers in adults.[3] Exercise is a recognized cofactor that can trigger anaphylaxis on its own (exercise-induced anaphylaxis) or lower the threshold for a food or drug trigger the patient otherwise tolerates (food-dependent, exercise-induced anaphylaxis) — advise avoiding exercise for several hours after eating a known co-trigger food, and always carrying an epinephrine autoinjector during exercise when this history is present.[1]
Monitoring & Follow-Up
Observation period after treatment
Around half of biphasic reactions occur within 6-12 hours of the initial reaction resolving, though the reported range is wide.[1] Risk-stratify the observation period rather than applying one fixed duration to everyone:
- Extend observation to at least 6 hours, and consider 12-24 hours or inpatient admission, for a severe initial reaction, a reaction requiring more than 1 epinephrine dose, delayed epinephrine administration, an unknown trigger, a history of a prior biphasic reaction, or significant comorbid asthma or cardiovascular disease.[5]
- For a milder reaction with a rapid, complete response to a single epinephrine dose and none of the risk factors above, a shorter observation period (as little as 1-2 hours) can be reasonable — provided the patient has reliable access to a second epinephrine dose and to emergency care after discharge.[6]
- Where individualized risk stratification is not being done, a minimum observation period of 4 hours after full symptom resolution is a reasonable default.[5]
What to monitor
Blood pressure, heart rate, oxygen saturation, respiratory effort, and mental status at frequent, regular intervals throughout treatment and observation.[1] Draw a baseline serum tryptase at least 24 hours after full symptom resolution if the diagnosis is uncertain or a mast cell disorder is suspected.
Before discharge
- Prescribe an epinephrine autoinjector — 2 doses, not 1 — and physically demonstrate its use, having the patient or caregiver "teach back" the technique; do not rely on a handout alone.[1]
- Provide a written, personalized anaphylaxis emergency action plan covering how to recognize a reaction and exactly when and how to use the autoinjector.
- Refer to an allergist/immunologist for trigger confirmation, prevention counselling, and consideration of immunotherapy where relevant (e.g., venom).[1]
- Recommend medical-alert identification (bracelet or wallet card) documenting the known or suspected trigger.
Common Errors to Avoid
- Giving an antihistamine or corticosteroid first, or instead of, epinephrine — neither reverses airway obstruction or hypotension, and delaying epinephrine to give them is a leading cause of preventable death.[4]
- Waiting to "see if it progresses" before giving epinephrine — clinicians cannot reliably predict which reactions will progress, and early treatment of even a single-system reaction after a known/probable allergen exposure is the safer default.[1]
- Injecting subcutaneously instead of intramuscularly, or into a site other than the anterolateral thigh.
- Sitting or standing a hypotensive patient up, or having them walk — this can precipitate fatal empty-ventricle collapse.[1]
- Withholding a repeat epinephrine dose out of concern for its transient, expected side effects (tremor, pallor, palpitations) when symptoms are not resolving.
- Withholding or under-dosing epinephrine because the patient takes a beta-blocker or has cardiovascular disease — the risk of withholding treatment exceeds the risk of the drug in this emergency.[1]
- Discharging a patient without a prescribed and demonstrated epinephrine autoinjector, a written action plan, and an allergist referral.[1]
- Cutting the observation period short in a patient with biphasic-reaction risk factors — severe initial reaction, multiple epinephrine doses required, unknown trigger, or a prior biphasic reaction.[5]
- Assuming a normal tryptase drawn during the reaction rules out anaphylaxis — it does not, particularly for food triggers.[1]
- Attempting IV bolus epinephrine outside a monitored resuscitation setting.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are typical adult and pediatric doses and require patient-specific confirmation. Select any drug name to open its complete Pharmasist Drug Database page.
Epinephrine autoinjectors — weight-based selection (Canadian CSACI recommendations)
Product monographs advise wider weight bands (0.15 mg for 15-30 kg, 0.3 mg for ≥30 kg, and calling 911 instead of using a device below 15 kg); CSACI's own recommendations, reproduced below, use narrower bands to reduce the underdosing that occurs as a child's weight climbs through the older, wider bands[3].
| Body weight | Autoinjector dose | Device options in Canada | Comments |
|---|---|---|---|
| Under 15 kg (including under 10 kg / infants) | 0.15 mg | EpiPen Jr®, Allerject® 0.15 mg | CSACI-recommended despite product monographs advising against an autoinjector below 15 kg for lack of a lower-dose alternative. Needle length can reach bone in a minority of infants this small, but the risk of withholding epinephrine outweighs this risk[2]. |
| 15 kg to under 25 kg | 0.15 mg | EpiPen Jr®, Allerject® 0.15 mg | CSACI recommends continuing the 0.15 mg dose through this whole band, moving the transition point down from the 30 kg threshold in the original product monographs. |
| 25 kg to under 45 kg | 0.3 mg | EpiPen®, Allerject® 0.3 mg, or Emerade™ 0.3 mg | Standard transition dose for this weight range. |
| 45 kg and over | 0.3 mg or 0.5 mg | EpiPen®/Allerject® 0.3 mg, or Emerade™ 0.5 mg | CSACI: consider the 0.5 mg device via shared decision-making, since the proportion of the ideal 0.01 mg/kg dose delivered by a fixed 0.3 mg device falls as weight rises above 30 kg; no head-to-head trial has yet shown 0.5 mg to be clinically superior to 0.3 mg. |
Epinephrine by ampule/syringe — IM dosing by age (hospital or clinic setting)
All doses are 1 mg/mL (1:1000) solution, given IM, repeated every 5-15 minutes as needed; maximum single dose 0.5 mg[1].
| Age / weight | Dose |
|---|---|
| Infants under 10 kg | 0.01 mg/kg (0.01 mL/kg of 1 mg/mL solution) |
| Children 1-5 years | 0.15 mg (0.15 mL) |
| Children 6-12 years | 0.3 mg (0.3 mL) |
| Teenagers and adults | 0.5 mg (0.5 mL) |
Do not prescribe drawn-up ampule-and-syringe epinephrine as a routine community first-aid alternative to an autoinjector — studies of parents drawing up doses under time pressure found a 40-fold range in the amount actually drawn, with delays and dosing errors even among trained caregivers[2].
Second-line antihistamines
Adjuncts for cutaneous symptoms only — neither drug reverses airway obstruction or hypotension, and neither should delay an epinephrine dose.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Cetirizine (2nd-generation) | Adult: 10 mg PO once Pediatric: Weight-/age-based dosing per product monograph | Mild sedation, headache | Minimal — few clinically significant interactions | Preferred over a 1st-generation agent whenever an oral route is workable, since sedation can otherwise mask a worsening level of consciousness. |
| Diphenhydramine (1st-generation) | Adult: 25-50 mg IM or IV Pediatric: 1 mg/kg, max 50 mg | Sedation, anticholinergic effects, paradoxical agitation in children | Additive sedation with other CNS depressants | Use when a parenteral route is specifically needed. Sedation can mask a worsening level of consciousness — reassess mental status frequently. |
Second-line corticosteroids
Given with the goal of shortening protracted symptoms or reducing biphasic-reaction risk, but current evidence does not reliably support either benefit — do not delay epinephrine to obtain or give one of these.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Methylprednisolone | Dosing: 1-2 mg/kg IV, max 125 mg | Hyperglycemia, mood changes, insomnia with repeated dosing | Minimal for a single acute dose | IV formulation for the acute setting. |
| Hydrocortisone | Dosing: 5 mg/kg IV, max 200 mg | Hyperglycemia, mood changes with repeated dosing | Minimal for a single acute dose | Alternative IV corticosteroid. |
| Dexamethasone | Adult: 4-12 mg PO/IM once Pediatric: 0.15-0.6 mg/kg, max 12 mg | Hyperglycemia, insomnia | Minimal for a single acute dose | An oral or IM alternative where IV access is not yet available. |
Bronchospasm adjunct
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Salbutamol | Dosing: Inhaled/nebulized per institutional protocol | Tremor, tachycardia, palpitations | Additive tachycardia with epinephrine — expected and monitored, not a reason to withhold either drug | For wheeze/bronchospasm not fully relieved by epinephrine. Not a substitute for repeat epinephrine dosing. |
Refractory hypotension
Reserved for anaphylaxis not responding to repeated IM epinephrine, particularly in a patient on a beta-blocker.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Glucagon | Adult: 1-2 mg IV over 5 minutes; may repeat or follow with an infusion of 5-15 mcg/min Pediatric: 20-30 mcg/kg IV, max 1 mg | Nausea, vomiting (protect the airway), transient hyperglycemia | Reverses the effect of beta-blockers on this pathway specifically — no significant interaction with epinephrine itself | Acts independently of the beta-adrenergic receptor, so it works even when a beta-blocker is blunting epinephrine's effect. |
References
- World Allergy Organization Anaphylaxis Guidance 2020 — World Allergy Organization Journal (Cardona V, Ansotegui IJ, Ebisawa M, et al.). World Allergy Organ J 2020;13(10):100472
- CSACI position statement: epinephrine auto-injectors and children < 15 kg — Allergy, Asthma & Clinical Immunology (Halbrich M, Mack DP, Carr S, Watson W, Kim H). Allergy Asthma Clin Immunol 2015;11:20
- CSACI position statement: transition recommendations on existing epinephrine autoinjectors — Allergy, Asthma & Clinical Immunology (Li LDX, Abrams EM, Lavine E, Hildebrand K, Mack DP). Allergy Asthma Clin Immunol 2021;17:130
- Management of anaphylaxis — CMAJ (Jeimy S, Huan PW, Abrams E). CMAJ 2025;197(38):E1270-1
- Anaphylaxis: Recognition and Management — American Family Physician (Pflipsen MC, Vega Colon KM). Am Fam Physician 2020;102(6):355-362
- Anaphylaxis: A 2023 practice parameter update — Annals of Allergy, Asthma & Immunology (Golden DBK, Wang J, Waserman S, et al.). Ann Allergy Asthma Immunol 2023;132(2):124-176
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.