Cluster Headache
Clinical Snapshot
Cluster headache is the most common of the trigeminal autonomic cephalalgias (TACs) -- a group of primary headache disorders that share short-lasting, severe, strictly one-sided pain attacks together with prominent ipsilateral cranial autonomic symptoms.[1] It is a genuinely different disease from migraine and tension-type headache, not a more severe version of either: the attacks are shorter, far more intense, occur in clustered bouts, and are managed with an entirely different drug list -- high-flow oxygen and injectable/intranasal triptans for an attack, and verapamil as first-line prevention, none of which have a comparable role in migraine or tension-type headache.[2]
Attacks are excruciating -- among the most severe pain a person can experience -- and the disorder has earned the lay nickname "suicide headache"; a meaningful minority of patients report suicidal ideation during an unremitting bout, which makes deliberate safety screening part of routine assessment, not an afterthought.[3]
Cluster headache is classified as episodic (ICHD-3 code 3.1.1) -- attacks occurring in bouts lasting days to months, separated by pain-free remission periods of 3 months or longer -- or chronic (ICHD-3 code 3.1.2) -- attacks occurring for more than 1 year without remission, or with remission periods shorter than 3 months. About 80% of patients have the episodic form; up to 12% of episodic patients eventually progress to chronic cluster headache, and rarely a chronic pattern reverts to episodic.[3]
Recognize the Condition
The cluster headache attack
Pain
Severe-to-very-severe, strictly unilateral and almost always side-locked (the same side for an entire bout, and usually for life) pain centred in the orbital, supraorbital, and/or temporal region, sometimes referred to the forehead, jaw, throat, ear, neck, or shoulder. Patients often describe it as a "hot knife stabbing the eye" or a "burning thorn in the temple," with intensity frequently rated 9-10/10. A single untreated attack lasts 15-180 minutes, occurring at a frequency of every other day up to 8 times a day during a bout.[3]
Behaviour during an attack -- the key differentiator from migraine
Cluster headache patients characteristically become restless and agitated during an attack -- pacing, rocking, or unable to stay still -- and this "sense of restlessness or agitation (akathisia)" is itself one of the ICHD-3 diagnostic criteria. This is the opposite of migraine, where patients typically seek a dark, quiet room and prefer to lie motionless; the distinction is one of the fastest and most reliable ways to tell the two apart at the bedside.[1]
Ipsilateral autonomic features
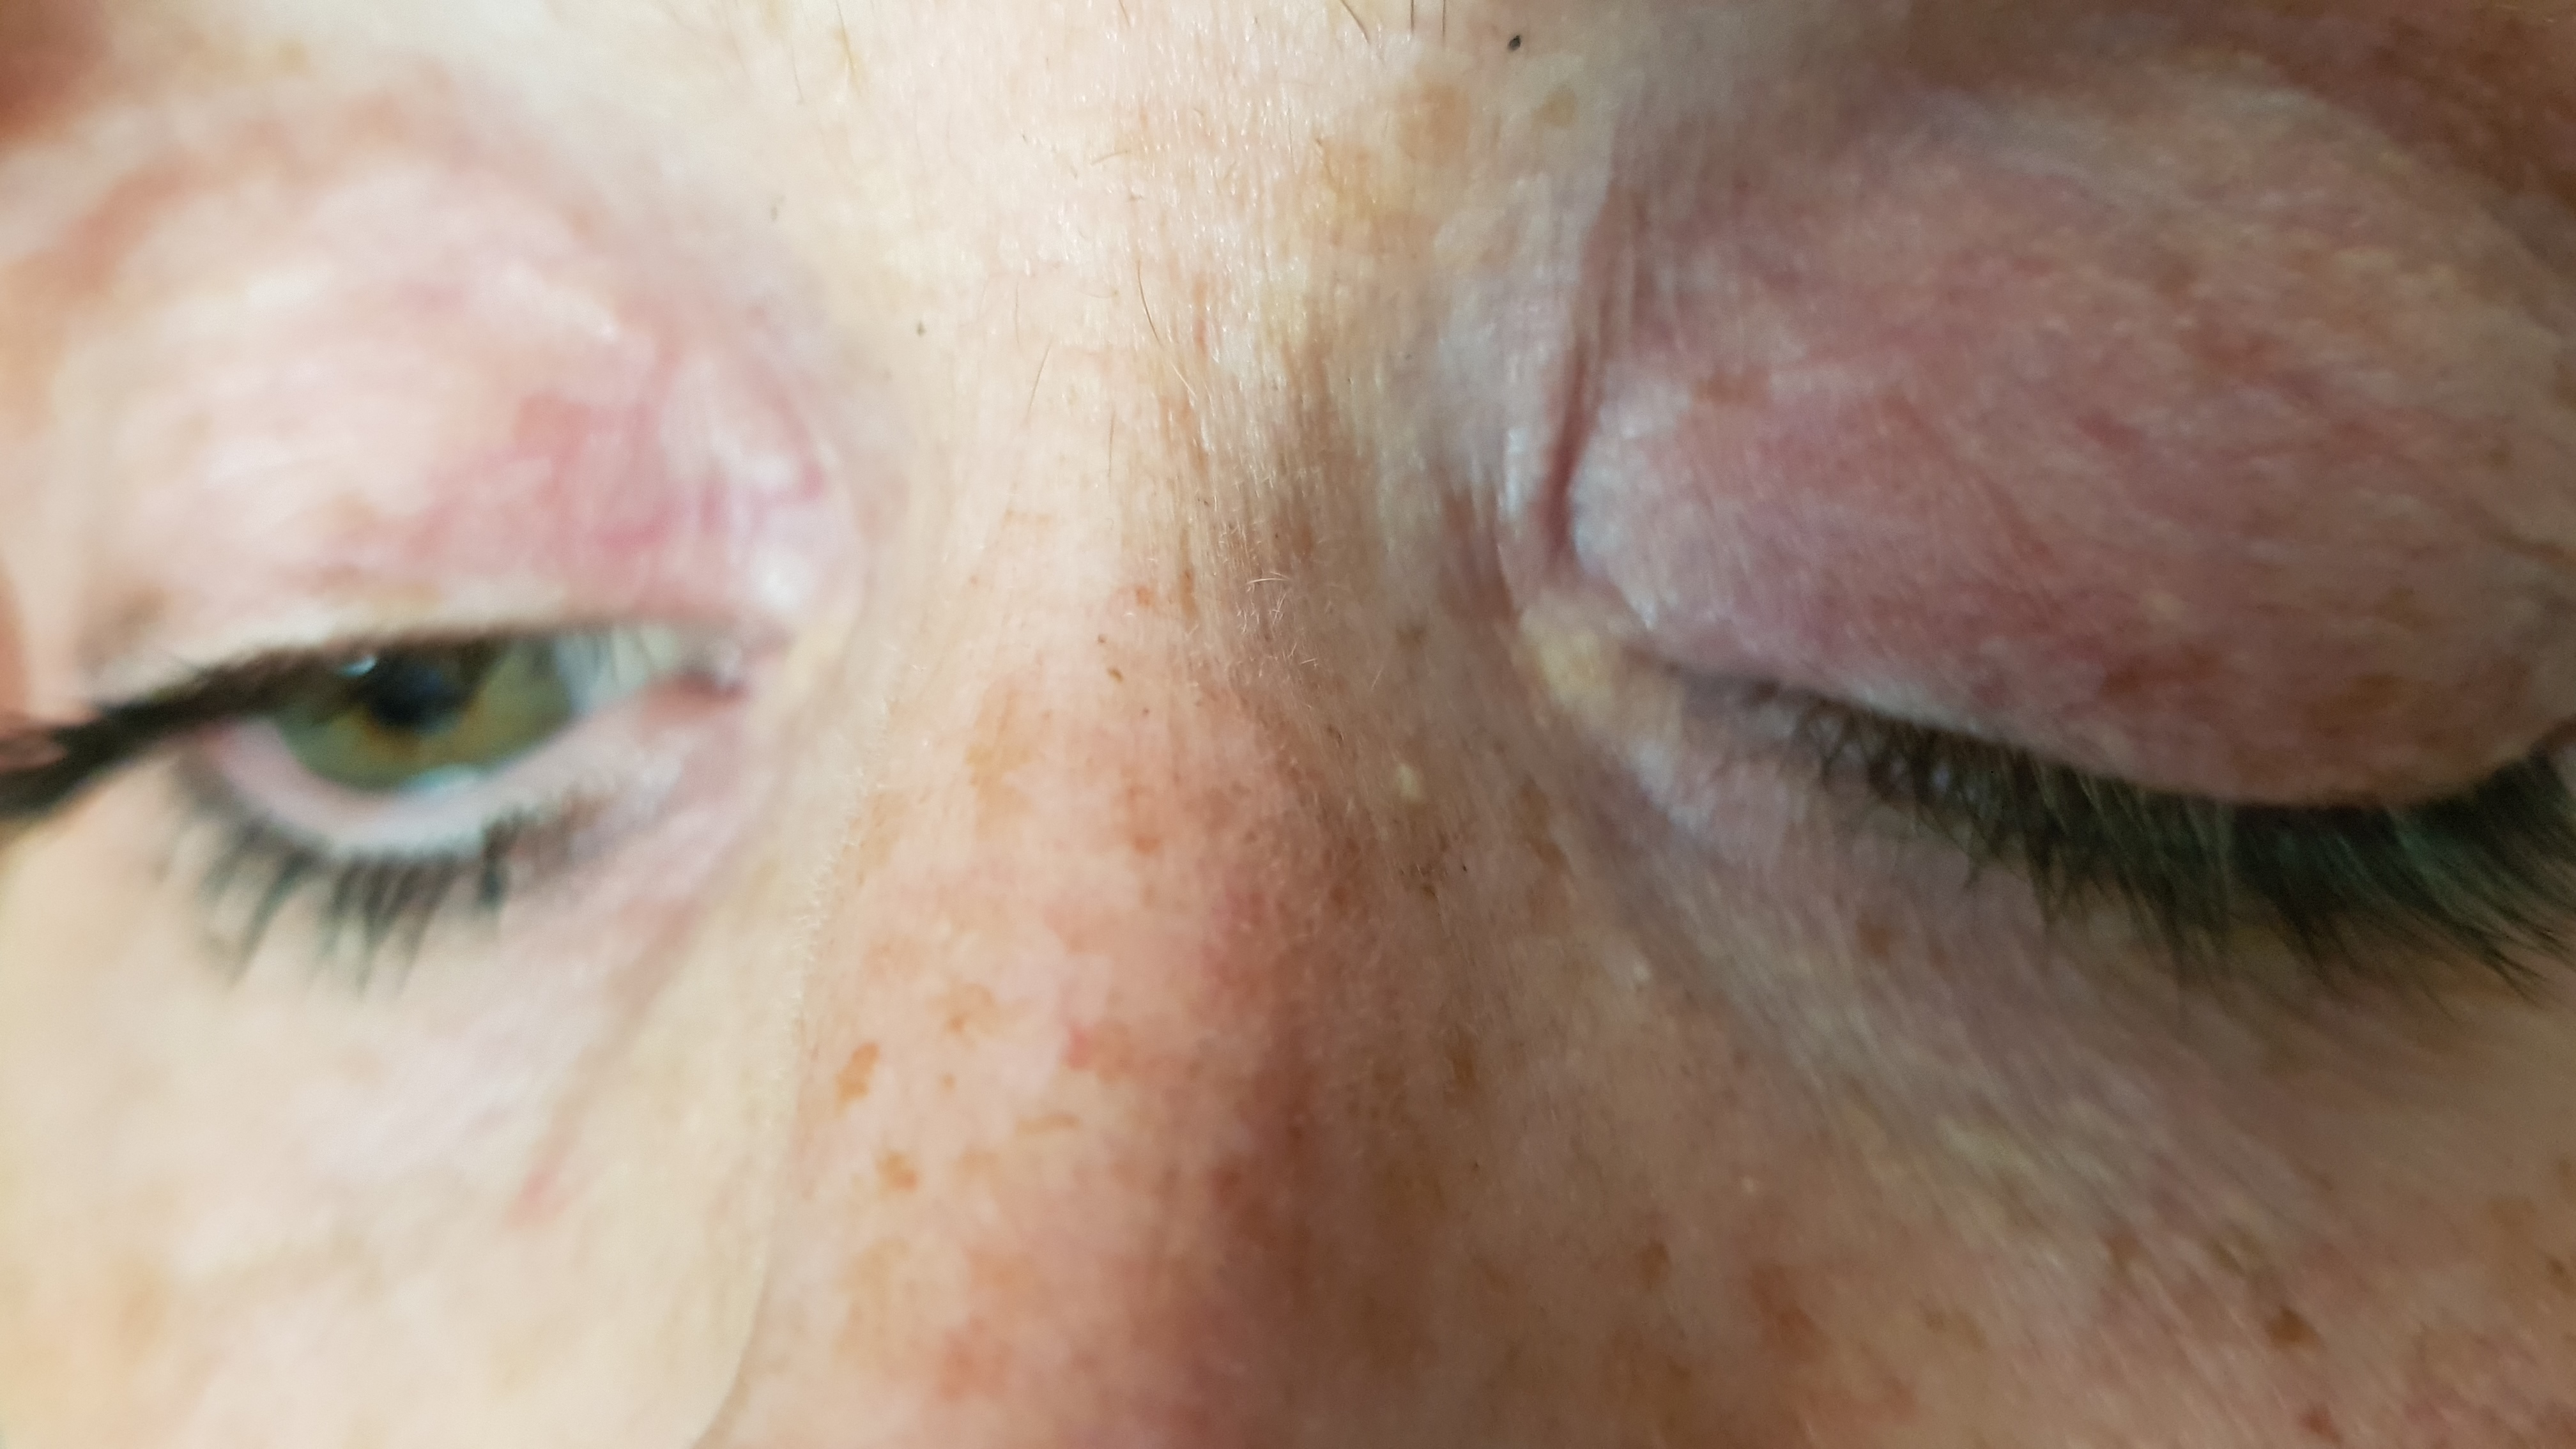
At least one autonomic sign or symptom on the same side as the pain accompanies the great majority of attacks: conjunctival injection and/or lacrimation, nasal congestion and/or rhinorrhea, eyelid edema, forehead and facial sweating, and miosis and/or ptosis (a partial Horner syndrome). Photophobia and phonophobia can occur but, unlike in migraine, tend to be lateralized to the side of the pain rather than generalized.[3]

Circadian and circannual pattern
Attacks are frequently nocturnal -- classically waking the patient 1-2 hours after falling asleep -- and bouts often recur at the same time of year (spring or autumn is common), a circannual rhythmicity that is itself a useful diagnostic clue.[2]
Episodic vs. chronic cluster headache
During an active bout (a "cluster period"), attacks occur in clusters typically lasting 7 days to several months (most often 4-12 weeks), followed by a symptom-free remission of 3 months or longer in the episodic form; during remission, cluster-typical triggers (alcohol, in particular) no longer provoke an attack. In chronic cluster headache -- 15% of all cases -- attacks occur on a near-daily basis without a meaningful remission, or with remission shorter than 3 months.[3]
Risk Factors
- Male sex -- historically estimated at 3-4:1 male-to-female, though the gap has been narrowing over recent decades.[3]
- Age of onset typically in the 20s-40s (commonly cited peak around 28-30 years).[2]
- Family history -- a modest genetic component, with cluster headache reported in 2-7% of first-degree relatives of affected patients.[3]
- Cigarette smoking -- most patients with cluster headache are current or former smokers, one of the strongest and most consistent associations described for this disorder; smoking cessation should be raised, though it should not delay starting effective treatment.[2]
- Alcohol -- a well-established trigger for attacks, but specifically during an active bout only; the same patient can typically drink alcohol without triggering an attack while in remission, an important and reassuring counselling point.[3]
- Other vasodilating triggers during a bout -- nitroglycerin/other nitrates, histamine, strenuous exertion, high altitude, and daytime napping have all been reported to provoke attacks in the active period.[2]
- The underlying mechanism is not fully understood but is thought to involve hypothalamic activation (accounting for the circadian/circannual rhythmicity) together with activation of the trigeminal-autonomic reflex, which produces both the severe first-division trigeminal pain and the ipsilateral parasympathetic (autonomic) features.[3]
Red Flags & Refer
Cluster headache is easier to diagnose than the other TACs once suspected, but diagnosis is often significantly delayed in practice, and secondary causes with a genuinely identical presentation exist and must be actively excluded, not assumed away.[2]
- First presentation of cluster-type headache -- neuroimaging (brain MRI including the craniocervical junction) is recommended to exclude a secondary cause before treating as primary cluster headache, even when the presentation looks classic.[3]
- Any atypical feature -- an abnormal neurologic examination, onset after age 60, a clear change from the patient's previously stable pattern, or poor/absent response to a properly administered trial of oxygen and a triptan (both of which should be highly effective in true cluster headache) -- all warrant repeat or expanded imaging rather than simply escalating the same treatment.[3]
- Case reports describe secondary "cluster-like" headache from tumours and malformations located near the midline -- particularly the pituitary/parasellar region and the posterior fossa -- as well as brain infarction or inflammatory plaques; this risk is higher, and imaging correspondingly more important, in older patients or with any abnormal examination finding.[3]
- Screen explicitly for suicidal ideation during an active bout -- the pain intensity of cluster headache is severe enough that suicidal thoughts and, rarely, suicidal behaviour have been documented, and patients rarely volunteer this without being asked directly. Any expressed suicidal ideation needs urgent mental health involvement, not reassurance alone.[3]
- Consider hospitalization for intravenous transitional treatment (e.g., IV corticosteroids or dihydroergotamine), an atypical initial presentation, failure of an adequate trial of two preventive medications, or significant psychophysical distress from drug-refractory or persistent daily attacks.[3]
- Refer to a headache specialist or neurology for diagnostic uncertainty (especially distinguishing from paroxysmal hemicrania or SUNCT/SUNA), chronic cluster headache, verapamil failure or intolerance at a maximally titrated, ECG-cleared dose, lithium initiation, or candidacy for neuromodulation.
Assessment & Diagnosis
ICHD-3 diagnostic criteria for cluster headache
| Criterion | Requirement |
|---|---|
| A | At least 5 attacks fulfilling criteria B-D |
| B | Severe or very severe unilateral orbital, supraorbital, and/or temporal pain lasting 15-180 minutes when untreated |
| C | Either or both of: (1) at least one ipsilateral autonomic symptom/sign (conjunctival injection and/or lacrimation, nasal congestion and/or rhinorrhea, eyelid edema, forehead/facial sweating, miosis and/or ptosis); (2) a sense of restlessness or agitation |
| D | Attacks occurring with a frequency between one every other day and 8 per day |
| E | Not better accounted for by another ICHD-3 diagnosis |
Differentiating the trigeminal autonomic cephalalgias
Cluster headache, paroxysmal hemicrania, and SUNCT/SUNA share the same basic structure -- short-lasting, strictly unilateral pain with ipsilateral cranial autonomic features -- but differ enough in duration, frequency, and (critically) treatment response that mistaking one for another leads directly to the wrong treatment.
| Feature | Cluster headache | Paroxysmal hemicrania | SUNCT / SUNA |
|---|---|---|---|
| Attack duration | 15-180 minutes | 2-45 minutes | 1-600 seconds (typically seconds to a few minutes) |
| Attack frequency | Every other day to 8/day | 1-40/day | 1/day up to 30/hour |
| Sex ratio (M:F) | ~3-4:1 (male predominant) | ~1:3 (female predominant) | ~8:1 (male predominant) |
| Response to indomethacin | No response | Absolute, complete response -- diagnostic | No response |
| Preferred acute treatment | Oxygen, SC/intranasal triptan | Indomethacin (both acute and preventive) | IV lidocaine infusion for severe attacks |
| Preferred preventive treatment | Verapamil | Indomethacin | Lamotrigine (topiramate/gabapentin alternatives) |
An absolute, complete response to a therapeutic trial of indomethacin is itself part of the ICHD-3 diagnostic criteria for paroxysmal hemicrania -- if diagnostic uncertainty exists between cluster headache and paroxysmal hemicrania, a supervised indomethacin trial is a reasonable and often diagnostic next step. Cluster headache itself does not respond to indomethacin. If paroxysmal hemicrania is being considered, any concurrent lithium should be stopped first, since lithium raises indomethacin levels.[2][4]
Migraine as a differential
Migraine remains the most important non-TAC differential: migraine pain is typically longer-lasting (4-72 hours untreated), less strictly one-sided, and accompanied by a preference to lie still rather than the restlessness typical of cluster headache; nausea/vomiting and generalized (not lateralized) photophobia/phonophobia are also more typical of migraine. Both conditions can coexist in the same patient, which is itself a recognized contributor to diagnostic delay -- see the separate Migraine chapter for its full diagnostic and treatment detail.[2]
Investigations
- No laboratory, electrophysiological, or CSF test contributes to the diagnosis of a primary TAC -- diagnosis rests on history and a normal neurologic examination.[3]
- Brain MRI including the craniocervical junction is recommended for the initial diagnosis of cluster headache, and for any patient with an abnormal neurologic examination or another red flag (see Red Flags & Refer), specifically to exclude a structural secondary cause.[3]
- A baseline ECG is required before starting verapamil, given its cardiac conduction effects (see Choose Initial Treatment and Monitoring & Follow-Up).[2]
Treatment Targets
- Rapidly and reliably terminate individual attacks -- given attack severity, "rapidly acting" is not optional; a slow-onset acute treatment is not an adequate treatment for this disease.
- Suppress attacks entirely and re-establish remission for the expected duration of the bout, using transitional and preventive therapy together rather than acute treatment alone.
- Minimize acute-medication burden and its risks by front-loading effective, non-overusable acute options (oxygen) alongside triptans.
- Detect and manage medication-related complications early -- verapamil's cardiac conduction effects and lithium's narrow therapeutic index both require active, scheduled monitoring, not passive follow-up.
- Screen for and address the psychological burden of the disease, including suicidal ideation during active bouts.
- Taper preventive therapy appropriately once sustained remission is achieved, rather than continuing indefinitely by default in episodic cluster headache, or stopping abruptly in any patient.
Choose Initial Treatment
First-line, and can be combined
1st line 100% oxygen at a flow rate of at least 12 L/minute (up to 15 L/minute) for 15-20 minutes via a non-rebreather mask -- a nasal cannula does not deliver an adequate flow rate or FiO2 and should not be used. Oxygen has no cardiovascular contraindications, no drug interactions, no medication-overuse ceiling, and can be used multiple times a day; a demand-valve mask improves the response in some patients and portable devices exist for use outside the home.[3][2]
1st line subcutaneous sumatriptan 6 mg -- the fastest-onset acute drug treatment, with the great majority of patients pain-free within 5-20 minutes; labelled for up to 2 doses in 24 hours. Oxygen and SC sumatriptan can be used together and are not mutually exclusive.[3]
Alternative intranasal zolmitriptan 5 mg (may be increased to 10 mg) or intranasal sumatriptan 20 mg for patients who cannot tolerate self-injection, when SC sumatriptan is unavailable, or as an add-on -- both are effective but have a slower onset than the subcutaneous route.[3]
Avoid oral triptans as routine acute therapy -- attacks peak too quickly and resolve within 15-180 minutes for an orally absorbed drug to act in time; the evidence for oral triptans in cluster headache is weak and inconsistent, and only injectable or intranasal formulations should be considered first-line.[3][2]
Indicated primarily for high-frequency episodic cluster headache (more than 2 attacks/day) to stop the bout quickly while a preventive medication is being titrated to an effective dose -- transitional therapy is not a substitute for starting a maintenance preventive, since attacks are very likely to recur once a short steroid course ends without one already on board.[2]
Oral corticosteroids e.g., prednisone starting at 60-100 mg/day as a single morning dose, most often for about 5 days, then tapered down over the following 1-2 weeks; keep the total course well under a month to limit steroid-related adverse effects, and do not use as a long-term therapy.[3][2]
Greater occipital nerve (GON) block a corticosteroid injection (e.g., methylprednisolone), with or without a local anesthetic, given ipsilateral to the pain -- effective and may require only one or a few injections; can be repeated if effective.[3]
1st line verapamil -- start at 80 mg PO three times daily (a regular-release preparation is generally preferred over extended-release for more reliable levels through 3-times-daily dosing), and increase the dose by 80 mg every 1-2 weeks toward a target of at least 240 mg/day; many patients ultimately need 480 mg/day or more. A baseline ECG is mandatory before starting, and follow-up ECGs are required once the daily dose reaches 400 mg and again roughly a week after every further increase above that level, watching specifically for PR-interval prolongation, bradycardia, or (uncommonly, mostly at very high doses) higher-degree AV block. Avoid grapefruit and grapefruit juice, which inhibit verapamil's metabolism and can raise levels substantially. Do not stop verapamil abruptly once effective -- taper gradually over 2-4 weeks after the patient has been in sustained remission beyond their usual bout length.[2][3]
Note many drugs that are effective migraine preventives -- beta-blockers in particular -- are not effective in cluster headache and should not be substituted for verapamil on the assumption that "any migraine preventive will do."[3]
2nd line lithium carbonate, for patients in whom verapamil is ineffective, not tolerated, or contraindicated, and particularly considered in chronic cluster headache -- start 300 mg PO twice daily, increasing to 300 mg three times daily after about a week if there is no response; target a trough serum lithium level of 0.4-0.8 mmol/L and do not exceed 1.2 mmol/L. Obtain baseline renal and thyroid function before starting, and monitor both periodically thereafter, along with lithium levels. NSAIDs (including indomethacin) raise lithium levels and can precipitate toxicity; verapamil itself can enhance lithium excretion, so watch for reduced efficacy when the two are combined.[2]
Add-on / alternative preventives (weaker evidence) topiramate (open-label evidence only, target at least 100 mg/day starting from 25 mg), melatonin 10 mg nightly (modest evidence from a single small randomized trial, low-risk adjunct particularly in episodic cluster headache), and galcanezumab 300 mg SC monthly (licensed specifically for episodic cluster headache based on a positive randomized trial -- a chronic cluster headache trial of the same drug was not more effective than placebo).[3]
Non-Pharmacologic Treatment
- During an active bout specifically, advise avoiding alcohol, nitroglycerin/other vasodilating medications, strenuous exertion, high altitude, and daytime napping -- all recognized attack triggers during the active period, but not necessarily during remission (a genuinely reassuring distinction to make explicit for patients).[3]
- Teach correct oxygen technique specifically -- a non-rebreather mask at 12-15 L/minute, seated upright, breathing normally for the full 15-20 minutes -- since this simple, highly effective, side-effect-free treatment is frequently used incorrectly (most often with an inadequate-flow nasal cannula) and then wrongly judged to have failed.[2]
- Smoking cessation counselling, given the strong association between cluster headache and smoking -- but do not delay effective acute/preventive treatment while pursuing it.[2]
- A headache diary tracking attack frequency, bout onset, and remission is genuinely useful here -- it guides how long to continue preventive therapy and when it is reasonable to begin a taper.
- Non-invasive vagus nerve stimulation (nVNS) has a strong evidence base as an add-on acute treatment in episodic cluster headache (not shown effective for chronic cluster headache acute attacks), and a weaker evidence base as an add-on to standard preventive care.[3]
- Explicit psychological support and safety screening -- validate the severity of the pain, explain the cyclical/self-limited nature of episodic bouts, and directly ask about mood and suicidal ideation during an active bout rather than waiting for the patient to raise it.[3]
- For refractory chronic cluster headache that has failed medical therapy, invasive options exist at specialized centres -- sphenopalatine ganglion (SPG) stimulation has a strong evidence base for both acute attack treatment and prevention of chronic cluster headache; occipital nerve stimulation has been studied but has only very-low-quality evidence and no formal recommendation. Both are specialist-directed, not primary-care or community-pharmacy decisions.[3]
Special Populations
Pregnancy
Data specific to cluster headache in pregnancy are very limited, so management leans on general principles and migraine-pregnancy safety data for shared drugs. Oxygen is safe throughout pregnancy and remains first-line. Sumatriptan has the largest pregnancy-safety experience of any triptan (from migraine data) and can reasonably be used when needed. Verapamil should be used only if genuinely necessary and with specialist involvement -- data in cluster headache prevention specifically are limited. Lithium is best avoided, particularly in the first trimester, given an increased risk of fetal cardiac malformation (Ebstein anomaly); if lithium cannot be avoided, this requires specialist (obstetric/psychiatric or neurology) co-management throughout pregnancy, not a routine primary-care decision.
Breastfeeding
Oxygen and sumatriptan are considered compatible with breastfeeding. Verapamil is generally compatible with monitoring. Lithium transfers into breast milk and carries a real risk of infant toxicity -- avoid, or use only with specialist supervision and infant monitoring.
Cardiac disease and older adults
Verapamil is contraindicated in significant AV block, sick sinus syndrome (without a pacemaker), and decompensated heart failure, and needs particular caution when combined with other rate-limiting or negative-inotropic drugs (beta-blockers, diltiazem); ECG monitoring is especially important in this group. Triptans carry the usual contraindications in significant cardiovascular disease and uncontrolled hypertension. Oxygen has no cardiovascular contraindications, which makes it a particularly valuable first-line option when triptans or verapamil are limited by cardiac disease.[3]
Renal impairment
Lithium requires more cautious dosing and closer level monitoring in renal impairment given reduced clearance and narrow therapeutic index; verapamil does not require renal dose adjustment and is generally preferred if renal impairment limits lithium use.
Smokers
The great majority of patients with cluster headache are current or former smokers. Raise smoking cessation as part of overall care, but do not delay or withhold effective acute or preventive treatment while addressing it.[2]
Monitoring & Follow-Up
- Verapamil ECG schedule: baseline ECG before starting; repeat ECG once the daily dose reaches 400 mg, and again about a week after every further dose increase beyond that -- continue periodic ECGs on a stable maintenance dose, particularly at doses above 480 mg/day, since arrhythmias can develop even after a period of good tolerance.[2][3]
- Lithium monitoring: baseline renal and thyroid function before starting; periodic renal/thyroid function and serum lithium trough levels thereafter, targeting 0.4-0.8 mmol/L and never exceeding 1.2 mmol/L. Ask specifically about tremor, GI upset, and confusion at each follow-up as early signs of toxicity.[2]
- Track attack frequency, bout duration, and remission with a headache diary at every follow-up -- this is what determines both whether preventive therapy is working and when it is reasonable to begin tapering it.
- Once a patient has been in sustained remission beyond their usual bout length, taper verapamil (or lithium) gradually over 2-4 weeks rather than stopping abruptly or continuing indefinitely by default; chronic cluster headache patients may need indefinite preventive therapy, individualized to the patient.[2]
- Reassess for chronification (progression from episodic to chronic cluster headache, seen in up to 12% of episodic patients) if bouts are becoming longer, more frequent, or remissions shorter over time.[3]
- Screen for mood and suicidal ideation at follow-up during any active bout, not only at initial diagnosis.[3]
Common Errors to Avoid
- Treating cluster headache as "severe migraine" and reaching for oral triptans or migraine-style stepped analgesia instead of oxygen and an injectable/intranasal triptan -- the two diseases need different drugs.[2]
- Delivering oxygen through a nasal cannula instead of a non-rebreather mask, or at an inadequate flow rate/duration, and then concluding oxygen "doesn't work" for this patient.
- Using an oral triptan as routine acute therapy -- too slow for the attack's natural course, and only weakly supported by evidence.[3]
- Starting verapamil without a baseline ECG, or continuing to escalate the dose without the required follow-up ECGs at 400 mg/day and beyond.[2]
- Stopping an effective preventive (verapamil or lithium) abruptly rather than tapering over 2-4 weeks once sustained remission is achieved.
- Substituting a proven migraine preventive (a beta-blocker, for example) for verapamil on the assumption that any migraine preventive will work in cluster headache -- many do not.[3]
- Using a prolonged, unpaired course of oral corticosteroids as if it were a maintenance preventive, rather than a short bridge alongside verapamil titration.
- Missing a secondary cause on first presentation by treating an atypical case (abnormal exam, onset after 60, poor response to oxygen/triptan) as routine cluster headache without imaging.[3]
- Confusing cluster headache with paroxysmal hemicrania or SUNCT/SUNA and prescribing the wrong first-line treatment as a result -- these conditions do not all respond to the same drugs.[4]
- Not asking directly about suicidal ideation during an active bout.[3]
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation, including cardiac, renal, and hepatic status and pregnancy. Select any drug name to open its complete Pharmasist Drug Database page.
Oxygen (100%) has no Pharmasist Drug Database page (it is a medical gas, not a prescription drug product) but is first-line acute therapy: at least 12 L/min (up to 15 L/min) via a non-rebreather mask for 15-20 minutes. No cardiovascular contraindications, no drug interactions, no medication-overuse ceiling.
Acute attack -- triptans
Only injectable and intranasal formulations are appropriate for cluster headache -- onset is too slow with oral tablets for a 15-180 minute attack.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Sumatriptan (subcutaneous) | 6 mg SC; max 2 doses/24h | Injection-site reaction, flushing, warm sensation, chest/neck/jaw tightness, paresthesia | Avoid within 24h of ergotamine/DHE or another triptan; avoid with MAOIs | Fastest-onset acute option -- most patients pain-free within 5-20 minutes. |
| Zolmitriptan (intranasal) | 5 mg intranasal, may increase to 10 mg | Bitter taste, chest tightness, paresthesia | Avoid within 24h of ergotamine/DHE or another triptan; avoid with MAOIs | Slower onset than SC sumatriptan; a reasonable alternative when self-injection is not tolerated. |
| Sumatriptan (intranasal) | 20 mg intranasal | Bitter taste, chest tightness | Avoid within 24h of ergotamine/DHE or another triptan; avoid with MAOIs | Less trial evidence than intranasal zolmitriptan. |
| Dihydroergotamine (DHE) | 1 mg SC or IM, up to 3 times daily | Nausea, vasoconstriction, chest tightness, leg cramps, cold extremities | Contraindicated with triptans within 24h and with potent CYP3A4 inhibitors | Second-line injectable option when triptans are contraindicated or ineffective; watch for vasoconstriction-related side effects. |
Transitional (bridge) therapy
Reserved primarily for high-frequency episodic cluster headache (more than 2 attacks/day); always paired with a maintenance preventive being titrated in parallel, not used alone.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Prednisone | 60-100 mg PO once daily x ~5 days, then taper over 1-2 weeks; keep the total course well under a month | Hyperglycemia, insomnia, mood change, fluid retention; Cushingoid effects with prolonged/repeated courses | Additive hyperglycemic effect with other agents affecting glucose | Stops a high-frequency bout quickly while verapamil is titrated to an effective dose. |
| Methylprednisolone (greater occipital nerve block) | Local injection, ipsilateral to the pain, +/- a local anesthetic (e.g., lidocaine) | Local injection-site pain; rare cutaneous atrophy or alopecia with repeated superficial injection | None of note for the local route | Effective transitional option; can be repeated if effective. |
Preventive therapy -- first- and second-line
Verapamil is the preventive of choice; lithium is second-line. Many proven migraine preventives (e.g., beta-blockers) are not effective in cluster headache.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Verapamil | Start 80 mg PO TID; increase by 80 mg every 1-2 weeks; target at least 240 mg/day (commonly up to 480 mg/day, occasionally higher under cardiology supervision) | Constipation, ankle edema, gingival hyperplasia; bradycardia, PR-interval prolongation, AV block at higher doses | Avoid grapefruit/grapefruit juice (CYP3A4 inhibition raises levels -- case reports of complete heart block); additive bradycardia with beta-blockers/diltiazem; may enhance lithium excretion | Baseline ECG mandatory. Repeat ECG at 400 mg/day and roughly a week after every further increase. Taper over 2-4 weeks once in sustained remission -- do not stop abruptly. |
| Lithium carbonate | Start 300 mg PO BID; may increase to 300 mg TID after ~1 week if no response | Tremor, GI upset (nausea, diarrhea), polyuria; toxicity with narrow therapeutic index (confusion, ataxia, lethargy) | NSAIDs (including indomethacin) raise lithium levels and can cause toxicity; verapamil may enhance lithium excretion | Target trough level 0.4-0.8 mmol/L; do not exceed 1.2 mmol/L. Baseline and periodic renal/thyroid function required. 2nd-line to verapamil; particularly considered in chronic cluster headache. |
Preventive therapy -- add-on / alternative options (weaker evidence)
Consider when verapamil and lithium are inadequate, not tolerated, or contraindicated; typically specialist-guided.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Topiramate | Start 25 mg, titrate slowly; target at least 100 mg/day | Paresthesia, cognitive slowing, weight loss, nephrolithiasis, teratogenicity | May reduce hormonal contraceptive efficacy at higher doses | Open-label evidence only in cluster headache. Contraindicated in pregnancy. |
| Melatonin | 10 mg PO nightly | Drowsiness | Additive sedation with other CNS depressants | Modest evidence from a single small randomized trial; low-risk adjunct, mainly studied in episodic cluster headache. |
| Galcanezumab | 300 mg SC monthly | Injection-site reaction, nasopharyngitis | None significant | Licensed specifically for episodic cluster headache -- a chronic cluster headache trial did not show benefit over placebo. |
Evidence note: Drug inventory, dosing, and the verapamil ECG-monitoring protocol reflect Becker's Canadian Headache Society-hosted review[2] and the 2023 European Academy of Neurology guideline on cluster headache treatment[3].
References
- The International Classification of Headache Disorders, 3rd edition — Cephalalgia, Headache Classification Committee of the International Headache Society (IHS). Cephalalgia 2018;38(1):1-211
- Cluster Headache: Conventional Pharmacological Management — Headache, Werner J. Becker (University of Calgary and Alberta Health Services), hosted as guidance by the Canadian Headache Society. Headache 2013;53(7):1152-1163
- European Academy of Neurology guidelines on the treatment of cluster headache — European Journal of Neurology, European Academy of Neurology Task Force (May A, Evers S, Goadsby PJ, et al.). Eur J Neurol 2023;30(10):2955-2979
- Phenotypic and treatment outcome data on SUNCT and SUNA, including a randomised placebo-controlled trial — Cephalalgia (Weng HY, Cohen AS, Schankin C, Goadsby PJ). Cephalalgia 2018;38(9):1554-1563
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.