Dry Mouth (Xerostomia)
Clinical Snapshot
Xerostomia — commonly called dry mouth — is the subjective sensation of oral dryness, distinct from hyposalivation (also called salivary gland hypofunction), which is an objectively measurable reduction in salivary flow. The two frequently occur together but do not always correlate: some patients report a persistently dry mouth despite a measured salivary flow rate in the normal range, while others have objectively reduced flow — sometimes marked — with little or no subjective complaint until dental or mucosal complications appear.[1][2] Objective hyposalivation is generally defined as an unstimulated salivary flow rate of ≤0.1 mL/min, or a chewing-stimulated flow rate of ≤0.7 mL/min measured over 5 minutes.[3] A patient's report of dryness is what drives a visit and a treatment plan, but it is hyposalivation — the true reduction in the protective volume of saliva bathing the teeth and mucosa — that drives the downstream dental and mucosal complications this chapter covers.
Saliva does far more than keep the mouth moist. It forms the protective pellicle on enamel, buffers and neutralizes the acids produced by cariogenic bacteria and by food, supplies the calcium and phosphate needed to remineralize early enamel lesions, contains antibacterial and antifungal proteins, and provides the lubrication and enzymatic activity needed for chewing, swallowing, speech, and taste.[4][2] When salivary flow drops, oral pH falls, acid-producing bacteria such as Streptococcus mutans and Lactobacillus proliferate unchecked, and the mouth loses both its buffering capacity and its ability to repair early demineralization — the mechanism underlying the sharply elevated caries risk covered in Complications.[4]
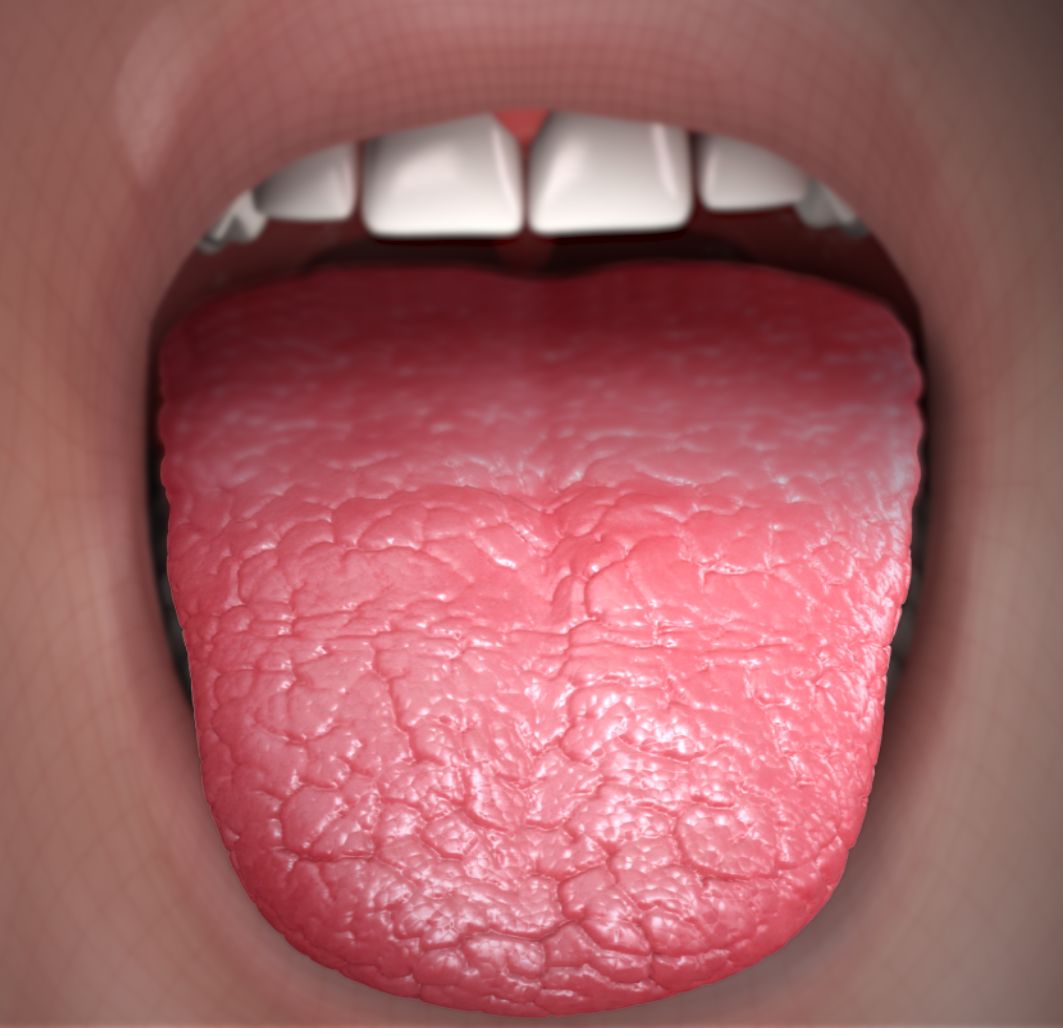
Xerostomia is common, and becomes more common with each additional problem a patient's medication list accumulates. A 2018 systematic review and meta-regression pooling 29 studies estimated the global prevalence of dry mouth at 22% (95% CI 17-26%).[5] Medications are the single most common cause — more so than any disease process — which is precisely why this is a pharmacist-relevant condition and not simply a dental one; a careful medication review is often both the diagnostic clue and the first line of treatment.[4][1] Sjögren syndrome, the classic autoimmune cause, is estimated to affect roughly 1% of Canadians — more than 430,000 people, 90% of them women — and remains widely underdiagnosed.[6]
Every patient presenting with dry mouth deserves a medication review before anything else. If a xerogenic drug can be safely stopped, switched to a lower-burden alternative, or moved to a different time of day, that intervention treats the actual cause — every other measure in this chapter manages the symptom around it.
Recognize the Condition
What patients report
Patients describe a dry, sticky, or "cottony" feeling in the mouth; a persistent need to sip water, especially at night or while speaking; difficulty chewing dry foods (crackers, toast) without liquid; difficulty swallowing (dysphagia) or a sensation that food sticks; altered or diminished taste (dysgeusia); a burning sensation of the tongue or oral mucosa; bad breath; and, in denture wearers, a poorly retained or newly uncomfortable denture that previously fit well.[1][2] Speech can become effortful, and some patients report frequent lip-cracking or objects (a straw, an oral appliance) sticking to the mucosa.
What you find on examination
Look for a dry, dull, or frankly fissured tongue; pale, dry, and friable oral mucosa that may stick to a gloved finger or tongue depressor; reduced or absent salivary pooling in the floor of the mouth; scant, thick, or ropy saliva rather than the thin, freely flowing saliva of a well-hydrated mouth; angular cheilitis (cracking at the corners of the mouth); and erythematous or white patches consistent with oral candidiasis, discussed further in Complications.[1][4] A simple bedside check: gently palpate or "milk" the major salivary glands (parotid, submandibular) and watch for flow at the duct opening — reduced or absent flow supports a genuine hyposalivation component rather than subjective dryness alone.
Onset pattern is a genuine diagnostic clue
Acute/rapid onset vs. chronic/progressive onset
Acute or rapid onset (days)
Think of a newly started or recently increased xerogenic medication, acute dehydration or fluid restriction, uncontrolled hyperglycemia, an acute viral illness, or the start of head and neck radiation. This pattern should prompt an immediate medication and hydration review rather than being assumed to be "just getting older."
Chronic, gradual onset (months to years)
Think of cumulative medication burden (particularly anticholinergic burden from several lower-risk drugs taken together), progressive Sjögren syndrome or another autoimmune sialadenitis, chronic mouth breathing, or long-standing poorly controlled diabetes. This pattern warrants the systemic red-flag screen in Red Flags and Referral.
Risk Factors
Medications — by far the most common cause
More medications are linked to xerostomia than to almost any other adverse effect in this platform's library, and a new or increased xerogenic drug — or simply the cumulative burden of several lower-risk drugs taken together — is the most likely explanation for a new complaint of dry mouth.[1][4] The classes below account for the great majority of drug-induced cases; see Drug Tables for a fuller reference list.
- Anticholinergics/antimuscarinics — the mechanistically most direct cause: these drugs block muscarinic receptors on the salivary acinar cells themselves, directly shutting off the parasympathetic signal that drives secretion. Examples include oxybutynin and tolterodine (overactive bladder), atropine and hyoscine butylbromide (antispasmodics), and inhaled ipratropium.[1]
- First-generation antihistamines — carry substantial anticholinergic activity in addition to H1 blockade; diphenhydramine is the prototype. Second-generation antihistamines cause meaningfully less dryness and are a reasonable substitute where clinically appropriate.[1]
- Tricyclic antidepressants (TCAs) — among the most anticholinergic drugs in common use; amitriptyline is a prototypical high-risk example. SSRIs and SNRIs (e.g., fluoxetine, citalopram, venlafaxine, duloxetine) also commonly cause xerostomia, but generally less severely than a TCA at an equivalent therapeutic effect.[1]
- Antipsychotics — both older and newer agents, including olanzapine, quetiapine, risperidone, and haloperidol, through combined anticholinergic and antihistaminergic activity.[1]
- Opioids — morphine, oxycodone, and the class generally, through a central effect on the salivary nuclei that reduces parasympathetic outflow to the glands, distinct from direct peripheral anticholinergic blockade.[1]
- Diuretics — hydrochlorothiazide and furosemide, largely through a volume-depletion effect on salivary output rather than a direct glandular mechanism — adequate hydration counseling is particularly relevant here.[1]
- Antihypertensives, especially clonidine — clonidine, a centrally acting alpha-2 agonist, is one of the most reliably xerogenic antihypertensives in practice, through reduced central sympathetic/parasympathetic outflow to the glands; diuretics (above) and, to a lesser extent, beta-blockers also contribute.[1]
- Decongestants — pseudoephedrine and other alpha-adrenergic agonists cause vasoconstriction of the glandular blood supply, reducing the substrate available for secretion — a genuinely common, easily overlooked over-the-counter contributor.[1]
- Chemotherapy agents — many cytotoxic regimens damage salivary acinar tissue directly, on top of any mucositis produced by the same treatment; the resulting hyposalivation can be severe and, particularly when combined with head and neck radiation, protracted or permanent.[4][1]
Xerostomia risk is cumulative. A patient taking four or five only mildly xerogenic drugs together — for example, an antihistamine, a diuretic, and an opioid — can develop clinically significant dryness even though no single agent would be flagged in isolation. Total xerogenic burden, not any one drug, is often the real target of a medication review.
Non-medication causes
- Sjögren syndrome — a chronic autoimmune exocrinopathy in which lymphocytic infiltration progressively destroys the salivary and lacrimal glands, producing xerostomia together with dry eyes (keratoconjunctivitis sicca); it is the classic non-drug cause and the one most likely to need rheumatology involvement (see Red Flags and Referral and Special Populations).[7][2]
- Head and neck radiation therapy — direct radiation injury to the major salivary glands, particularly the parotids, that can produce severe and sometimes permanent hyposalivation depending on the radiation field and dose.[4][1]
- Diabetes mellitus, particularly when poorly controlled — through osmotic diuresis and microvascular changes affecting glandular perfusion.[4][1]
- Dehydration from any cause — inadequate fluid intake, vomiting, diarrhea, fever, or excessive caffeine/alcohol intake.
- Mouth breathing — from chronic nasal obstruction, allergic rhinitis, or obstructive sleep apnea, particularly with unhumidified CPAP use — evaporates oral moisture independent of glandular function.
- Aging — glandular tissue does undergo some age-related change, but the dominant driver of xerostomia in older adults is the cumulative medication burden that comes with age, not aging of the glands itself; do not attribute a new complaint to age alone before completing a medication review.[4]
- Other autoimmune and systemic diseases: lupus, scleroderma, and graft-versus-host disease following stem cell transplantation.[4]
- HIV infection and hepatitis C — both are recognized, less common causes of salivary gland dysfunction.[4][1]
- Hormonal changes — menopause and pregnancy are both associated with a modest increase in reported dry mouth.[1]
- Cannabis use, salivary gland aplasia, and direct nerve damage (surgical or traumatic) to the glands' innervation are less common but recognized causes.[1]
Red Flags & Refer
Most xerostomia is straightforward drug-induced or age/polypharmacy-related dryness that pharmacists can manage directly with the measures in this chapter. The findings below point toward a systemic disease, an acute process, or a complication that needs specific referral rather than routine dry-mouth counseling.
- Dry eyes alongside dry mouth — a gritty, sandy, or burning sensation in the eyes, especially together with joint pain, unexplained fatigue, or other autoimmune symptoms, particularly in a woman in her 40s-60s. Symptoms persisting more than 3 months warrant discussing Sjögren syndrome with the patient's physician and considering rheumatology referral; the average time to diagnosis is reported at up to 5 years, largely because this pattern goes unrecognized.[8][7]
- Signs of oral candidiasis — creamy white plaques that wipe off (pseudomembranous) or diffuse erythema of the palate/tongue (erythematous), particularly under a denture — needs antifungal treatment, not just more saliva substitute (see Pharmacologic Management and Complications).
- Rapid, severe-onset dryness — especially with systemic symptoms (fever, vomiting, confusion, marked thirst) — suggests an acute process (significant dehydration, new severe hyperglycemia, an acute illness) rather than routine chronic xerostomia, and needs prompt medical assessment rather than dry-mouth counseling alone.
- Unilateral salivary gland swelling or pain, or a firm/fixed mass in a gland — this is not the pattern of ordinary xerostomia and needs assessment for obstruction (a stone), infection (sialadenitis), or a salivary gland tumour.
- Dysphagia significant enough to affect nutrition, hydration, or that raises aspiration concern — refer to the treating physician and consider a speech-language pathology assessment rather than managing with dry-mouth measures alone.
- Rapidly progressing dental caries, or new caries in a previously low-risk patient — confirms the need for the intensive fluoride/dental-surveillance plan in Non-Pharmacologic Management, and warrants a dental referral if the patient does not already have regular dental care.
Assessment & Diagnosis
History
Take a complete and current medication list, including over-the-counter products, herbal products, and cannabis use, and anything started or changed in the weeks before symptom onset — this single step resolves the majority of cases. Characterize onset (sudden vs. gradual), severity, and functional impact (eating, speaking, sleep), and ask specifically about associated dry eyes, joint pain, fluid intake, caffeine/alcohol/tobacco use, mouth breathing/snoring, diabetes control, and any history of head and neck radiation or chemotherapy.[8][4]
Examination
Examine the oral mucosa, tongue, and floor of the mouth for the findings described in Recognize the Condition (dryness, fissuring, reduced pooling, candidiasis, angular cheilitis), assess denture fit if applicable, and palpate the major salivary glands for swelling, tenderness, or an asymmetric mass.[1]
Objective salivary flow testing — a specialist/dental measurement, not routine pharmacy practice
Where the diagnosis is unclear or systemic disease is suspected, a dentist, oral medicine specialist, or rheumatologist may formally measure salivary flow: an unstimulated flow rate of ≤0.1 mL/min, or a chewing-stimulated flow rate of ≤0.7 mL/min over 5 minutes, is considered abnormally low (true hyposalivation).[3] This objective step is what separates hyposalivation from purely subjective xerostomia, and is one of the criteria used in formally diagnosing Sjögren syndrome (see below).
Differentiating the major causes
| Feature | Drug-induced | Sjögren syndrome | Radiation-induced | Diabetes-related | Dehydration/mouth breathing |
|---|---|---|---|---|---|
| Onset | Temporally linked to a new/changed drug, or gradual with polypharmacy | Gradual, over months to years | During or shortly after a course of head/neck radiation | Gradual, tracks with glycemic control | Rapid (dehydration) or positional/nocturnal (mouth breathing) |
| Associated features | None specific beyond the causative drug's own profile | Dry eyes, joint pain, fatigue, other autoimmune features | Mucositis, altered taste, a documented radiation field | Polyuria, polydipsia, other diabetes symptoms | Thirst, dizziness (dehydration); snoring, daytime fatigue (mouth breathing) |
| Key next step | Medication review — trial of switching/stopping/timing change | SS-A/SS-B antibodies, ANA; rheumatology referral | Managed with the oncology/dental oncology team | Blood glucose/HbA1c, glycemic optimization | Rehydration; ENT/sleep assessment for mouth breathing |
When laboratory or specialist workup is warranted
A straightforward case with an obvious causative medication and no red flags does not need laboratory testing — the "investigation" is the medication review itself. Pursue further workup when Red Flags and Referral criteria are met: SS-A (anti-Ro) and SS-B (anti-La) antibodies plus antinuclear antibody if Sjögren syndrome is suspected (present in roughly 70% and 40% of Sjögren patients respectively), with formal diagnosis requiring rheumatology involvement and, where needed, ophthalmologic testing (Schirmer test, ocular staining) and/or a minor salivary gland (lip) biopsy; check blood glucose/HbA1c if diabetes is suspected but not yet diagnosed.[8]
Treatment Targets
- Relieve the subjective symptoms of dryness and restore the patient's ability to eat, speak, and sleep comfortably.
- Stimulate residual salivary gland output wherever meaningful gland function remains, rather than relying on substitution alone.
- Prevent the specific dental and mucosal complications hyposalivation causes — dental caries, oral candidiasis, and denture-related problems — rather than treating symptoms in isolation from these downstream risks.
- Identify and, wherever clinically appropriate, minimize the causative agent — this is the single highest-value pharmacist action in this chapter, and the only intervention that addresses the underlying cause rather than the symptom.
- Recognize and refer for further workup any patient whose presentation suggests Sjögren syndrome or another systemic disease, rather than treating indefinitely as simple drug-induced dryness.
- Set realistic expectations and a durable long-term management plan for patients with an irreversible cause (established Sjögren syndrome, completed head and neck radiation) where the underlying hyposalivation will not resolve.
Choose Initial Treatment
Start with the medication review — every time
Before recommending any product, review the full medication list for a xerogenic drug that is new, recently increased, or simply one of several contributing to cumulative burden (see Risk Factors). If a reasonable alternative with a lower xerogenic burden exists, or the dose/timing can be adjusted, discuss this with the prescriber before layering on symptomatic treatment. Never stop or switch a medication unilaterally — particularly an antipsychotic, antidepressant, or cardiac drug — without involving the prescriber; the goal is a collaborative medication review, not an independent substitution.
Build the plan in this order
Step 1 — always non-pharmacologic measures (hydration, sugar-free salivary stimulation, saliva substitutes, oral hygiene and fluoride) for every patient, regardless of cause — see Non-Pharmacologic Management. These measures are low-risk, symptomatic, and appropriate even while a causative-drug discussion with the prescriber is still in progress.[4][1]
Step 2 — if residual gland function is plausible and symptoms remain troublesome a trial of a sialogogue (pilocarpine — the only agent approved for this indication in Canada) is reasonable in patients with genuine residual salivary gland tissue capable of responding to stimulation — most clearly post-radiation xerostomia and Sjögren syndrome, the two indications actually studied and approved in this country.[9] Sialogogues are far less useful, and not indicated, when the gland tissue itself has been destroyed or is absent (e.g., very advanced Sjögren syndrome with minimal residual secretory tissue) — see Pharmacologic Management.[4]
Step 3 — for a drug-induced case where the causative agent cannot be changed (for example, an antipsychotic that is genuinely the best option for the patient's psychiatric stability) focus on Step 1 symptomatic/preventive measures and an intensified dental-surveillance and fluoride plan (see Non-Pharmacologic Management and Complications) rather than adding a sialogogue, which has not been studied for, and is not indicated in, purely drug-induced xerostomia with an intact but pharmacologically blocked gland.[9]
Step 4 — confirmed or strongly suspected oral candidiasis at any point treat with a topical or systemic antifungal (see Pharmacologic Management) — candidiasis will not resolve with saliva substitutes or a sialogogue alone.
Non-Pharmacologic Treatment
- Frequent small sips of water throughout the day and at the bedside overnight — genuinely more effective for comfort than infrequent large volumes, and the single most accessible first measure for every patient.[2]
- Sugar-free gum or lozenges, preferably xylitol-based, chewed or sucked several times daily — mechanically stimulates residual salivary flow in patients who still have functioning gland tissue, and xylitol itself cannot be fermented by cariogenic bacteria, adding a direct anti-caries benefit distinct from the saliva-stimulation effect.[4][2]
- Gentle salivary gland massage (massaging over the parotid and submandibular glands) — a simple, low-cost adjunct some patients find helpful for residual gland stimulation.[2]
- Saliva substitutes — carboxymethylcellulose- or mucin-based sprays, gels, or rinses provide symptomatic lubrication and some antibacterial enzyme activity; they do not stimulate gland output and are appropriate even when little or no residual gland function remains.[4][1]
- Avoid caffeine, alcohol (including alcohol-containing mouthwash), tobacco, and dry/salty/spicy foods, all of which worsen oral dryness and mucosal irritation.[1]
- Humidifier use, particularly overnight — reduces evaporative moisture loss, and is especially relevant for mouth breathers and CPAP users without integrated humidification.
- Meticulous, more frequent oral hygiene and dental care — gentle brushing with a soft-bristled brush and fluoride toothpaste at least twice daily, daily flossing, and dental visits every 3-4 months rather than the usual 6-12 months, given the markedly elevated caries risk.[4][2]
- Daily high-concentration fluoride — a prescription-strength 5,000 ppm fluoride toothpaste, and professionally applied 5% sodium fluoride varnish every 1-3 months (monthly for severe xerostomia) — is core caries-prevention therapy in this population, not an optional extra; see Complications and Pharmacologic Management.[4]
- Where relevant, address mouth breathing directly — ENT assessment for nasal obstruction, or a sleep assessment and CPAP humidification review for suspected obstructive sleep apnea.
- For denture wearers: reassess denture fit and consider a denture adhesive or a soft reline, since a previously well-fitting denture can become poorly tolerated once salivary lubrication is lost.[4]
Special Populations
Older adults
Age itself is a minor contributor compared with the cumulative medication burden that accompanies it — polypharmacy, and specifically cumulative anticholinergic burden across several drugs, is the dominant driver of xerostomia in this group.[4] A xerostomia complaint in an older adult is a genuine deprescribing opportunity: review the full list for lower-xerogenic-burden alternatives (e.g., a second-generation antihistamine instead of diphenhydramine, an SSRI/SNRI instead of a TCA where clinically appropriate) before defaulting to symptomatic treatment alone.
Sjögren syndrome
Confirm the patient has an established multidisciplinary care plan — rheumatology (primary coordinating role), dental, and eye care, with follow-up in each every 6 months.[8] Canada-specific access note pilocarpine is currently the only Health Canada-approved sialogogue for Sjögren-related xerostomia; cevimeline was never granted market authorization in Canada, and the Special Access Programme pathway that had allowed limited access closed after Health Canada's final refusal in September 2022 — patients seeking cevimeline specifically now need to travel to the United States to obtain it.[10] Set this expectation clearly and early rather than letting a patient discover it only after asking a prescriber for cevimeline by name.
Head and neck cancer / radiation and chemotherapy patients
Xerostomia here can be severe and, depending on the radiation field and dose, permanent — this population needs the most intensive version of the caries-prevention plan in Non-Pharmacologic Management (custom fluoride trays/carriers, more frequent varnish, remineralizing pastes) rather than a standard recommendation.[4] Pilocarpine is specifically approved and studied for this indication and is a reasonable trial once mucositis from active treatment has settled enough for oral intake of the tablet.[9]
Diabetes
Optimizing glycemic control is itself part of the xerostomia treatment plan in this group, alongside the standard measures above.[4]
Pregnancy and breastfeeding
Pilocarpine's safety in human pregnancy has not been established, and animal studies have shown reproductive toxicity — use only if the expected benefit outweighs the potential risk, and it is not recommended in women of childbearing potential who are not using contraception.[9] Pilocarpine is excreted into breast milk in animal studies at concentrations similar to plasma; because the effect on a nursing infant is not established, the decision to continue breastfeeding or continue pilocarpine should be individualized.[9] Non-pharmacologic measures (hydration, xylitol gum, saliva substitutes, fluoride) remain first-line and are appropriate throughout pregnancy and breastfeeding.
Pediatrics
Pilocarpine's safety and effectiveness have not been studied in children under 18 years of age — it is not a pediatric option.[9] Xerostomia in children more often reflects mouth breathing, a stimulant or anticholinergic medication (e.g., for ADHD or overactive bladder), or, rarely, juvenile Sjögren syndrome; non-pharmacologic measures and a medication review remain the mainstay.
Cardiovascular disease, asthma, and glaucoma
Pilocarpine is contraindicated in uncontrolled asthma and whenever miosis is undesirable (acute iritis, narrow-angle/angle-closure glaucoma).[9] Use with caution and close medical supervision in significant cardiovascular disease, since pilocarpine's dose-related cardiovascular effects include hypotension, hypertension, bradycardia, and tachycardia, and pulmonary edema has been reported as a toxicity complication.[9]
Hepatic and renal impairment
Patients with mild-to-moderate hepatic impairment should start pilocarpine at a reduced dose and titrate gradually as tolerated; it is not recommended in severe hepatic impairment (Child-Pugh C) except with extreme caution if clinically necessary.[9] No reliable pharmacokinetic data exist for oral pilocarpine in renal impairment — use with caution, since pilocarpine can theoretically increase ureteral smooth muscle tone and precipitate renal colic in a patient with nephrolithiasis.[9]
Monitoring & Follow-Up
- Reassess subjective symptom relief, functional impact (eating, speaking, sleep), and treatment adherence at every follow-up — most patients are managing this chronically, so periodic check-ins matter more than a single assessment.
- Repeat the medication review at every follow-up, not just at the initial visit — new xerogenic drugs are added over time, and cumulative burden can change even when no single new "culprit" drug appears.
- For patients trialing pilocarpine (or bethanechol): allow up to 12 weeks before concluding a trial has failed, since relief can build gradually over this period; monitor for the expected dose-related adverse effects (sweating, GI upset, flushing) and titrate or reduce the dose as needed.[9]
- Increase dental visit frequency to every 3-4 months for any patient with confirmed or suspected hyposalivation, rather than the standard interval — this is a monitoring recommendation, not only a treatment one.[4][2]
- For patients with confirmed Sjögren syndrome: confirm ongoing 6-month follow-up with rheumatology, dental, and eye care as coordinated by the rheumatologist.[8]
- Screen for new oral candidiasis, new or accelerating caries, and denture problems at each encounter — these are the complications this whole management plan exists to prevent, and their appearance signals the current plan needs to intensify, not just continue unchanged.
Common Errors to Avoid
- Attributing a new complaint of dry mouth to "just getting older" without first completing a full medication review — age is a minor contributor next to cumulative drug burden.[4]
- Missing an easily switchable or timing-adjustable causative drug because the medication review stopped at the most obviously anticholinergic agent rather than considering the patient's total burden.
- Not asking about dry eyes and joint pain in a patient with unexplained chronic dry mouth — this is the single easiest missed opportunity to catch Sjögren syndrome years earlier than it is typically diagnosed.[8]
- Recommending an alcohol-containing mouthwash or sugared mints/candies to a xerostomic patient — both actively worsen the problem this plan is trying to solve.
- Treating saliva substitutes as a substitute for fluoride — they provide comfort but no meaningful caries protection on their own.[4]
- Assuming cevimeline is a routine, accessible Canadian option — it is not currently approved or marketed in Canada.[10]
- Recommending or implying a patient should stop an antipsychotic, antidepressant, or cardiac medication on their own without prescriber involvement — the medication review is a collaborative conversation with the prescriber, never a unilateral pharmacy substitution.
- Dismissing new oral white patches or erythema as "just more dryness" rather than recognizing and treating oral candidiasis specifically.
- Starting or continuing a pilocarpine trial in a patient with uncontrolled asthma or narrow-angle glaucoma — both are contraindications, not relative cautions.[9]
- Overlooking denture-related complications (poor retention, mucosal irritation) in an edentulous patient, who cannot report "tooth" symptoms but is still at real risk from hyposalivation.
Clinical Decision Algorithm
Drug Tables
How to use this table: pilocarpine and bethanechol doses require patient-specific confirmation (cardiovascular, hepatic, and renal status; contraindications). Antifungal and fluoride product doses are per the product's own Drug Database monograph or manufacturer labeling. Select any linked drug name to open its complete Pharmasist Drug Database page.
Sialogogues (Salivary Stimulants)
Appropriate only where meaningful residual salivary gland tissue remains — see Choose Initial Treatment.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Pilocarpine | Usual adult dose: 5 mg PO 3-4 times daily; titrate to 10 mg/dose if needed and tolerated, maximum 30 mg/day Hepatic impairment: Start at a reduced dose, titrate cautiously; not recommended in severe impairment | Dose-dependent hyperhidrosis (up to 68% at 30 mg/day), nausea, rhinitis, flushing, urinary frequency, dizziness, headache | Caution with beta-blockers (conduction disturbances); additive with other parasympathomimetics; may antagonize concurrent anticholinergic drugs; a CYP2A6 inhibitor (in vivo interaction with CYP2A6 substrates, e.g. coumarin, cannot be ruled out) | The only sialogogue approved and marketed in Canada. Approved specifically for radiation-induced xerostomia and Sjögren syndrome, not for xerostomia generally. Contraindicated in uncontrolled asthma and narrow-angle glaucoma. Response may take up to 12 weeks. |
| Cevimeline | U.S. labeled dose (not a Canadian option): 30 mg PO 3 times daily | Cholinergic profile similar to pilocarpine — sweating, nausea, rhinitis, GI upset | Similar cautions to pilocarpine (additive parasympathomimetic effects, caution with beta-blockers) | Not approved or marketed in Canada — Health Canada denied market authorization in 2022 and the Special Access Programme pathway has since closed. Confirm with the patient that obtaining it now requires travel to the United States before discussing it as an option. |
| Bethanechol | Dosing: Individualized — no standard xerostomia-specific regimen; discuss with the prescriber | Cholinergic effects — sweating, GI cramping, urinary urgency, flushing | Additive with other cholinergic drugs; caution with beta-blockers for the same conduction-disturbance concern as pilocarpine | An off-label alternative when pilocarpine is not tolerated or is contraindicated; the evidence base specific to xerostomia is considerably smaller than for pilocarpine. |
Antifungals for Oral Candidiasis
Xerostomia is a major risk factor for oral candidiasis (see Complications) — treat confirmed or strongly suspected infection directly rather than relying on saliva substitutes alone.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Nystatin (oral suspension) | Adults: Per the product's own Drug Database monograph — swish and swallow, or swish and spit | GI upset, taste disturbance | None significant at standard doses | First-line topical option. Also disinfect any denture concurrently — a contaminated denture is a common source of reinfection. |
| Clotrimazole (troches) | Adults: Per the product's own Drug Database monograph | GI upset, mild transient LFT elevation | None significant at standard doses | Alternative topical option. Troches require adequate saliva to dissolve fully — counsel patients with severe hyposalivation that this may work less well for them specifically. |
| Fluconazole | Adults: Per the product's own Drug Database monograph | GI upset, rare hepatotoxicity, QTc prolongation | Numerous CYP450 interactions (e.g., warfarin, phenytoin, many others) — review carefully | Reasonable for infection not responding to a topical agent, or when severe hyposalivation limits troche dissolution. |
Topical Fluoride and Saliva Substitutes
Core, ongoing therapy for every patient with hyposalivation — not optional adjuncts. See Complications for why caries risk is so sharply elevated.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Topical fluoride gel/rinse (0.4% stannous fluoride or 1.1% neutral sodium fluoride) | Home use: Nightly application per product labeling | Fluorosis risk only with excessive or inappropriate use — not a concern at recommended adult dosing | None significant | Daily home use; pair with professionally applied 5% sodium fluoride varnish every 1-3 months (monthly if severe). |
| Saliva substitutes (carboxymethylcellulose- or mucin-based spray/gel/rinse) | All patients: As needed for symptom relief | Generally well tolerated; taste preference varies by product | None significant | Symptomatic relief only — does not stimulate gland output; appropriate even with no residual gland function. |
Representative Causative Medications, by Class
Not an exhaustive list — hundreds of medications are linked to xerostomia. These are the classes and representative agents a pharmacist encounters most often; see Risk Factors for the full class-by-class discussion.
| Drug | Class | Xerostomia mechanism |
|---|---|---|
| Oxybutynin | Anticholinergic/antimuscarinic | Direct muscarinic receptor blockade on salivary acinar cells |
| Tolterodine | Anticholinergic/antimuscarinic | Direct muscarinic receptor blockade on salivary acinar cells |
| Atropine | Anticholinergic/antimuscarinic | Direct muscarinic receptor blockade on salivary acinar cells |
| Ipratropium (inhaled) | Anticholinergic/antimuscarinic | Direct muscarinic receptor blockade; some systemic absorption despite the inhaled route |
| Diphenhydramine | First-generation antihistamine | Combined H1 blockade and substantial anticholinergic activity |
| Amitriptyline | Tricyclic antidepressant | Strong anticholinergic activity — among the most xerogenic drugs in common use |
| Fluoxetine | SSRI | Serotonergic effects on salivary secretion — generally less severe than a TCA |
| Citalopram | SSRI | Serotonergic effects on salivary secretion — generally less severe than a TCA |
| Venlafaxine | SNRI | Combined serotonergic/noradrenergic effects on salivary secretion |
| Duloxetine | SNRI | Combined serotonergic/noradrenergic effects on salivary secretion |
| Olanzapine | Antipsychotic (atypical) | Combined anticholinergic and antihistaminergic activity |
| Quetiapine | Antipsychotic (atypical) | Combined anticholinergic and antihistaminergic activity |
| Risperidone | Antipsychotic (atypical) | Combined anticholinergic and antihistaminergic activity |
| Haloperidol | Antipsychotic (typical) | Anticholinergic activity |
| Morphine | Opioid | Central effect on the salivary nuclei reducing parasympathetic outflow to the glands |
| Oxycodone | Opioid | Central effect on the salivary nuclei reducing parasympathetic outflow to the glands |
| Hydrochlorothiazide | Thiazide diuretic | Volume-depletion effect on salivary output |
| Furosemide | Loop diuretic | Volume-depletion effect on salivary output |
| Clonidine | Central alpha-2 agonist (antihypertensive) | Reduced central sympathetic/parasympathetic outflow to the glands — one of the most reliably xerogenic antihypertensives |
| Pseudoephedrine | Decongestant (alpha-adrenergic agonist) | Vasoconstriction of the glandular blood supply, reducing the substrate available for secretion |
References
- Xerostomia (Dry Mouth) — American Dental Association. ADA Oral Health Topics, last updated March 4, 2026
- Dry Mouth — Sjögren's Society of Canada. Sjögren's Society of Canada, What is Sjögren's?
- Sjögren Disease — American Dental Association. ADA Oral Health Topics, last updated August 21, 2023
- Caries Prevention for Patients with Dry Mouth — Journal of the Canadian Dental Association (Su N, Marek CL, Ching V, Grushka M). J Can Dent Assoc 2011;77:b85
- How Common is Dry Mouth? Systematic Review and Meta-Regression Analysis of Prevalence Estimates — Brazilian Dental Journal (Agostini BA, Cericato GO, da Silveira ER, Nascimento GG, Costa FDS, Thomson WM, Demarco FF). Braz Dent J 2018;29(6):606-618
- About Sjögren's Disease — Sjögren's Society of Canada. Sjögren's Society of Canada, What is Sjögren's?
- Sjögren syndrome — CMAJ (Mavragani CP, Moutsopoulos HM). CMAJ 2014;186(15):E579-E586
- Diagnosis — Sjögren's Society of Canada. Sjögren's Society of Canada, What is Sjögren's?
- SALAGEN (Pilocarpine Hydrochloride Tablets) Product Monograph — Health Canada Drug Product Database / Amdipharm Limited, distributed by Methapharm Inc.. Date of Revision: February 28, 2020
- Cevimeline/Sholyne Update — Sjögren's Society of Canada. Sjögren's Society of Canada Blog, October 25, 2022
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.