Kawasaki Disease
Clinical Snapshot
Kawasaki disease (KD) is an acute, self-limited but potentially serious systemic vasculitis of small- and medium-sized arteries, of unknown cause, that predominantly affects young children — most commonly those under 5 years of age — and can occur throughout childhood.[1] It is a leading cause of acquired heart disease in children in Canada, a status it holds specifically because of its particular predilection for the coronary arteries: coronary artery aneurysm formation is the source of essentially all serious long-term morbidity and, rarely, mortality from this disease, and preventing it is the central organizing goal of every intervention described in this chapter.[1]
The diagnostic backbone: fever plus 4 of 5 principal features. Kawasaki disease is diagnosed clinically. The required core feature is fever for at least 5 days, together with at least 4 of 5 principal clinical features — bilateral non-exudative conjunctival injection, oral mucous membrane changes, a polymorphous rash, extremity changes, and cervical lymphadenopathy. See Recognize the Condition for the full criteria table, including the important incomplete/atypical presentation that is especially common — and especially dangerous to miss — in infants under 6 months.[1]
Left untreated, roughly 25% of children with Kawasaki disease develop coronary artery aneurysms.[2] The single most important treatment goal is to reduce that risk: intravenous immunoglobulin (IVIG), given ideally within the first 10 days of fever onset, reduces the aneurysm risk to under 5% — making timely recognition and treatment, more than any other factor, the central clinical priority in this chapter.[1] Acute-phase treatment pairs IVIG with aspirin — an anti-inflammatory, higher dose during the febrile phase, transitioning to a low, antiplatelet dose once fever resolves — a deliberate, guideline-endorsed exception to the usual pediatric avoidance of aspirin due to Reye syndrome, addressed explicitly in Common Errors to Avoid.[1] Patients at higher risk of IVIG resistance, or with IVIG-refractory disease, may receive adjunctive corticosteroids or the biologic infliximab; long-term management is then stratified by the severity of any coronary artery involvement found on echocardiography.[3]
Recognize the Condition
Epidemiology
In Canada, the incidence of Kawasaki disease is highest in preschoolers, at 19.6 to 26.0 cases per 100,000 children under age 5, and it represents a leading cause of acquired childhood heart disease nationally.[1] The cause remains unknown; a triggering infection or environmental exposure in a genetically susceptible child is suspected, but no single causative organism has been identified.[1]
The classic diagnostic criteria — complete Kawasaki disease
Complete (classic) Kawasaki disease is diagnosed by fever for at least 5 days plus at least 4 of the 5 principal clinical features below; diagnosis can be made as early as day 4 of fever if 4 or more principal features are already present.[1]
| Required core feature | Description |
|---|---|
| Fever | Present for at least 5 days (diagnosis may be made on day 4 if ≥4 principal features are already present) |
| Principal clinical feature (≥4 of 5 required) | Description |
|---|---|
| Bilateral conjunctival injection | Non-exudative (non-purulent), typically with perilimbal sparing — see photograph below |
| Oral mucous membrane changes | Strawberry tongue, and red, cracked, swollen lips — see photograph below |
| Polymorphous rash | Variable morphology; typically truncal, non-vesicular |
| Extremity changes | Erythema and edema of the palms/soles in the acute phase; periungual desquamation in the subacute phase (roughly 2-3 weeks after fever onset) — see photograph below |
| Cervical lymphadenopathy | At least 1.5 cm, typically unilateral — usually the least consistently present of the 5 features |

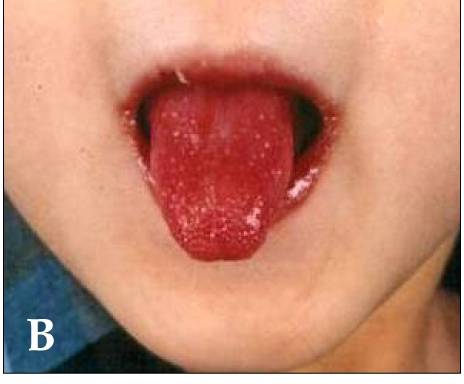

Incomplete (atypical) Kawasaki disease — a genuinely important and clinically tricky variant
Fewer classic features does not mean lower risk — often the opposite. Incomplete/atypical Kawasaki disease is defined as fever for at least 7 days in infants under 12 months, OR fever for at least 5 days with only 2-3 principal features, together with elevated inflammatory markers (ESR ≥40 mm/h or CRP ≥30 mg/L) and either supportive echocardiographic findings or at least 3 of 6 supplemental laboratory criteria.[1] This presentation is more common in infants under 6 months — and these same infants are at higher risk of coronary artery complications despite the less classic clinical picture: patients age ≤6 months (or with a coronary artery Z-score ≥2.5 at diagnosis) carry an approximately 16-fold increased likelihood of coronary artery aneurysm development.[3] This is precisely the group most likely to be missed or diagnosed late, exactly when they are at greatest risk — maintain a high index of suspicion for prolonged, unexplained fever in a young infant even when fewer than 4 principal features are present.[1][3]
Risk Factors
- Age under 5 years — the incidence peaks in preschoolers, at 19.6-26.0 cases per 100,000 children under age 5 in Canada.[1]
- Age under 12 months, and particularly under 6 months — the highest-risk group both for an incomplete/atypical presentation and, independently, for coronary artery aneurysm development (an approximately 16-fold increased risk versus older children).[3]
- No single causative organism or environmental exposure has been confirmed; a preceding infectious or environmental trigger in a genetically susceptible child is suspected but not established, and Kawasaki disease is not considered contagious.[1]
- A coronary artery Z-score of 2.5 or higher already present at diagnosis independently identifies a higher-risk group regardless of age.[3]
- Male sex and East Asian ancestry are recognized epidemiologic associations in the broader international literature, though this chapter's Canadian incidence figures reflect the general Canadian pediatric population.[1]
Red Flags & Refer
This entire chapter is fundamentally about timely recognition — prolonged, unexplained fever in a young child should prompt consideration of Kawasaki disease rather than being dismissed as a routine viral illness. Refer promptly for pediatric (or pediatric cardiology/emergency) evaluation for:
- Fever for 5 or more days (7 or more days in an infant under 12 months) without a clear alternative explanation, particularly with any of the 5 principal clinical features present — even if fewer than 4 are present, especially in an infant under 6 months (see Recognize the Condition for incomplete/atypical Kawasaki disease).[1]
- Any suspected case — do not wait for echocardiography or laboratory confirmation before arranging urgent assessment; echocardiography should never delay treatment once the clinical picture is convincing.[1]
- IVIG resistance — persistent or recrudescent fever 24-36 hours or more after completing an IVIG infusion — which requires prompt reassessment and second-line therapy rather than simply waiting it out (see Treatment Failure/Next Step).[1]
- Signs suggesting Kawasaki disease shock syndrome or macrophage activation syndrome (hypotension, poor perfusion, or a markedly more severe/atypical illness course) — these require urgent escalation and specialist-directed intensified therapy (see Special Populations).[1]
- New or worsening cardiac symptoms in a child with a known coronary artery aneurysm (chest pain, syncope, pallor, or irritability with diaphoresis in a young child, which can represent myocardial ischemia) — evaluate emergently.[3]
The pharmacist's role here is recognition and prompt escalation, not outpatient reassurance — the aneurysm-prevention benefit of treatment is time-dependent, and delay has a real, measurable cost.[1]
Assessment & Diagnosis
Kawasaki disease is a clinical diagnosis, supported by labs and echocardiography
Diagnosis rests primarily on the fever-plus-principal-features pattern described in Recognize the Condition. Laboratory testing and echocardiography support the diagnosis — particularly for incomplete/atypical presentations — and guide risk stratification, but should not delay treatment once the clinical picture is convincing.[1]
Laboratory findings
No single laboratory test is diagnostic. Supportive findings include elevated inflammatory markers (ESR ≥40 mm/h, CRP ≥30 mg/L), which are used both to support the diagnosis of incomplete Kawasaki disease and to help confirm the incomplete-KD supplemental laboratory criteria (which also include anemia for age, a white blood cell count ≥15,000/mm³, sterile pyuria, elevated ALT, low albumin, and a platelet count ≥450,000/mm³ after day 7 of illness).[1] Thrombocytosis is a particularly characteristic finding in the subacute phase — the platelet count is usually normal in the first several days of illness and rises, sometimes markedly, as the acute inflammation begins to resolve, typically in the second or third week.[1]
Echocardiography — obtain it, but never let it delay treatment
Echocardiography at diagnosis is essential for assessing coronary artery involvement using standardized Z-score calculations, but should never delay initiation of therapy in a clinically convincing presentation.[1] Coronary artery aneurysms can continue to develop for up to 4 to 6 weeks after disease onset, which is why serial follow-up echocardiography (not a single study at diagnosis alone) is essential — see Monitoring & Follow-Up for the specific schedule.[1]
| Coronary artery Z-score category | Definition |
|---|---|
| No involvement | Z-score always <2 |
| Dilatation only | Z-score ≥2 to <2.5 |
| Small aneurysm | Z-score ≥2.5 to <5 |
| Medium aneurysm | Z-score ≥5 to <10 |
| Large/giant aneurysm | Z-score ≥10, or an absolute internal diameter ≥8 mm |
Cardiac prognosis worsens with increasing coronary artery size; this classification directly determines the long-term antithrombotic strategy described in Monitoring & Follow-Up.[1][3]
Differential diagnosis
Consider and exclude alternative explanations for prolonged fever with a mucocutaneous/rash picture, particularly measles, scarlet fever, staphylococcal or streptococcal toxin-mediated illness (toxic shock syndrome), drug hypersensitivity reactions, juvenile idiopathic arthritis, and — in the appropriate epidemiologic context — multisystem inflammatory syndrome in children (MIS-C). A clear alternative diagnosis with a typical course argues against Kawasaki disease, but persistent or atypical fever should prompt reassessment rather than premature closure.[1]
Treatment Targets
- Reduce systemic inflammation during the acute febrile phase.
- Reduce the risk of coronary artery aneurysm formation — the single most important treatment goal, since this is the complication that drives essentially all long-term cardiac morbidity, and rarely mortality, from this disease.[1]
- Treat within the defined early time window from fever onset (ideally within the first 10 days) to maximize the aneurysm-risk reduction achievable with IVIG.[1]
- Identify patients at higher risk of IVIG resistance or more severe disease early, so that adjunctive therapy can be added up front rather than only after resistance has already occurred.[3]
- Prevent thrombosis in any coronary artery abnormality that does develop, with antiplatelet or, where indicated, anticoagulant therapy matched to aneurysm severity.
- Support the family through an acute, frightening illness and its monitoring requirements with clear, honest education — including specifically addressing aspirin/Reye syndrome concerns (see Common Errors to Avoid).
Choose Initial Treatment
IVIG plus aspirin — the central acute pharmacotherapy
Every confirmed or strongly suspected case: give IVIG 2 g/kg as a single IV infusion, ideally within the first 10 days of fever onset — earlier treatment is more effective at preventing coronary complications, a genuinely time-critical point. Treatment given after day 10 is still beneficial if fever, inflammation, or aneurysm formation is ongoing, and should not be withheld solely because the 10-day window has passed.[1]
Pair IVIG with aspirin at an anti-inflammatory dose during the acute febrile phase — either 30-50 mg/kg/day PO divided every 6 hours (up to 80-100 mg/kg/day in some protocols), or low-dose aspirin from the outset; both approaches are currently accepted.[1]
The high-dose-to-low-dose aspirin transition — a specific and important protocol detail
Once the child has been afebrile for 24-48 hours and inflammatory markers are improving, transition aspirin from the anti-inflammatory dose to a low, antiplatelet dose of 3-5 mg/kg PO once daily, continued for a minimum of 4-6 weeks or longer if any coronary artery abnormality is identified.[1]
A deliberate exception to routine pediatric aspirin avoidance. Aspirin is normally avoided in febrile children because of the risk of Reye syndrome, particularly during varicella or influenza infection. Its use in Kawasaki disease is a specific, guideline-endorsed exception to that rule — not an oversight — and pharmacists should be prepared to explain this proactively, since it is a common point of parent/caregiver concern and even occasional prescriber hesitation. Monitor for concurrent varicella or influenza during the low-dose maintenance phase and switch to an alternative antiplatelet (clopidogrel or dipyridamole) if either occurs; children on long-term aspirin should also receive annual influenza vaccination.[1]
Adjunctive corticosteroids for higher-risk patients
For patients identified as being at higher risk of IVIG resistance by current risk-scoring approaches, or for IVIG-refractory disease, add an adjunctive corticosteroid: oral prednisone/prednisolone 2 mg/kg/day (maximum 60 mg/day), used consultatively and tapered per specialist direction, is the typical approach for up-front intensification or IVIG resistance; IV methylprednisolone 30 mg/kg (maximum 1000 mg/dose) is reserved specifically for the more severe presentations of Kawasaki disease shock syndrome or macrophage activation syndrome.[1] In this higher-risk/IVIG-resistant group, adding either a corticosteroid or infliximab reduces progression of coronary artery aneurysm size compared with IVIG alone — the evidence suggests that using one of the two matters more than which specific agent is chosen.[3]
Biologic and second-line options for IVIG-resistant disease
Infliximab is a well-established second-line option, alongside a second dose of IVIG or corticosteroids, for patients with IVIG-refractory disease — see Treatment Failure/Next Step for the full escalation pathway.[1][3]
Non-Pharmacologic Treatment
- Admit every patient with confirmed or strongly suspected Kawasaki disease for IVIG administration, monitoring, and baseline echocardiography.[1]
- Supportive care during the acute febrile phase: adequate hydration, and antipyresis with acetaminophen as needed alongside the anti-inflammatory aspirin dose.
- Confirm the child has been afebrile for at least 24-48 hours and is clinically improving before considering discharge, and confirm the aspirin dose has been (or is ready to be) transitioned to the low, antiplatelet dose.[1]
- Arrange the full serial echocardiography follow-up schedule before discharge — do not leave this to be arranged later (see Monitoring & Follow-Up).[1]
- Provide clear caregiver education before discharge: the deliberate, guideline-endorsed reason for using aspirin in this specific illness despite the usual Reye syndrome caution; the specific signs of varicella or influenza that should prompt a call and a switch to an alternative antiplatelet; the specific signs of IVIG resistance (recurring or persisting fever) that should prompt prompt reassessment rather than a wait-and-see approach; and, for any child found to have a coronary artery abnormality, honest counseling about the long-term follow-up and antithrombotic therapy that will be needed.[1]
- Defer live-virus vaccines (e.g. measles-mumps-rubella, varicella) for 11 months after high-dose IVIG, since IVIG can blunt the immune response to live vaccines; inactivated vaccines, including seasonal influenza vaccine, can proceed on the usual schedule and are specifically recommended for children remaining on long-term aspirin.[1]
- Involve pediatric cardiology early and continuously in any child with coronary artery involvement, and arrange psychological support for families navigating a frightening acute illness and, where relevant, an ongoing cardiac diagnosis.
Special Populations
Infants under 6 months
The single most important special population in this chapter. Infants under 6 months are more likely to present with incomplete/atypical Kawasaki disease (fewer than 4 principal features), yet carry an approximately 16-fold higher risk of coronary artery aneurysm development than older children.[3] This combination — a less classic presentation in the group at greatest risk — is precisely why these infants are more likely to be missed or diagnosed late. Maintain a low threshold to investigate prolonged, unexplained fever in this age group even without 4 principal features, and use the incomplete-KD criteria (fever ≥7 days plus elevated inflammatory markers and supportive echo/lab criteria) rather than waiting for a more classic picture to emerge.[1][3]
Kawasaki disease shock syndrome and macrophage activation syndrome
A minority of patients present with, or develop, a more severe, atypical course marked by hypotension and poor perfusion (Kawasaki disease shock syndrome) or hyperinflammatory macrophage activation syndrome. These patients require urgent escalation, intensive supportive care, and IV pulse methylprednisolone (see Choose Initial Treatment) rather than standard-dose adjunctive therapy alone.[1]
IgA deficiency
As with any IVIG indication, anaphylaxis is a recognized risk in patients with known IgA deficiency; screen where feasible and have the treating team plan accordingly.
Vaccination timing
Defer live-virus vaccines for 11 months after high-dose IVIG, since the antibody load can blunt the vaccine immune response; inactivated vaccines, including seasonal influenza vaccine, are not affected and influenza vaccination is specifically recommended for children remaining on long-term aspirin.[1]
Renal and hepatic considerations
Use IVIG cautiously in renal impairment, favouring a non-sucrose formulation and adequate hydration where feasible, consistent with IVIG use in any other indication. Aspirin should be used cautiously, with attention to bleeding risk and GI tolerability, in any child with a bleeding diathesis or significant hepatic impairment; there is no specific Kawasaki-disease-specific dose adjustment beyond standard pediatric practice.
Monitoring & Follow-Up
Echocardiography follow-up schedule
Obtain a baseline echocardiogram at diagnosis, without delaying treatment to do so, then repeat at 2 weeks and again at 4-6 weeks after disease onset, since aneurysms can continue to develop for up to 4-6 weeks.[1] In patients identified as high-risk (age ≤6 months, or a coronary artery Z-score ≥2.5 at diagnosis), repeat the echocardiogram again 2-3 days after the first study even if it was normal, and arrange outpatient follow-up at 1 week rather than the standard 1-2 week interval.[3]
Long-term management, stratified by coronary artery involvement
- No or minimal involvement (Z-score consistently <2.5) confirmed on follow-up echocardiography at 6-8 weeks: discontinue low-dose aspirin at that point and no further cardiology follow-up is generally needed.[1]
- Small-to-medium aneurysms (Z-score 2.5 to <10): continue low-dose aspirin long-term and maintain periodic cardiology follow-up. Small-to-moderate aneurysms typically regress within 1 year, though 1.5-3% of patients experience recurrent disease within 12 months.[1]
- Large/giant aneurysms (Z-score ≥10, or ≥8 mm absolute diameter): add anticoagulation — warfarin, a low-molecular-weight heparin, or a direct oral anticoagulant (DOAC) — to ongoing antiplatelet therapy, with long-term specialized cardiology follow-up; this is the highest-risk group for coronary thrombosis and long-term cardiac morbidity. A DOAC offers reduced monitoring requirements and fewer drug/food interactions than warfarin, where appropriate.[3] For a medium aneurysm where a documented thrombus has regressed, continuing anticoagulation rather than switching to antiplatelet therapy alone is a reasonable specialist-directed approach.[3]
Complications
Coronary artery aneurysm formation is the central complication of this disease, with the long-term risks of thrombosis, myocardial infarction, and (rarely) sudden cardiac death rising with aneurysm size, particularly for large/giant aneurysms.[3] Other recognized acute-phase complications include myocarditis, valvular regurgitation, and, uncommonly, Kawasaki disease shock syndrome or macrophage activation syndrome (see Special Populations). Most children with no or minimal coronary involvement have an excellent long-term prognosis.[1]
Common Errors to Avoid
- Withholding aspirin in a child with Kawasaki disease out of a general Reye-syndrome-related reflex against pediatric aspirin use — this is a specific, deliberate, guideline-endorsed exception, not an oversight, and should be explained proactively to concerned caregivers and, where needed, to hesitant prescribers.[1]
- Dismissing prolonged, unexplained fever in a young child — especially an infant under 6 months — as a routine viral illness without considering Kawasaki disease, particularly when fewer than 4 principal features are present; this is exactly the presentation most likely to be missed in the group at highest coronary risk.[1][3]
- Waiting for echocardiographic or laboratory confirmation before initiating IVIG in a clinically convincing presentation — treatment timing from fever onset is directly tied to aneurysm-risk reduction.[1]
- Forgetting to transition aspirin from the high, anti-inflammatory dose to the low, antiplatelet dose once the child becomes afebrile — continuing high-dose aspirin unnecessarily increases bleeding and GI risk without added benefit at that stage.[1]
- Treating a recurring or persisting fever after IVIG as simply "the same illness continuing" rather than recognizing it as IVIG resistance requiring prompt reassessment and second-line therapy.[1]
- Discontinuing low-dose aspirin, or relaxing echocardiography follow-up, before the full 4-6 week (or longer, if abnormalities are found) monitoring schedule is complete.[1]
- Giving a live-virus vaccine too soon after high-dose IVIG, which can blunt the vaccine response — defer for 11 months; inactivated vaccines, including influenza vaccine, are not affected.[1]
- Underestimating the long-term risk in large/giant coronary artery aneurysms, or failing to add anticoagulation to antiplatelet therapy when the Z-score threshold is met.[3]
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Disease-Modifying Acute Therapy
The essential acute pharmacotherapy for every confirmed or strongly suspected case — start as early as possible, ideally within 10 days of fever onset.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Immunoglobulin (Human) — IVIG | Standard dose: 2 g/kg IV as a single infusion | Aseptic meningitis, hemolytic anemia, anaphylaxis in IgA-deficient patients, rare acute kidney injury | May reduce the efficacy of live vaccines given within about 11 months of infusion | Reduces coronary artery aneurysm risk from roughly 25% (untreated) to under 5% when given within the first 10 days of fever onset. |
Aspirin — Acute (Anti-Inflammatory) and Maintenance (Antiplatelet) Dosing
A deliberate, guideline-endorsed exception to the usual pediatric avoidance of aspirin due to Reye syndrome — see Common Errors to Avoid.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Acetylsalicylic acid (ASA) — acute phase | Acute (anti-inflammatory) dose: 30-50 mg/kg/day PO divided every 6 hours (up to 80-100 mg/kg/day in some protocols) | GI upset, rare hepatotoxicity, tinnitus at high doses | Additive bleeding risk with other antiplatelet agents or anticoagulants | Continue at this anti-inflammatory dose until the child has been afebrile for 24-48 hours. |
| Acetylsalicylic acid (ASA) — maintenance phase | Maintenance (antiplatelet) dose: 3-5 mg/kg PO once daily | GI upset, bleeding risk | Additive bleeding risk with other antiplatelet agents or anticoagulants | Continue for a minimum of 4-6 weeks, or longer if any coronary artery abnormality is present; switch to clopidogrel or dipyridamole if varicella or influenza develops. |
Adjunctive and Second-Line Therapy — Higher IVIG-Resistance Risk or IVIG-Refractory Disease
Adding a corticosteroid or infliximab in this group reduces coronary aneurysm progression compared with IVIG alone; the specific choice among these options is specialist-directed.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Prednisone / prednisolone | Standard dose: 2 mg/kg/day PO, maximum 60 mg/day | Hyperglycemia, mood changes, GI upset, immunosuppression | Additive hyperglycemia with other agents affecting glucose control | Typical approach for up-front intensification in higher-risk patients, or for IVIG resistance; tapered per specialist direction. |
| Methylprednisolone sodium succinate (IV pulse) | Pulse dose: 30 mg/kg IV, maximum 1000 mg/dose | Hyperglycemia, hypertension, GI bleeding, adrenal suppression with repeated dosing | Additive hyperglycemia with other agents affecting glucose control | Reserved specifically for Kawasaki disease shock syndrome or macrophage activation syndrome — not routine adjunctive use. |
| Infliximab | Standard dose: 5 mg/kg IV single infusion, specialist-directed | Infusion reactions, infection risk, rare hepatotoxicity | Avoid with live vaccines; additive infection risk with other immunosuppressants | Second-line biologic option for IVIG-resistant/refractory disease, alongside a repeat IVIG dose or a corticosteroid. |
| Anakinra | Dose: Specialist-directed, weight-based | Injection-site reactions, infection risk, neutropenia | Additive infection risk with other immunosuppressants | A further-line option for refractory disease, particularly where hemoglobin has dropped more than 20 g/L after the first IVIG dose. |
Alternative Antiplatelet Agents (Reye-Syndrome-Related Aspirin Substitution)
Use in place of low-dose aspirin if ASA is contraindicated, or if the child develops varicella or influenza during the maintenance antiplatelet phase.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Clopidogrel | Dose: 1 mg/kg/day PO, maximum 75 mg/day, specialist-directed | Bleeding, GI upset, rare thrombocytopenia | Additive bleeding risk with other antiplatelet agents or anticoagulants | A reasonable substitute for low-dose ASA specifically when Reye syndrome risk factors are present. |
| Dipyridamole | Dose: Specialist-directed, weight-based | Headache, dizziness, GI upset | Additive bleeding risk with other antiplatelet agents or anticoagulants | An alternative antiplatelet agent where clopidogrel is not preferred or available. |
Anticoagulation — Large/Giant Coronary Artery Aneurysms Only
Reserved for the highest coronary-risk tier (Z-score ≥ 10, or ≥ 8 mm absolute diameter), added to ongoing antiplatelet therapy, with long-term specialized cardiology follow-up.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Warfarin | Dose: Specialist-directed, titrated to INR target | Bleeding, requires frequent INR monitoring, numerous drug/food interactions | Extensive — CYP2C9/VKORC1-mediated interactions with many co-administered drugs and foods high in vitamin K | The traditional standard for long-term anticoagulation in large/giant aneurysms; titrated to a specialist-directed INR target. |
| Enoxaparin | Dose: Specialist-directed, weight-based | Bleeding, injection-site bruising, rare heparin-induced thrombocytopenia | Additive bleeding risk with antiplatelet agents or anticoagulants | A low-molecular-weight heparin alternative to warfarin, particularly for bridging or shorter-term use. |
| Rivaroxaban | Dose: Specialist-directed, weight-based | Bleeding; fewer dietary interactions than warfarin | Additive bleeding risk with antiplatelet agents or anticoagulants; interacts with strong CYP3A4/P-glycoprotein inhibitors or inducers | A direct oral anticoagulant (DOAC) option offering decreased monitoring requirements and fewer drug/food interactions than warfarin, where appropriate for the patient. |
References
- Kawasaki disease: Practical guidance on diagnosis and management — Canadian Paediatric Society, Community Paediatrics Committee (Chen A, Rozenblyum E, Dahdah N, Lang B, Scuccimarri R, Lahiry P, Tam H, Chan M, Human A, Lee J, Wong P, Tsoukas P). Paediatr Child Health 2026;31(5):550-555
- Diagnosis, Treatment, and Long-Term Management of Kawasaki Disease: A Scientific Statement for Health Professionals From the American Heart Association — Circulation, American Heart Association (McCrindle BW, Rowley AH, Newburger JW, et al.). Circulation 2017;135(17):e927-e999
- Update on Diagnosis and Management of Kawasaki Disease: A Scientific Statement From the American Heart Association — Circulation, American Heart Association (Jone PN, Tremoulet A, Choueiter N, et al.). Circulation 2024;150(23):e481-e500
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.