Lyme Disease
Clinical Snapshot
Lyme disease is caused by the spirochete Borrelia burgdorferi, transmitted through the bite of an infected Ixodes (blacklegged) tick — Ixodes scapularis in most of Canada and the eastern/central United States, Ixodes pacificus on the Pacific coast. Transmission requires prolonged tick attachment, since the spirochete must migrate from the tick's gut to its salivary glands during feeding; risk rises sharply the longer an infected tick remains attached.[1] Left untreated, infection can progress from a localized skin infection at the bite site to disseminated disease affecting the nervous system, heart, and joints — but Lyme disease is highly treatable at every stage with the correct antibiotic and duration, and most patients recover fully once appropriately treated.[2]
Recognize the Condition
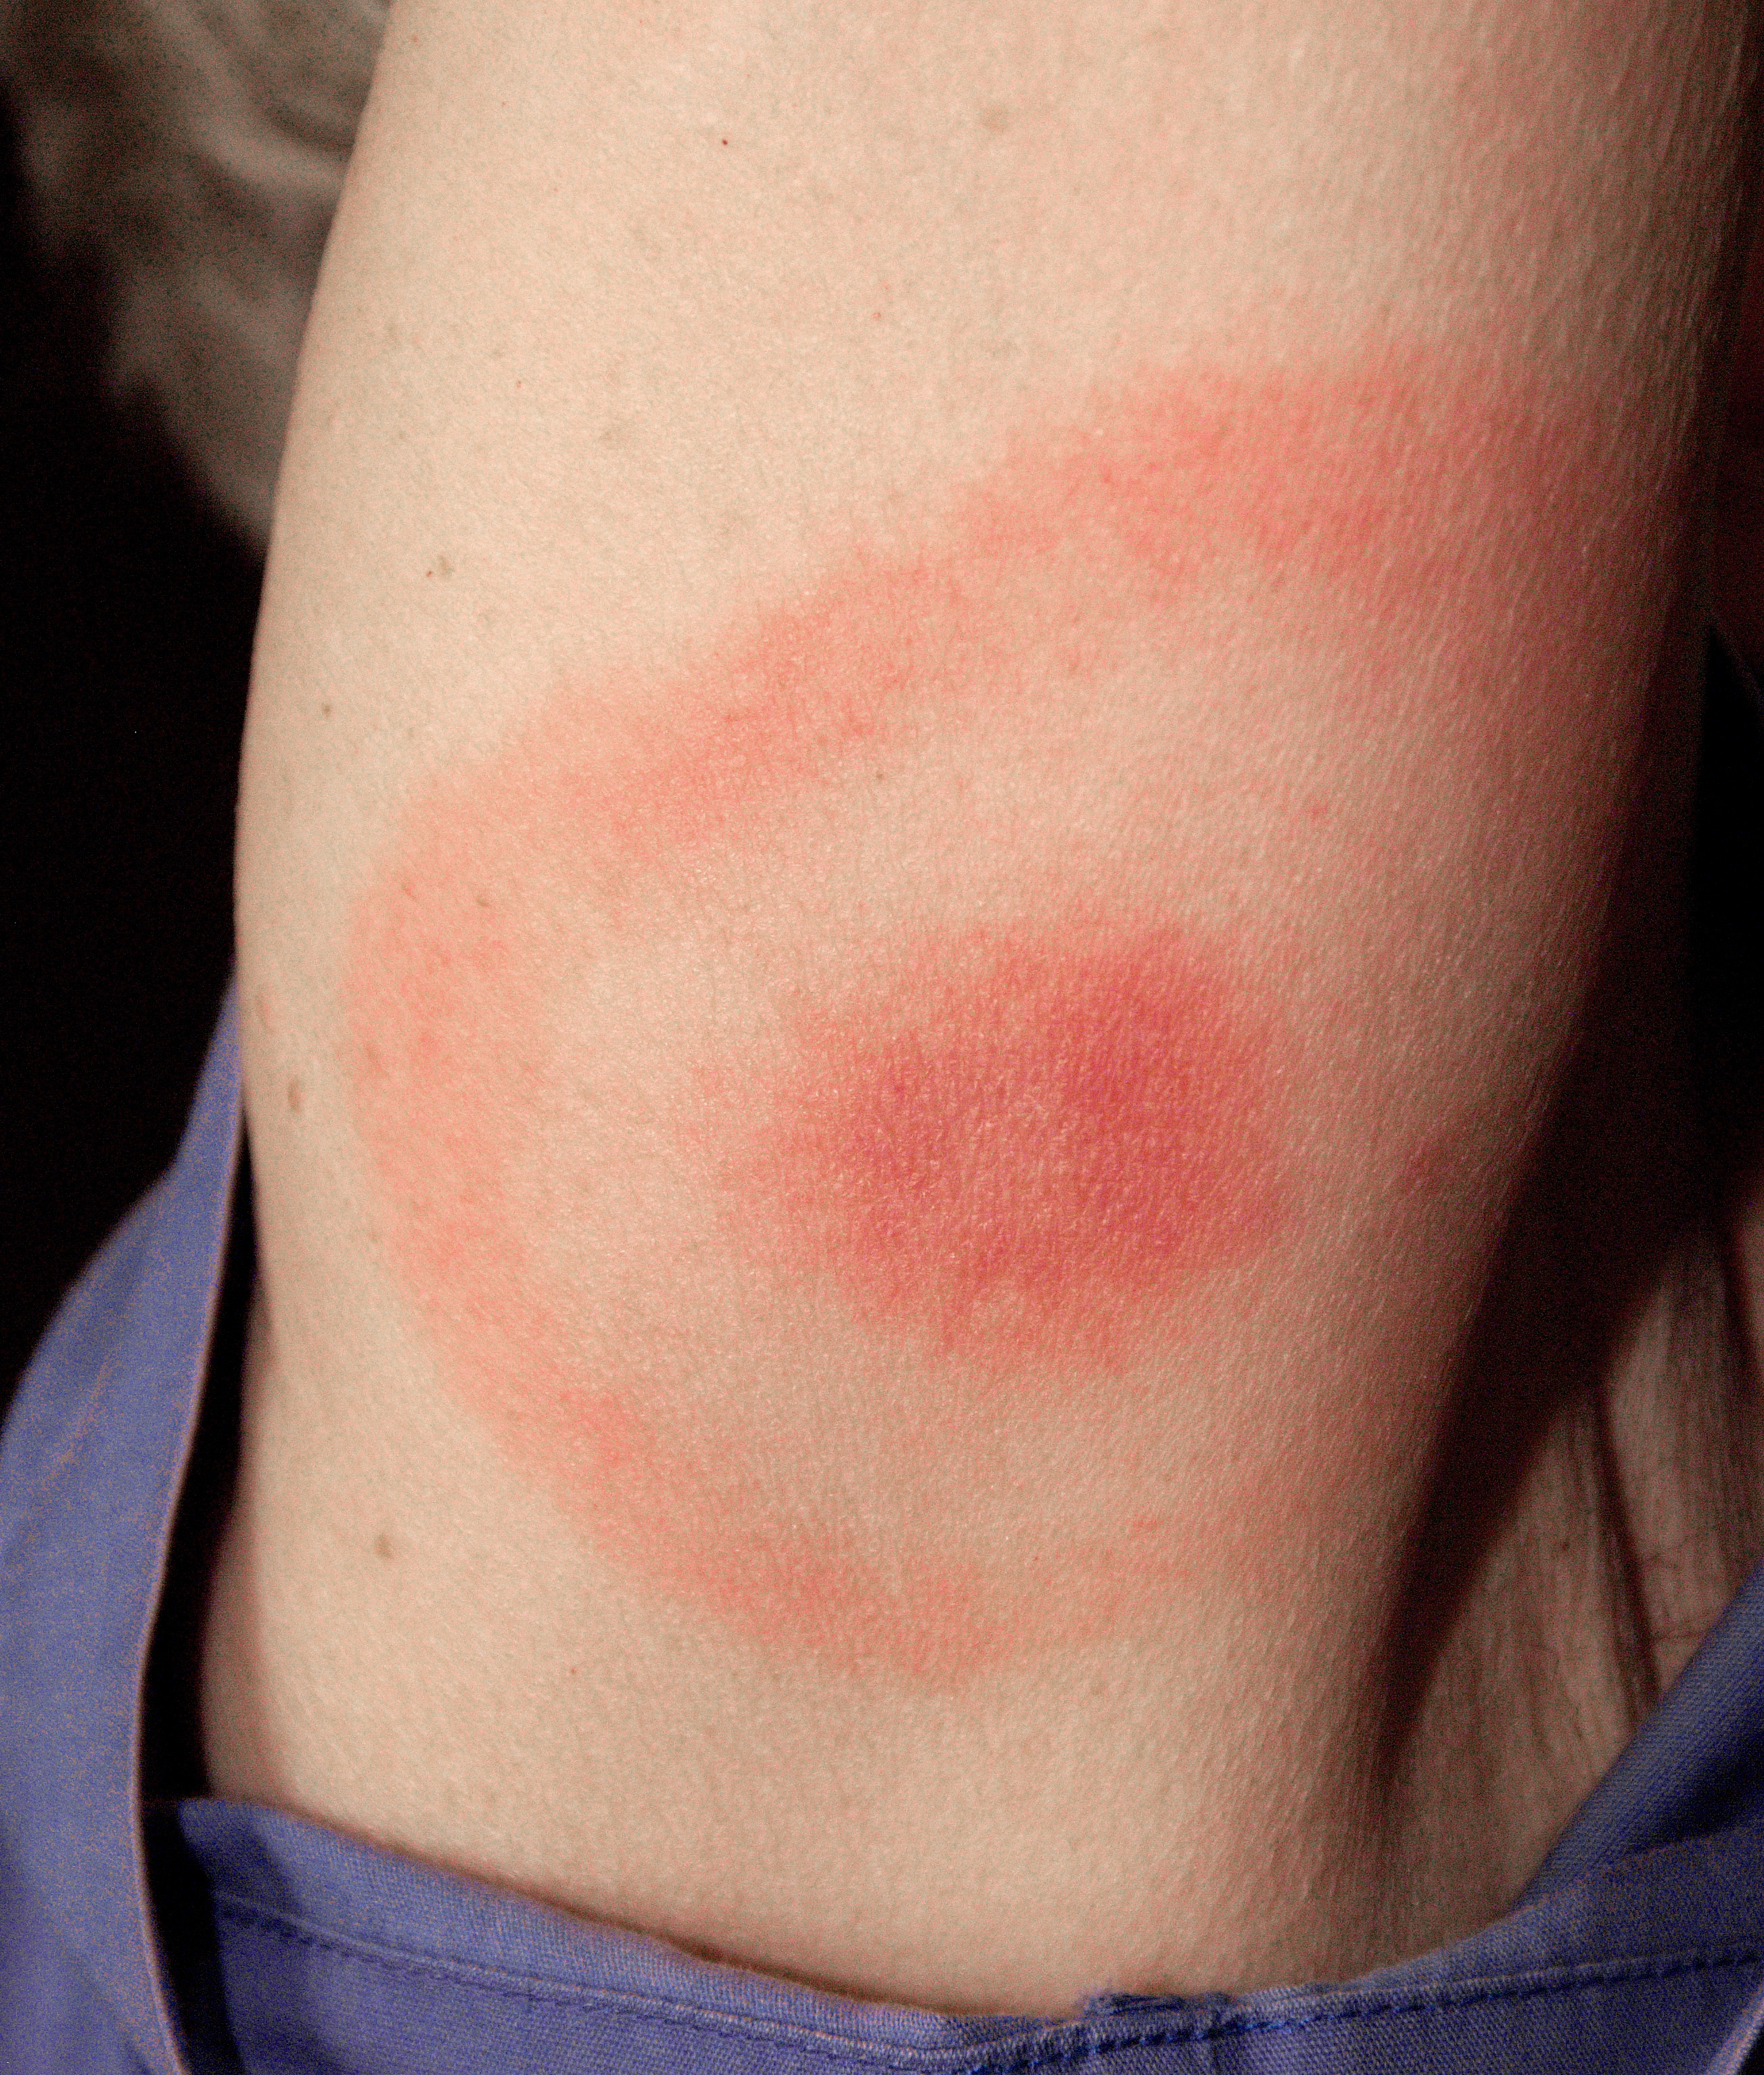
Erythema migrans (the presenting sign in most cases)
Appears at the site of the tick bite — commonly the groin, axilla, waist, back, or legs in adults, and the head or neck in children — and enlarges over days to reach a diameter of at least 5 cm. Morphology varies: many lesions are a uniform erythematous plaque, some show the classic "bull's-eye" appearance with central clearing, and others blister, become necrotic, or take on a bruise-like blue or purple hue. The lesion is non-tender and has well-defined margins; it may be pruritic or produce a stinging sensation. It can be accompanied by flu-like symptoms — fatigue, headache, myalgia, arthralgia, or low-grade fever.[1]
The 3 stages of Lyme disease
Early localized disease
Erythema migrans at the bite site, with or without mild systemic (flu-like) symptoms, and no evidence of dissemination to other organ systems.
Early disseminated disease
Occurs weeks to months after an untreated bite, once the spirochete has spread hematogenously.
- Skin: multiple secondary erythema migrans lesions, typically smaller than the primary lesion and appearing at sites distant from the bite; may fade and recur. Lymphocytomas (more common in children) or vaginal ulcers can occur.
- Neurologic: facial nerve palsy is the most common cranial neuropathy and can be bilateral; lymphocytic (aseptic) meningitis with headache lasting several days, neck pain, or listlessness, typically more indolent than viral meningitis; mononeuritis multiplex and meningoradiculitis (Bannwarth syndrome) occur mainly in adults; myelitis is rare.
- Cardiac: atrioventricular block of any degree — can be asymptomatic or present as dizziness, syncope, dyspnea, or palpitations — along with other ECG changes (T-wave abnormalities, ST changes, prolonged QTc), myopericarditis, and rarely cardiomyopathy.
- Ocular: conjunctivitis, uveitis/panophthalmitis, and rarely orbital myositis.
Late Lyme disease
Typically presents more than 3 months after the initial infection; specific skin lesions are rarely seen at this stage, so a high index of suspicion and careful exclusion of other chronic musculoskeletal/neurologic conditions is required.
- Musculoskeletal: asymmetric mono- or oligoarthritis, most often the knee or another large joint; subacute onset (over days); joint effusion is often disproportionate to pain; if untreated, can relapse and involve other joints over time.
- Neurologic: encephalopathy (impaired memory/concentration, usually with normal CSF) and chronic axonal polyneuropathy (distal paresthesias, reduced vibratory sensation, radicular pain, or an ataxic gait).
- Acrodermatitis chronica atrophicans: focal skin areas become edematous and erythematous, then progress to violaceous, atrophic changes — seen mostly in older adults and can be accompanied by peripheral neuropathy.
Risk Factors
- Outdoor activity — hiking, camping, gardening, hunting, or working — in wooded, brushy, or tall-grass areas, including backyards and playgrounds, not only remote wilderness.
- Residence in or travel to an established or expanding tick-endemic area of Canada — current risk areas include parts of southern and eastern Ontario, southern Quebec, Nova Scotia, New Brunswick, southeastern Manitoba, and southern British Columbia; risk-area boundaries continue to expand, so exposure cannot be excluded on geography alone outside these zones.[2]
- Highest activity for ticks (and therefore highest transmission risk) is spring through fall.
- Prolonged, unrecognized tick attachment — many patients never notice or recall the bite.
- Not using tick repellent or protective clothing when in tick habitat, or skipping a post-outdoor-activity tick check.
- Outdoor pets that are not checked for ticks before coming indoors.
Red Flags & Refer
Refer or escalate urgently for any of the following:
- Any degree of Lyme carditis with a PR interval ≥300 ms, or symptomatic carditis (dizziness, syncope, dyspnea, chest pain, palpitations) — admit for continuous cardiac monitoring; this is a risk factor for complete heart block and sudden death and may require a temporary pacemaker.[3]
- Suspected Lyme meningitis, radiculoneuropathy, or multiple cranial nerve involvement — needs prompt assessment and usually inpatient IV therapy.
- In a child with early disseminated Lyme disease and suspected meningitis: signs of raised intracranial pressure — headache worse in the morning or when lying flat, worsening with coughing/Valsalva/bending forward, or pulsatile tinnitus — need an urgent optic disc exam and visual acuity check, with escalation for specialist-directed intracranial pressure management if papilledema is found.
- Suspected septic arthritis (acute, high fever, a single very swollen and painful joint) rather than Lyme arthritis (which is usually subacute) — needs urgent joint aspiration and orthopedic assessment; do not treat empirically as Lyme arthritis without excluding this.
- Antibiotic-refractory Lyme arthritis — synovitis persisting 2 months or more after a completed course of IV ceftriaxone, or after 2 completed oral antibiotic courses — refer to rheumatology; further antibiotics are not indicated.
- A more severe or atypical systemic illness than expected for Lyme disease (unexplained thrombocytopenia, hemolytic features, high fever) in a patient with a compatible tick exposure — consider co-infection with another Ixodes-borne pathogen (anaplasmosis, babesiosis) and refer for further work-up.
- Pregnant or breastfeeding patients with disseminated, neurologic, or cardiac Lyme disease — needs combined infectious disease/obstetric management.
Assessment & Diagnosis
Differentiating erythema migrans from its common mimics
| Feature | Erythema migrans | Cellulitis | Nummular eczema | Tinea corporis | Insect bite / tick-bite hypersensitivity |
|---|---|---|---|---|---|
| Timing | 3-32 days after the bite (average 7-10 days), enlarges over days | Acute onset, often within 1-2 days | Gradual, unrelated to any bite; often recurrent | Gradual, unrelated to any bite | At the time of the bite or within hours; hypersensitivity reactions resolve within about 48 hours and do not expand |
| Tenderness | Non-tender; may be pruritic or have a stinging sensation | Tender, painful | Itchy, not tender | Itchy, not tender | Itchy, mildly tender at the papule only |
| Margins | Well-defined; may show central clearing ("bull's-eye"), or be uniformly erythematous, blistering, necrotic, or bruise-like | Poorly delineated, spreading, indistinct edge | Well-demarcated, coin-shaped, thickened/scaly | Raised, scaly, active border with central clearing | Small raised papule, sometimes with a central punctum; does not expand |
| Warmth / edema | Absent | Present — warm, edematous | Absent | Absent | Localized swelling at the bite only |
| Size | Reaches ≥5 cm diameter | Variable, can be large and spreading | Usually smaller, coin-sized, often multiple | Usually smaller than EM, may be multiple | Smaller than EM |
History
- Ask specifically about outdoor activity and exposure to wooded, brushy, or tall-grass environments — including gardens and residential yards — in or near an established or expanding Canadian risk area, and about travel to other endemic regions.
- A remembered tick bite is not required for diagnosis — many patients are unaware they were bitten.
- Characterize the timeline and morphology of any skin lesion(s), and ask about systemic symptoms (fever, fatigue, myalgia, arthralgia), neurologic symptoms (facial droop, headache, neck pain, paresthesias), and cardiac symptoms (palpitations, dizziness, syncope, dyspnea).
When a typical erythema migrans lesion needs no testing
Two-tier serologic testing — for atypical presentations, or disseminated/late disease
Use two-tier testing when the presentation is atypical, or when evaluating for early disseminated, neurologic, cardiac, or late (arthritis) disease: (1) a screening enzyme immunoassay (EIA), followed by (2) a confirmatory immunoblot (IB) only if the EIA is equivocal or positive. Do not order the immunoblot as a standalone first test — it must follow a positive or equivocal screening EIA. Sensitivity of the 2-tier assay is substantially higher in early disseminated, neurologic, or cardiac disease than in early localized disease, and highest in late-stage disease. If suspicion for early disseminated, neurologic, or cardiac Lyme disease remains high despite an initial negative test, repeat serology in 2-4 weeks.[2]
- Testing must be performed at an approved Canadian laboratory — reliability at unvalidated labs has not been established.
- Note any presumed European exposure explicitly on the requisition — European Lyme disease is caused by different Borrelia species (B. afzelii, B. garinii) and needs an alternative serologic panel to be detected.
- Do not use serology as a test of cure or to monitor treatment response — antibodies can persist for years after successful treatment and do not distinguish active from past infection.
Other investigations, and when they are not indicated
- Lumbar puncture: indicated for suspected meningitis, or unilateral facial nerve palsy accompanied by delirium, fever, or a severe/prolonged headache. Measure opening pressure. Expect lymphocytic pleocytosis with normal protein and glucose; PCR on CSF has very low sensitivity and should not be ordered routinely.
- Synovial fluid analysis: mainly used to exclude septic arthritis when the diagnosis is uncertain — cell counts alone do not reliably discriminate Lyme arthritis from septic arthritis. PCR for B. burgdorferi DNA can support the diagnosis but should not be used as a stand-alone test, and may remain positive after successful treatment.
- ECG: only for patients with symptoms of carditis (dyspnea, syncope, palpitations, chest pain) — not indicated routinely in asymptomatic early Lyme disease.
- Routine bloodwork (CBC, electrolytes): nonspecific and usually normal in Lyme disease; not useful for diagnosis.
Co-infection with other tick-borne pathogens
The same Ixodes ticks can transmit other pathogens whose presentations overlap with Lyme disease; consider co-infection in a patient with unexplained thrombocytopenia, hemolytic features, or more severe systemic illness than expected. Anaplasmosis (Anaplasma phagocytophilum) typically presents as an acute, nonspecific febrile illness with myalgia, malaise, headache, and cough, without a rash; laboratory features include thrombocytopenia, leukopenia, mild anemia, and elevated liver enzymes, diagnosed by PCR/NAAT early or serology later. Babesiosis (Babesia microti) presents as a nonspecific febrile illness with fatigue, chills, and headache, also without a rash; laboratory features include anemia, thrombocytopenia, and hepatitis, confirmed by intraerythrocytic parasites on blood smear or PCR. Borrelia miyamotoi, an Ehrlichia muris-like organism, and Powassan virus are additional possible co-infections to consider in an atypical or refractory presentation with the same geographic exposure.[1]
Treatment Targets
- Recognize and treat early localized disease (erythema migrans) promptly to prevent dissemination.
- Match the antibiotic agent, route, and duration to the specific clinical stage/manifestation — localized skin, neurologic, cardiac, or articular.
- Prevent Lyme disease after a genuinely high-risk tick bite using single-dose postexposure prophylaxis when criteria are met.
- Fully resolve neurologic, cardiac, and articular manifestations of disseminated or late disease.
- Avoid unnecessary prolonged or repeated antibiotic courses for symptoms not attributable to active infection.
Choose Initial Treatment
Early localized disease (erythema migrans)
1st line doxycycline 100 mg PO BID for 10 days in adults, or weight-based dosing in children of any age — short courses (≤21 days) are safe regardless of age, so doxycycline is no longer withheld under age 8.[1]
Equal-efficacy alternative — use in pregnancy, or when doxycycline is not tolerated or specifically avoided: amoxicillin PO for 14 days, or cefuroxime axetil PO for 14 days.
2nd line — use only when doxycycline, amoxicillin, and cefuroxime axetil are all contraindicated or not tolerated: azithromycin PO for 7 days; efficacy is lower than the other 3 options, so arrange closer follow-up to confirm response.
Postexposure prophylaxis after a tick bite
Offer a single dose of doxycycline only when all 3 criteria are met: the local infection rate in the tick population exceeds 20% (an established endemic area), the tick is identified as an Ixodes (blacklegged) species, and attachment lasted at least 36 hours (tick engorgement supports this when exact timing is unknown) — and only if the dose can be given within 72 hours of tick removal.[4]
Do not use amoxicillin for prophylaxis — its short half-life makes a single dose ineffective, and it has not been studied for this indication.
If any criterion is not met, or if timing is uncertain and the tick was not visibly engorged, use watchful waiting instead of prophylaxis — monitor for erythema migrans or a flu-like illness for up to 1 month.
Early disseminated disease — neurologic (neuroborreliosis)
Isolated facial nerve palsy, no other neurologic findings: doxycycline PO for 14-21 days (weight-based in children); amoxicillin or cefuroxime axetil PO for 14-21 days is an equal alternative. Antibiotics do not speed recovery of the palsy itself, but they prevent late complications — treat regardless of expected palsy recovery time.
Meningitis, radiculoneuropathy, or cranial neuropathy other than isolated facial palsy: start ceftriaxone IV once daily (cefotaxime IV or penicillin G IV are alternatives) once other causes of meningitis have been excluded, for a total of 14-21 days; once the patient is mildly ill or improving on initial IV therapy, switch to oral doxycycline to complete the course.
Lyme carditis
Outpatient — mildly ill, PR interval under 300 ms, hemodynamically stable: doxycycline, amoxicillin, or cefuroxime axetil PO for 14-21 days.
Admit to hospital for continuous cardiac monitoring — PR interval ≥300 ms or symptomatic carditis: start ceftriaxone or cefotaxime IV, then step down to oral doxycycline once clinically improving, for a total of 14-21 days.[3]
Lyme arthritis
Initial treatment: doxycycline, amoxicillin, or cefuroxime axetil PO for 28 days.
Mild residual joint swelling after the initial course: a second 28-day oral course is a reasonable option.
Arthritis that fails to resolve, or relapses, after oral therapy: treat with IV ceftriaxone (cefotaxime IV is an alternative) for 14-28 days; refer to rheumatology if synovitis persists 2 months or more after this course.
Non-Pharmacologic Treatment
Tick bite prevention
- Wear light-coloured, long-sleeved clothing in tick habitat to make ticks easier to spot.
- Shower or bathe within 2 hours of being outdoors, paying particular attention to the armpits, groin, back, and scalp — this helps dislodge unattached ticks before they bite.
- Do a full-body tick check daily on yourself and on children, especially the hairline, underarms, navel, and groin.
Tick removal technique — a real pharmacist counselling point
- Use clean, fine-tipped tweezers to grasp the tick by the head, as close to the skin surface as possible.
- Pull straight up, perpendicular to the skin, with steady, even pressure — do not twist or jerk, since this can cause the mouthparts to separate and remain embedded in the skin.
- Clean the bite site with soap and water or an alcohol-based antiseptic after removal.
- If mouthparts remain in the skin despite correct technique, leave them — they are usually expelled by the body without further intervention.
- Do not use folk remedies (petroleum jelly, a lit match, nail polish) to try to make the tick detach — these do not work reliably and may increase pathogen transmission by stressing the tick.
- Save the tick in a sealed container with the date, and consider submitting it to the local public health authority for identification — this supports surveillance, but tick testing is never used to make or exclude a diagnosis, since diagnosis is clinical.
Insect repellents
In the absence of a licensed human vaccine, avoiding tick bites is the mainstay of prevention. Health Canada's age-based recommendations for the 2 preferred repellent active ingredients:[5]
| Age group | DEET (diethyltoluamide) | Icaridin (picaridin) |
|---|---|---|
| Under 6 months | Not recommended | Not recommended |
| 6 months to 2 years | 10% concentration, applied once daily, for under 1 month | Preferred agent in this age group; up to 20% concentration |
| 2-12 years | 10% concentration, applied up to 3 times daily, for under 1 month | Preferred agent in this age group; up to 20% concentration |
| Over 12 years and adults | Up to 30% concentration (maximum 33%) | Up to 20% concentration |
Icaridin is odourless, does not feel sticky, and does not damage synthetic fabrics or plastics — a practical reason to recommend it over DEET for a child who will be wearing repellent repeatedly.
After a tick bite that does not meet postexposure prophylaxis criteria
- Counsel the patient to monitor the bite site and their overall health for up to 1 month for an expanding rash or flu-like symptoms, and to seek care promptly if either develops.
- Explain that prior infection does not provide protective immunity — reinfection with Lyme disease has been well documented, so the same prevention counselling applies regardless of past infection.
Special Populations
Breastfeeding: there is no evidence of transmission via breastfeeding. Follow the same drug preference as in pregnancy — amoxicillin or cefuroxime axetil for treatment, ceftriaxone for severe disease — and apply the same individualized discussion before using doxycycline for postexposure prophylaxis.
Pediatrics
Doxycycline is now first-line for children of any age provided the course is ≤21 days — current evidence does not support withholding it under age 8 for short courses, superseding older teaching.[7] Use weight-based dosing throughout (see Pharmacologic Treatment Options and Drug Tables). In children under 8 with a high-risk tick bite meeting all 3 postexposure prophylaxis criteria, the benefit of a single dose of doxycycline generally outweighs the risk. Amoxicillin has not been studied for single-dose prophylaxis and should not be used for that indication in any age group; azithromycin is reserved for the same narrow 2nd-line role as in adults.
Renal and hepatic impairment
Penicillin G and cefotaxime are renally cleared and require dose reduction in significant renal impairment — consult a renal dosing reference for the adjusted regimen. Ceftriaxone does not require dose adjustment for renal impairment alone given its predominant biliary excretion, but use caution with combined significant hepatic and renal impairment. Review doxycycline, amoxicillin, and cefuroxime axetil dosing in significant renal impairment; doxycycline itself does not require adjustment for renal impairment alone.
Monitoring & Follow-Up
Confirm clinical resolution rather than relying on repeat serology — antibodies persist for years after successful treatment and are not a test of cure. For erythema migrans, confirm the lesion resolves and watch for any new systemic or neurologic/cardiac symptoms during and after treatment, which would indicate dissemination rather than treatment failure. For facial nerve palsy, follow recovery clinically; antibiotics prevent late complications but do not accelerate the palsy's own resolution, and ophthalmology involvement may be needed for eye protection if closure is incomplete. For carditis, continue cardiac monitoring while hospitalized with PR prolongation — third-degree block typically resolves within 1 week of starting treatment, and lesser degrees of block within up to 6 weeks — then arrange outpatient ECG follow-up until resolution is confirmed.[3] For arthritis, some residual joint swelling can persist for weeks after an otherwise successful course; adjunctive NSAIDs may help symptoms while awaiting resolution. Watch for a Jarisch-Herxheimer-like reaction (fever, chills, rigors, sweating, myalgia, arthralgia) within 24 hours of starting treatment — this is a benign, self-limited reaction to spirochete lysis lasting under 48 hours, manageable with NSAIDs, and is not a sign of drug allergy or treatment failure.
Common Errors to Avoid
- Ordering serology for a typical erythema migrans lesion in a patient with plausible exposure — early Lyme disease is a clinical diagnosis, and serology is frequently falsely negative at this stage.
- Using a first-generation cephalosporin (e.g., cephalexin) for Lyme disease — it is not effective at any stage.
- Treating post-treatment Lyme disease syndrome, or a "chronic Lyme disease" diagnosis outside standard case definitions, with a prolonged or repeated antibiotic course — no proven benefit, and real risk of harm.[8]
- Missing PR-interval prolongation or another sign of AV block on ECG in a patient with Lyme disease and cardiac symptoms — this needs hospital admission and possible temporary pacing, not outpatient management.
- Using serologic titres to "prove" cure or to guide re-treatment decisions — antibodies persist for years regardless of treatment success.
- Twisting or jerking a tick during removal, or using a folk remedy (petroleum jelly, heat, nail polish) instead of steady traction with fine-tipped tweezers.
- Assuming a patient cannot have Lyme disease because they do not recall a tick bite — most patients do not recall the bite.
- Using amoxicillin as single-dose postexposure prophylaxis — its short half-life makes a single dose ineffective, and it has not been studied for this use.
- Delaying indicated treatment while waiting for serology results in a patient with a clinical presentation compatible with neurologic or cardiac Lyme disease — treat based on clinical suspicion in these presentations rather than waiting for confirmation.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are standard doses and require patient-specific confirmation, including renal/hepatic adjustment. Duration always depends on the specific clinical indication being treated — see Choose Initial Treatment for the stage-by-stage rule. Select any drug name to open its complete Pharmasist Drug Database page.
Tetracyclines
First-line agent for most indications; also the only agent used for single-dose postexposure prophylaxis.
| Drug | Dosage by indication | Adverse effects | Comments |
|---|---|---|---|
| Doxycycline | Erythema migrans — adults: 100 mg PO BID x 10 days Erythema migrans — children (any age): 4.4 mg/kg/day divided BID PO, max 100 mg/dose, x 10 days Facial nerve palsy alone — adults/children: 100 mg PO BID (weight-based in children) x 14-21 days Meningitis/other neurologic, oral step-down or once-daily alternative — adults: 100 mg PO BID to complete a total of 14-21 days, or 200 mg PO once daily as an alternative once-daily neuroborreliosis regimen Carditis, outpatient (mild) — adults/children: 100 mg PO BID (weight-based in children) x 14-21 days Carditis, oral step-down after IV (hospitalized) — adults/children: 100 mg PO BID (weight-based in children) to complete a total of 14-21 days Arthritis — adults/children: 100 mg PO BID (weight-based in children) x 28 days Postexposure prophylaxis — adults: 200 mg PO x 1 dose, within 72 hours of tick removal Postexposure prophylaxis — children: 4.4 mg/kg PO x 1 dose, max 200 mg; >45 kg: adult dose | GI upset, photosensitivity | Safe for short courses (≤21 days) at any pediatric age. Preferred for neurologic disease given CNS penetration. Not the preferred treatment agent in pregnancy/breastfeeding, but may be used for postexposure prophylaxis after an informed discussion. |
Penicillins
Equal-efficacy oral alternative (amoxicillin) or IV alternative (penicillin G) to doxycycline/ceftriaxone.
| Drug | Dosage by indication | Adverse effects | Comments |
|---|---|---|---|
| Amoxicillin | Erythema migrans — adults: 500 mg PO TID x 14 days Erythema migrans — children: 50 mg/kg/day divided TID PO, max 500 mg/dose, x 14 days Facial palsy / carditis, outpatient — adults: 500 mg PO TID x 14-21 days Facial palsy / carditis, outpatient — children: 50 mg/kg/day divided TID PO, max 500 mg/dose, x 14-21 days Arthritis — adults: 500 mg PO TID x 28 days Arthritis — children: 50 mg/kg/day divided TID PO, max 500 mg/dose, x 28 days | GI upset, rash, hypersensitivity | Preferred in pregnancy/breastfeeding for mild/localized disease, alongside cefuroxime axetil. |
| Penicillin G | Meningitis/other neurologic — adults: 18-24 million units/day IV divided Q4H x 14 days Meningitis/other neurologic — children: 200,000-400,000 units/kg/day IV divided Q4H, max 18-24 million units/day, x 14 days Arthritis, refractory (alternative) — adults: 18-24 million units/day IV divided Q4H x 14-28 days Arthritis, refractory (alternative) — children: 200,000-400,000 units/kg/day IV divided Q4H, max 18-24 million units/day, x 14-28 days | Rash, hypersensitivity, interstitial nephritis, seizures at high doses | Narrow spectrum; a reasonable IV alternative when ceftriaxone/cefotaxime are not appropriate. Requires renal dose adjustment. |
Cephalosporins, second-generation
Equal-efficacy oral alternative to doxycycline and amoxicillin.
| Drug | Dosage by indication | Adverse effects | Comments |
|---|---|---|---|
| Cefuroxime axetil | Erythema migrans — adults: 500 mg PO BID x 14 days Erythema migrans — children: 30 mg/kg/day divided BID PO, max 500 mg/dose, x 14 days Facial palsy / carditis, outpatient — adults: 500 mg PO BID x 14-21 days Facial palsy / carditis, outpatient — children: 30 mg/kg/day divided BID PO, max 500 mg/dose, x 14-21 days Arthritis — adults: 500 mg PO BID x 28 days Arthritis — children: 30 mg/kg/day divided BID PO, max 500 mg/dose, x 28 days | GI upset, rash, hypersensitivity | Drug of choice in pregnancy/breastfeeding alongside amoxicillin for mild/localized disease. |
Cephalosporins, third-generation
Parenteral therapy for meningitis/other neurologic disease, hospitalized carditis, and refractory arthritis; step down to oral doxycycline once clinically improving.
| Drug | Dosage by indication | Adverse effects | Comments |
|---|---|---|---|
| Ceftriaxone | Meningitis/other neurologic — adults: 2 g IV once daily x 14 days (range 10-21 days) Meningitis/other neurologic — children: 50-75 mg/kg IV once daily, max 2 g/dose, x 14 days (range 10-21 days) Carditis, hospitalized — adults/children: 2 g IV once daily (50-75 mg/kg in children, max 2 g/dose), stepped down to oral doxycycline once improving, total 14-21 days Arthritis, refractory/relapsed — adults/children: 2 g IV once daily (50-75 mg/kg in children, max 2 g/dose) x 14-28 days | GI upset, rash, hypersensitivity | Preferred parenteral agent given convenient once-daily dosing. |
| Cefotaxime | Meningitis/other neurologic — adults: 2 g IV Q8H x 14-21 days Meningitis/other neurologic — children: 150-200 mg/kg/day divided Q6-8H IV, max 6 g/day, x 14-21 days Carditis, hospitalized (alternative) — adults/children: 2 g IV Q8H (150-200 mg/kg/day divided Q6-8H in children, max 6 g/day), stepped down to oral doxycycline once improving Arthritis, refractory (alternative) — adults/children: 2 g IV Q8H (150-200 mg/kg/day divided Q6-8H in children, max 6 g/day) x 14-28 days | GI upset, rash, hypersensitivity, seizures at high doses | Reasonable substitute for ceftriaxone (e.g., biliary disease). |
Macrolides
2nd-line agent for early localized disease only — reduced efficacy compared with the tetracycline/penicillin/cephalosporin options above.
| Drug | Dosage by indication | Adverse effects | Comments |
|---|---|---|---|
| Azithromycin | Erythema migrans, 2nd line — adults: 500 mg PO once daily x 7 days (range 5-10 days) Erythema migrans, 2nd line — children: 10 mg/kg PO once daily, max 500 mg/dose, x 7 days (range 5-10 days) | GI upset, increased QTc interval | Use only when doxycycline, amoxicillin, and cefuroxime axetil are all contraindicated or not tolerated; arrange closer follow-up given lower efficacy. |
Not effective: first-generation cephalosporins (e.g., cephalexin) are not effective for Lyme disease at any stage.
Evidence note: Drug inventory, dosing, adverse effects, and comments reflect current IDSA/AAN/ACR guideline dosing, cross-checked against Public Health Agency of Canada guidance.[1][2]
References
- Clinical Practice Guidelines by the Infectious Diseases Society of America (IDSA), American Academy of Neurology (AAN), and American College of Rheumatology (ACR): 2020 Guidelines for the Prevention, Diagnosis and Treatment of Lyme Disease — Clinical Infectious Diseases (Lantos PM, Rumbaugh J, Bockenstedt LK, et al.) — reaffirmed by IDSA October 21, 2023. Clin Infect Dis 2021;72(1):e1-e48
- For health professionals: Lyme disease — Public Health Agency of Canada. Government of Canada, updated 2026
- Third-degree heart block associated with Lyme carditis: review of published cases — Clinical Infectious Diseases (Forrester JD, Mead P). Clin Infect Dis 2014;59(7):996-1000
- Prophylaxis with single-dose doxycycline for the prevention of Lyme disease after an Ixodes scapularis tick bite — New England Journal of Medicine (Nadelman RB, Nowakowski J, Fish D, et al.). N Engl J Med 2001;345(2):79-84
- Personal insect repellents — Health Canada, Pest Management Regulatory Agency. Government of Canada
- Committee Opinion No. 399: Management of Tick Bites and Lyme Disease During Pregnancy — Journal of Obstetrics and Gynaecology Canada (Smith GN, Moore KM, Hatchette TF, et al.; Society of Obstetricians and Gynaecologists of Canada). J Obstet Gynaecol Can 2020;42(5):644-653
- Management of Pediatric Lyme Disease: Updates From 2020 Lyme Guidelines — Pediatrics, American Academy of Pediatrics (Meissner HC, Steere AC). Pediatrics 2022;149(3):e2021054980
- Position statement on the diagnosis and treatment of people with persistent symptoms that have been attributed to Lyme disease — Journal of the Association of Medical Microbiology and Infectious Disease Canada, Association of Medical Microbiology and Infectious Disease Canada (AMMI Canada). J Assoc Med Microbiol Infect Dis Can 2019;4(2):43-46
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.