Microscopic Colitis
Clinical Snapshot
Microscopic colitis (MC) is a chronic inflammatory condition of the colon that produces chronic watery, non-bloody diarrhea in a patient whose colonoscopy looks essentially normal. That single fact is the highest-yield teaching point in this entire chapter: unlike ulcerative colitis or Crohn disease, microscopic colitis leaves no visible mucosal lesion for the endoscopist to target with a biopsy forceps — the diagnosis exists entirely at the microscopic level, in random biopsies taken from a grossly unremarkable-looking colon.[1][2] A pharmacist reading a colonoscopy report that says "normal colon, biopsies pending" should never assume this rules out a genuine, treatable inflammatory colonic disease — it may be exactly the picture MC produces.
Microscopic colitis comprises two principal histologic subtypes — collagenous colitis (CC), defined by an abnormally thickened subepithelial collagen band, and lymphocytic colitis (LC), defined by an increased density of intraepithelial lymphocytes — plus a third, increasingly recognized category, incomplete microscopic colitis (MCi), in which changes are present but fall short of the threshold for either full subtype.[1] All three share the same clinical presentation, the same normal-appearing colonoscopy, and, per current guidance, essentially the same first-line treatment — the distinction matters for pathology reporting and research, not for the pharmacist's practical treatment approach.[1]
MC is not rare. Pooled incidence across population-based studies is approximately 11.4 per 100,000 person-years, and pooled prevalence is approximately 119 per 100,000 persons — genuinely comparable in scale to Crohn disease in many Western populations.[1] It accounts for roughly 1 in 8 cases (12.8%) of otherwise unexplained chronic watery diarrhea worked up in referral settings, disproportionately affects women (pooled odds ratio 2.52 versus men), and is typically diagnosed after age 60 — though up to a quarter of cases are diagnosed before age 45, and pediatric cases are documented.[1] No Canadian Association of Gastroenterology practice guideline for microscopic colitis exists; this chapter is built primarily from the 2021 European Microscopic Colitis Group/United European Gastroenterology guideline and the American Gastroenterological Association's 2016 guideline, cross-checked against current primary literature throughout.[1][2]
Recognize the Condition
The presentation: chronic, watery, non-bloody diarrhea
The defining symptom of MC is chronic, watery, non-bloody diarrhea, reported by 84%-100% of patients across studies, with an average of 6-7 bowel movements per day at presentation.[1] Concomitant symptoms are common and clinically distinctive: fecal urgency (roughly 55%), nocturnal stools (roughly 35%), and fecal incontinence (roughly 26%) all occur meaningfully more often than in ordinary diarrhea-predominant irritable bowel syndrome, and their presence should raise, not lower, suspicion for MC.[1] Mild abdominal pain and bloating are common; modest weight loss can occur, but the visible blood, marked weight loss, and systemic illness that suggest classic inflammatory bowel disease are notably absent — their presence should prompt reconsidering the diagnosis rather than assuming a more severe presentation of MC (see Red Flags & Refer).
The classic patient
Think of an older woman — median age at diagnosis in the 60s, though MC can occur at any age — presenting with weeks to months of watery diarrhea that has often already been through one or more rounds of empiric management for presumed irritable bowel syndrome or infectious diarrhea before a colonoscopy is finally obtained.[1] This delay is common and avoidable: MC should be actively considered, not deferred to last, whenever an older patient presents with new persistent watery diarrhea, particularly if a new medication was started in the preceding months (see Risk Factors) or the patient carries a personal history of celiac disease or autoimmune thyroid disease.
Two things that make MC genuinely different from classic inflammatory bowel disease
Not visually, and not oncologically, like ulcerative colitis or Crohn disease
The mucosa looks normal
Endoscopic abnormalities are seen more often than once assumed — one pooled analysis found visible lesions (linear ulceration, mucosal edema or erythema, an altered vascular pattern, or pseudomembranes) in as many as 38.8% of cases — but these findings remain nonspecific, and a normal or near-normal appearance remains the dominant, expected picture.[1] Visible findings do not replace the need for biopsy, and a normal appearance does not exclude the diagnosis (see Assessment & Diagnosis).
No increased colorectal cancer risk
Unlike long-standing ulcerative colitis, MC does not increase the risk of colorectal cancer or adenoma — one pooled analysis found the odds ratio for adenoma was actually below 1 (0.49) in MC patients — and current guidance explicitly states that a special surveillance colonoscopy program is not recommended.[1] This is genuinely reassuring information worth actively giving a newly diagnosed patient, who may otherwise assume any "colitis" diagnosis carries the same cancer-surveillance burden as ulcerative colitis.
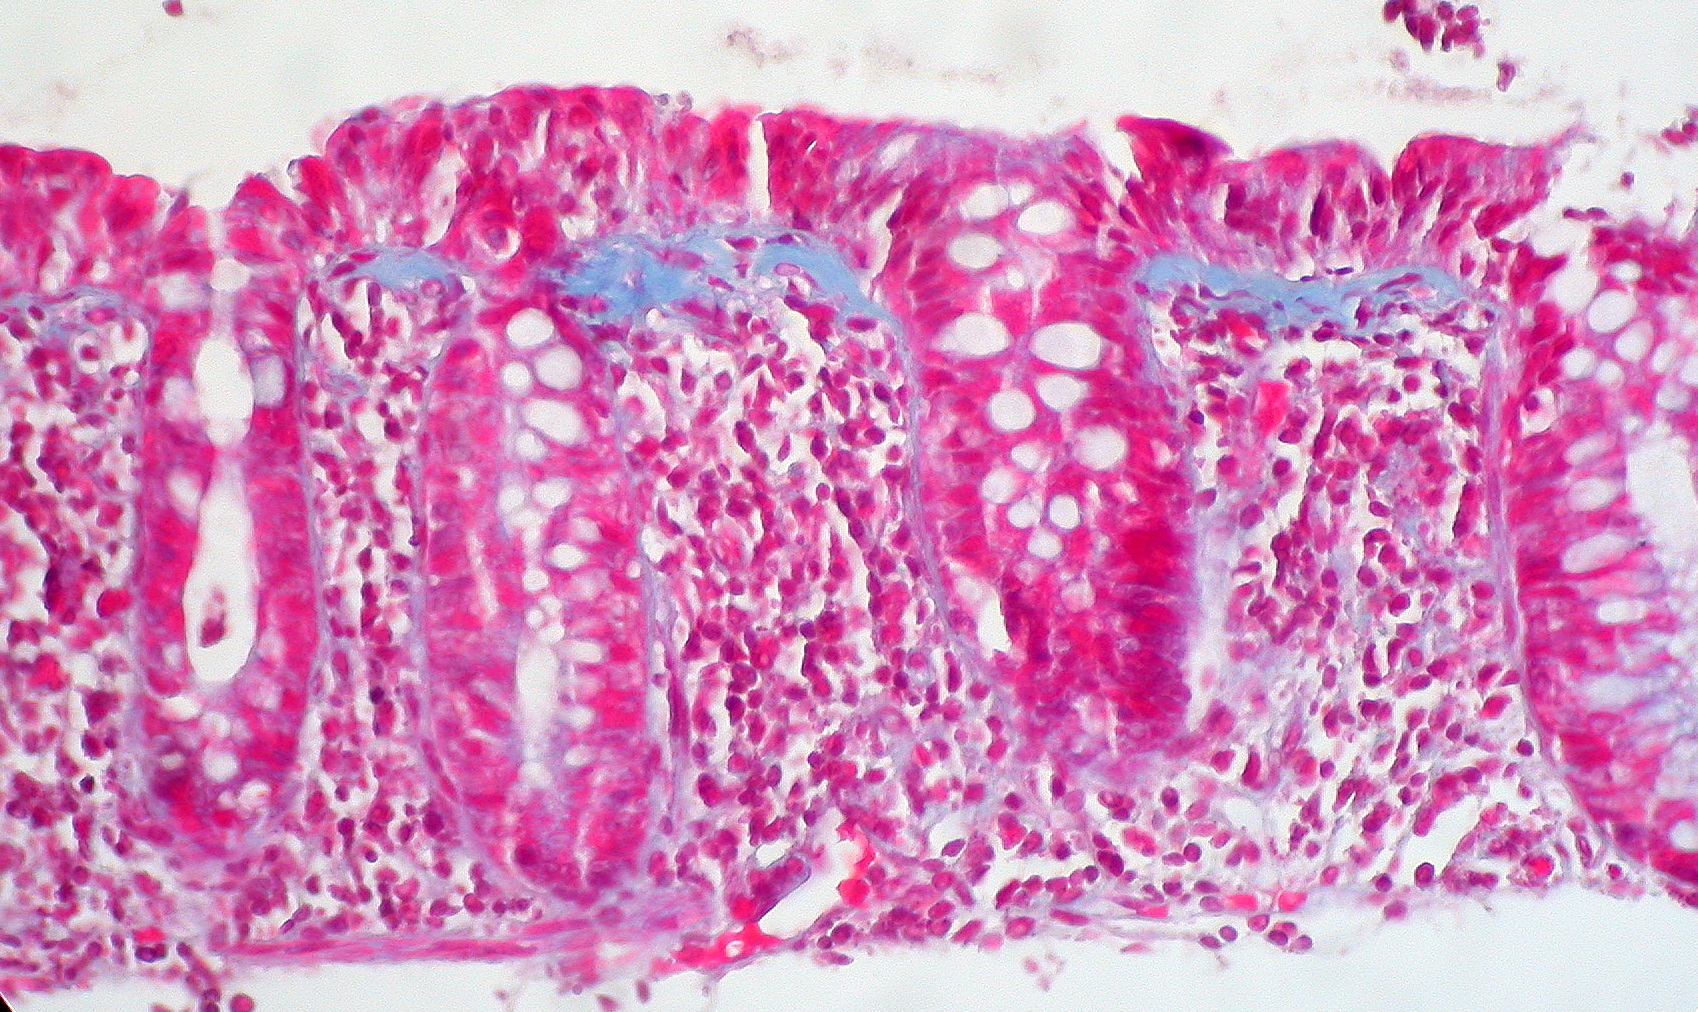
What untreated collagenous colitis looks like under the microscope
Risk Factors
- Age over 60 and female sex — pooled odds ratio 2.52 for women versus men across major studies; disease can occur at any age but is most often diagnosed after 60.[1]
- Current cigarette smoking — odds ratio 2.99 versus never-smokers, more strongly associated with collagenous colitis (OR 5.5) than lymphocytic colitis (OR 2.96); former smoking also carries some elevated risk (OR 1.6).[1]
- Drug exposure — the single most pharmacist-actionable risk factor in this chapter (see Choose Initial Treatment for the clinical response). A 2023 systematic review and meta-analysis found significant pooled associations for proton pump inhibitors (OR 2.34), SSRIs (OR 2.34), NSAIDs (OR 1.79), and aspirin (OR 2.84).[3] PPI risk is concentrated disproportionately in lansoprazole specifically, whose individual signal is markedly stronger than the PPI class average — reported as high as OR 9.57 in the same meta-analysis, and OR 4.69 for continuous 4-12 month use in the European guideline's own pooled estimate.[3][1] Statins, ACE inhibitors, benzodiazepines, beta-blockers, diuretics, and H2-receptor antagonists were not significantly associated in the same meta-analysis, which matters for not over-attributing every drug on a long medication list.[3]
- Celiac disease — genuinely bidirectional: roughly 3%-4% of MC patients (up to about 13% of collagenous colitis specifically, in some cohorts) also have celiac disease, several-fold higher than the general-population rate, and roughly 7% of celiac disease patients will themselves be diagnosed with MC at some point.[1]
- Autoimmune thyroid disease — a large 2025 Swedish nationwide case-control study found autoimmune thyroid disease in 12.0% of MC patients versus 7.8% of matched controls (adjusted OR 1.65), with a substantially stronger association (OR 2.41) in patients diagnosed with MC before age 50.[4]
- Other autoimmune disease — rheumatoid arthritis, type 1 diabetes, Sjögren disease, and psoriasis are all recognized associations; one case-control analysis found autoimmune conditions overall in 18.5% of MC patients versus 7.9% of controls.[4]
- Concurrent inflammatory bowel disease and bile acid malabsorption are also recognized, clinically relevant associations (see Assessment & Diagnosis and Treatment Failure/Next Step for the bile-acid-diarrhea link).
Red Flags & Refer
Any of the following should prompt reconsidering the diagnosis, escalating the workup, or referring rather than treating empirically as typical MC:
- Rectal bleeding, or visible blood in the stool — MC does not typically cause bleeding. Its presence should prompt re-evaluation for ulcerative colitis, Crohn disease, an infectious cause, or a colorectal neoplasm rather than being attributed to MC.[1]
- Significant unintentional weight loss, fever, or other systemic features — not typical of MC and warrant a broader workup rather than being assumed to represent unusually severe MC.
- Severe or high-volume diarrhea with dehydration or electrolyte derangement, particularly in an older or frail patient — needs prompt clinical assessment and, in more severe cases, hospital-level supportive care rather than purely outpatient medication adjustment.
- No meaningful response to an adequate trial of first-line budesonide (see Treatment Failure/Next Step) — reconsider the original diagnosis (was the biopsy protocol adequate? was a causative drug actually stopped?) rather than assuming simple treatment failure and escalating indefinitely.[1]
- New or changing symptoms in a patient with an already-established MC diagnosis — reassess for a second, coexisting diagnosis (celiac disease, inflammatory bowel disease, bile acid diarrhea, infection) rather than assuming a routine flare.
- Suspected acute kidney injury or significant dehydration from high-volume diarrhea in an older adult — this needs prompt medical assessment and, where indicated, intravenous fluids, not a purely outpatient problem.
Assessment & Diagnosis
Case definition
MC is diagnosed on the combination of chronic diarrhea lasting at least one month plus the histologic findings described below, in a colon that looks grossly normal or near-normal at colonoscopy.[1]
Colonoscopy and biopsy technique — the step most often done incompletely
Because the mucosa looks normal, biopsies must be taken irrespective of endoscopic appearance, not reserved for visibly abnormal areas.[1] Current guidance specifically recommends biopsies from at least the right and the left colon, submitted in separate, labelled containers so the pathologist knows which segment each sample came from. Concordance between right- and left-colon histology is high (95%-98%), but rectosigmoid-only biopsies are not an adequate substitute and risk a false-negative result, since disease can be patchy or, in a minority, most pronounced proximally.[1] An endoscopist who declines to biopsy a "normal-looking" colon in a patient with a genuinely compatible history of chronic watery diarrhea has not actually completed the diagnostic evaluation.
What the pathologist is looking for
| Subtype | Defining histologic finding |
|---|---|
| Collagenous colitis | Subepithelial collagen band ≥10 micrometres (measured in well-oriented sections cut perpendicular to the surface), plus an increased inflammatory infiltrate in the lamina propria |
| Lymphocytic colitis | ≥20 intraepithelial lymphocytes per 100 surface epithelial cells, plus an increased lamina propria infiltrate, with a collagen band that remains <10 micrometres |
| Incomplete microscopic colitis (MCi) | A mild lamina propria infiltrate plus either a collagen band of 5-10 micrometres (incomplete CC) or 10-20 intraepithelial lymphocytes per 100 epithelial cells (incomplete LC) — changes present but short of full-subtype criteria |
What NOT to order
Fecal calprotectin is not a useful screening or monitoring test for MC — levels overlap substantially between active disease, quiescent disease, and unaffected controls, unlike its genuinely useful role in classic inflammatory bowel disease.[1] Routine histological monitoring or repeat biopsy in a clinically improved patient is not recommended — histologic findings correlate only weakly with clinical activity, can persist in 45%-77% of patients even after clinical remission, and 6%-18% of patients show subtype conversion over time without this changing practical management.[1]
Screen for celiac disease
Because of the genuinely elevated bidirectional prevalence (see Risk Factors), current guidance specifically recommends screening every newly diagnosed MC patient for celiac disease (tTG-IgA plus a total IgA level) — a strong recommendation on high-quality evidence, not an optional add-on reserved for patients with additional celiac-suggestive features.[1]
Differential diagnosis
| Condition | Distinguishing feature(s) |
|---|---|
| Diarrhea-predominant irritable bowel syndrome | Genuinely overlaps symptomatically; nocturnal stools and fecal incontinence are more suggestive of MC and less typical of IBS-D |
| Bile acid diarrhea | Can coexist with MC or mimic it in isolation; consider testing or an empiric bile acid binder trial (see Choose Initial Treatment) |
| Celiac disease | Screen every MC patient given the genuine bidirectional association; can also coexist with MC rather than substitute for it |
| Ulcerative colitis / Crohn disease | Rectal bleeding, endoscopically visible ulceration/friability, and a genuinely elevated colorectal cancer risk with long-standing disease — none typical of MC |
| Clostridioides difficile and other infectious colitis | Stool studies; typically more acute onset than the chronic (≥1 month) course required for an MC diagnosis |
| Laxative misuse or other drug-induced diarrhea not meeting MC histologic criteria | Medication history; diarrhea resolves with discontinuation and biopsy does not meet MC criteria |
Treatment Targets
- Achieve clinical remission — defined and validated in trials by the Hjortswang criteria: a mean of fewer than 3 stools per day and a mean of fewer than 1 watery stool per day, averaged over a 1-week symptom diary.[1] Use this, or a simplified version of it, as an objective target rather than relying only on "the patient says they feel better."
- Actively identify and, wherever feasible, discontinue any temporally-associated causative drug before or alongside starting pharmacotherapy — a genuinely first-line, low-risk intervention this chapter treats as its own distinct step, not an afterthought (see Choose Initial Treatment).[1]
- Use budesonide, the only agent with consistent high-quality trial evidence, at the lowest effective dose for the shortest duration that maintains remission — most patients relapse quickly off treatment, so "shortest duration" does not mean stopping after a single course regardless of outcome (see Monitoring & Follow-Up).[1]
- Avoid unnecessary exposure to systemic corticosteroids (prednisone/prednisolone) given budesonide's comparable efficacy and substantially better systemic safety profile.[1]
- Screen for, and correct, celiac disease and other treatable comorbidities that can perpetuate diarrhea despite otherwise adequate MC-directed therapy.
- Recognize genuine treatment failure early, and distinguish it from an inadequate biopsy protocol, an unstopped causative drug, or a coexisting diagnosis, rather than escalating therapy against a possibly incorrect assumption.
Choose Initial Treatment
For every newly diagnosed MC patient, systematically review the medication list for a temporally plausible culprit. Highest-risk agents proton pump inhibitors (lansoprazole carries a disproportionately strong individual signal among PPIs[1][3]), SSRIs, NSAIDs, and regular aspirin use.[3] Current guidance gives a weak/conditional recommendation to consider withdrawal of any drug with a plausible chronological relationship to diarrhea onset — this is genuinely actionable, low-risk, and should happen in parallel with, not instead of, budesonide when disease is active enough to need pharmacotherapy; do not delay effective treatment purely to "see if stopping the drug alone works" in a symptomatic patient.[1] In practice this usually means working with the prescriber: substituting an H2-receptor antagonist or on-demand dosing for a chronic PPI continued without an ongoing indication, discussing an SSRI-class switch where psychiatrically feasible, or moving a patient off routine NSAID/aspirin use where the underlying indication allows.
Budesonide — preferred over every other agent, including prednisone
Oral budesonide is the only agent with consistent, high-quality randomized trial evidence in MC, and both the AGA and the 2021 European guideline recommend it first for induction in symptomatic patients of either major subtype.[2][1] Dose: 9 mg PO once daily for 6-8 weeks.[1] Budesonide undergoes roughly 90% first-pass hepatic and intestinal-mucosal metabolism, giving it a topically-acting, colon-targeted effect with substantially less systemic corticosteroid exposure than prednisone at an equivalent anti-inflammatory dose — which is exactly why current guidance specifically recommends against using prednisolone or any other systemic corticosteroid in place of budesonide[1], even though the AGA's earlier 2016 guideline still lists prednisone as a conditional, very-low-quality-evidence option specifically reserved for when budesonide is not feasible.[2] In trial data, budesonide achieved clinical remission in 81% of collagenous colitis patients (versus 26% on placebo) and 84% of lymphocytic colitis patients (versus 43% on placebo) after 6-8 weeks.[1] No routine taper is required at the end of a single 6-8 week induction course at this dose — adrenal insufficiency has not been reported with this specific regimen.[1]
When budesonide genuinely is not feasible
Cost, access, or intolerance can occasionally make budesonide impractical. Second-line, weaker evidence bismuth subsalicylate and mesalazine both have some historical trial support and remain listed as conditional options by the AGA[2], but the more recent 2021 European guideline is more skeptical: it explicitly recommends against mesalazine for induction (no meaningful benefit over placebo across the available trials) and judges the evidence for bismuth subsalicylate insufficient to recommend either way.[1] This is a genuine area of evolving evidence rather than a settled contradiction — the practical takeaway is that budesonide should be pursued as the true first choice whenever accessible, and mesalazine/bismuth subsalicylate should be understood as a fallback of meaningfully weaker evidence, not an equivalent alternative chosen simply on cost.
Bile acid diarrhea overlap
Bile acid malabsorption/diarrhea coexists often enough in MC that a trial of a bile acid binder (cholestyramine) is a reasonable option, particularly in a budesonide non-responder or when formal bile-acid testing is unavailable — current guidance gives this a weak recommendation in favour, reflecting genuine but limited-quality evidence.[1]
Symptomatic adjunct
Adjunct only loperamide has no dedicated randomized trial evidence in MC specifically, but given its well-established effect in chronic diarrhea generally, expert opinion favours its use for symptomatic relief in mild disease or as an adjunct alongside directed therapy — it does not treat the underlying inflammation and should not substitute for budesonide in a patient with at least moderate active disease.[1]
Not recommended
Avoid antibiotics, probiotics, and Boswellia serrata all lack adequate supporting evidence and are specifically recommended against for MC treatment.[1]
Non-Pharmacologic Treatment
- Systematically review and, in partnership with the prescriber, stop or substitute any temporally plausible causative drug (see Choose Initial Treatment) — genuinely the single most pharmacist-actionable non-drug-therapy intervention in this chapter.[1][3]
- Smoking cessation is reasonable general advice given the genuine association between current smoking and MC risk, though current evidence is insufficient to confirm that quitting after diagnosis changes the disease course — counsel for its many other health benefits rather than promising it will resolve the diarrhea.[1]
- Adequate oral hydration and electrolyte attention, particularly in an older patient with high-volume diarrhea, urgency, or nocturnal stools — dehydration risk in this population is genuinely under-recognized relative to more visibly "dramatic" inflammatory bowel disease presentations.
- A trial dietary review for caffeine, dairy (if lactose intolerance is plausible), and other individually reported triggers is reasonable supportive advice, though no specific diet has been shown to alter the underlying disease course the way it does in, for example, celiac disease.
- Reassure the patient early that microscopic colitis does not increase colorectal cancer risk and does not require a special surveillance colonoscopy program — this is a genuinely common and unnecessary source of patient anxiety once any "colitis" diagnosis is mentioned.[1]
Special Populations
Older adults
This is genuinely the population MC most often affects — most patients are diagnosed after age 60.[1] High-volume watery diarrhea, urgency, and nocturnal stools carry real fall, dehydration, and functional-decline risk in frail older patients; treat these symptoms with real urgency rather than as a minor nuisance complaint. Review the full medication list with particular attention to PPIs continued without an ongoing indication (a well-recognized, broadly under-deprescribed pattern in this age group generally) and to NSAIDs used for chronic musculoskeletal pain. Watch for cumulative corticosteroid exposure — bone mineral density can decline with prolonged budesonide use even though it is substantially safer than prednisone (see Monitoring & Follow-Up).[1]
Women
The roughly 2.5-fold female predominance holds across both major subtypes and across the age spectrum.[1] No MC-specific reason exists to alter counseling by sex beyond the higher baseline pretest probability when a woman presents with compatible symptoms.
Patients who cannot simply stop the causative drug
Not every implicated drug can be discontinued — an SSRI may be essential for the patient's mental health, an NSAID may be the only effective option for another chronic condition, or a PPI may have a genuine, ongoing indication (confirmed erosive esophagitis, a bleeding-risk indication). In these situations, do not withhold budesonide while waiting for a deprescribing conversation to resolve — treat the MC directly, and pursue medication review as a parallel, collaborative discussion with the prescriber rather than a precondition for treatment.
Patients with celiac disease or autoimmune thyroid disease
Given the genuinely elevated bidirectional prevalence, persistent GI symptoms in a patient with known celiac disease or autoimmune thyroid disease — even one who is otherwise well-controlled — deserve real consideration of a second, coexisting MC diagnosis rather than being attributed automatically to the known condition.[1][4] Correcting one diagnosis does not rule out the other.
Pregnancy and lactation
MC is uncommon in patients of reproductive age given its typical age of onset, but it does occur. Safety data specific to budesonide use for MC in pregnancy are limited; individualize therapy with obstetric input, favouring the lowest effective dose and involving the patient's obstetric care team in any treatment decision.
Steroid-dependent or biologic-refractory patients
A small but genuine and growing body of evidence, including a 2022 Canadian multicentre case series (7 patients across 3 Winnipeg-area centres, most either oral-steroid-dependent or with prior biologic failure/intolerance), supports vedolizumab as an option once budesonide, immunomodulators, and/or anti-TNF therapy have failed — in that Canadian series, stool frequency fell from 7 or more daily to 1-3 daily in the majority of patients by more than 6 months post-induction, with clear improvement in urgency, incontinence, and nocturnal symptoms.[5] This remains specialist-directed, refractory-disease-only therapy (see Treatment Failure/Next Step).
Monitoring & Follow-Up
- Reassess symptoms against the Hjortswang remission criteria (mean <3 stools/day and <1 watery stool/day over a week) at follow-up, not simply a "better/worse" impression.[1]
- Do not order routine repeat colonoscopy, biopsy, or fecal calprotectin to monitor a clinically improving patient — none of these change management, and histologic findings correlate only weakly with symptoms.[1]
- For a patient continuing budesonide beyond a single induction course: reassess at regular intervals whether maintenance therapy is genuinely still needed, aim for the lowest effective dose (6 mg daily, or an alternate-day 3 mg/6 mg regimen once stable), and periodically attempt a taper, given that roughly 20% of patients need 6 mg/day or more long-term while many others can step down successfully.[1]
- Watch for bone-health implications with prolonged budesonide use — while its systemic corticosteroid burden is substantially lower than prednisone's, prolonged high-dose use has still been associated with measurable bone mineral density change in other budesonide-treated GI populations; apply the same general bone-health vigilance used for any patient on long-term corticosteroid-class therapy.[1]
- Reconfirm at every visit that any causative drug identified at diagnosis was actually stopped, not merely "discussed" — this is a common, quietly incomplete step.
- Revisit the celiac disease screen if it was not completed at diagnosis, and reassess for it if new or unexplained symptoms emerge later.[1]
Common Errors to Avoid
- Ruling out an inflammatory colonic disease, and therefore MC specifically, because "the colonoscopy was normal" — a normal-appearing colon is the expected finding in MC, not a reason to skip biopsy.[1]
- Accepting rectosigmoid-only biopsies as an adequate substitute for biopsies from both the right and left colon.[1]
- Starting prednisone or another systemic corticosteroid before budesonide, rather than reserving systemic steroids for the rare situation where budesonide is genuinely unusable.[1]
- Not reviewing the medication list for a PPI (especially lansoprazole), SSRI, NSAID, or aspirin with a plausible temporal relationship to diarrhea onset before or alongside starting pharmacotherapy.[1][3]
- Continuing a chronic PPI indefinitely in an MC patient without ever reassessing whether the original indication still applies — a broadly under-deprescribed pattern that is specifically relevant here.
- Ordering fecal calprotectin or scheduling routine repeat colonoscopy/biopsy to monitor a clinically stable or improving patient.[1]
- Treating budesonide as a fixed, one-time course regardless of outcome — a genuine majority of patients relapse after stopping induction therapy, and maintenance dosing is a real, guideline-supported option, not "long-term steroid dependence" to be avoided reflexively.[1]
- Skipping celiac disease screening at diagnosis.[1]
- Telling a patient that microscopic colitis raises their colorectal cancer risk or that they need extra surveillance colonoscopies — current evidence shows no increased risk, and no special surveillance program is recommended.[1]
- Attributing new or changing GI symptoms in a patient with known celiac disease or autoimmune thyroid disease automatically to that known condition, without considering a second, coexisting MC diagnosis.[4]
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
First-Line — Budesonide (Oral)
The only agent with consistent, high-quality trial evidence in MC. Preferred over prednisone and every other systemic corticosteroid given its high first-pass metabolism and substantially lower systemic exposure.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Budesonide (oral) | Induction: 9 mg PO once daily for 6-8 weeks Maintenance: 6 mg PO once daily, tapering toward the lowest effective dose (e.g., 3 mg alternate-day) once stable | Headache, nausea; low systemic corticosteroid burden, though prolonged high-dose use can still affect bone density | Strong CYP3A4 inhibitors (azole antifungals, some protease inhibitors, grapefruit) increase systemic exposure | No taper needed after a single 6-8 week induction course at 9 mg/day — adrenal insufficiency has not been reported with this regimen.[1] |
Second-Line — When Budesonide Is Genuinely Not Feasible
Both carry meaningfully weaker current evidence than budesonide. The 2021 European guideline now recommends against mesalazine for induction and judges bismuth subsalicylate evidence insufficient either way, in contrast to the AGA's older conditional recommendations for both.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Mesalazine | Adults: 3 g/day in divided doses | GI upset; generally well tolerated | Reduced absorption with concurrent antacids | 3 g/day in divided doses was the dose studied in collagenous colitis trials; use only as a true budesonide-inaccessible fallback.[2][1] |
| Bismuth subsalicylate | Adults: 8 chewable 262 mg tablets/day (3-2-3 split) for 8 weeks | Dark stools/tongue; salicylate toxicity risk with prolonged high-dose use, particularly with concurrent NSAID/aspirin use | Additive salicylate exposure with aspirin or other salicylates; may reduce absorption of tetracyclines | Eight 262 mg chewable tablets/day (3 morning, 2 midday, 3 evening) for 8 weeks was the dose in the original open-label trial.[2] |
Bile Acid Binder — Overlap or Adjunct Trial
Reasonable in a patient with a bile-acid-diarrhea-compatible pattern, or as a trial in a budesonide non-responder. Weak recommendation reflecting genuine but limited-quality evidence.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Cholestyramine resin | Adults: 4 g PO once to three times daily with meals, titrated to response | Bloating, constipation, fat-soluble vitamin malabsorption with prolonged use | Reduces absorption of many co-administered drugs (levothyroxine, warfarin, digoxin, fat-soluble vitamins) — separate dosing by several hours | Counsel on strict separation from other oral medications given its broad drug-binding potential.[1] |
Symptomatic Adjunct
Does not treat the underlying colonic inflammation and should not substitute for budesonide in at least moderate active disease.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Loperamide | Adults: 2 mg PO after each loose stool, or scheduled dosing per product monograph, to a standard maximum daily dose | Constipation, abdominal cramping | Avoid with other agents causing significant constipation or ileus risk | No dedicated MC trial evidence; expert opinion favours use for symptomatic relief in mild disease or as an adjunct.[1] |
Avoid as First-Line, or Not Recommended
Prednisone carries meaningfully more systemic exposure than budesonide for equivalent efficacy. Methotrexate is specifically recommended against for MC at any point in the treatment pathway.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Prednisone | Adults: Per specialist-directed protocol if used | Hyperglycemia, weight gain/cushingoid features, bone loss, mood changes, increased infection risk | Numerous CYP3A4-mediated interactions; additive hyperglycemia with other diabetogenic drugs | Reserve for the rare situation where budesonide is genuinely unusable; specialist-directed only.[1][2] |
| Methotrexate | Not recommended: Not indicated for microscopic colitis | Hepatotoxicity, myelosuppression, teratogenicity, stomatitis | Additive hepatotoxicity with other hepatotoxic drugs; NSAIDs can reduce methotrexate clearance | Specifically recommended against for MC — do not substitute for a thiopurine or biologic in refractory disease.[1] |
Refractory Disease — Specialist-Directed Immunomodulators and Biologics
Reserved for confirmed budesonide-refractory, intolerant, or steroid-dependent disease after diagnosis reconfirmation and medication review (see Treatment Failure/Next Step). All are off-label for MC.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Azathioprine | Adults: Specialist-directed, weight-based protocol | Myelosuppression, hepatotoxicity, GI intolerance, rare pancreatitis | Allopurinol and febuxostat markedly increase active thiopurine metabolite levels | Steroid-sparing option for a more prolonged specialist-directed course.[1] |
| Infliximab | Adults: Specialist-directed protocol | Infusion reaction, infection risk, rare hepatotoxicity | Avoid live vaccines during therapy; additive infection risk with other immunosuppressants | Specialist GI-initiated only, typically extrapolated from inflammatory bowel disease dosing.[1] |
| Adalimumab | Adults: Specialist-directed protocol | Injection-site reaction, infection risk | Avoid live vaccines during therapy; additive infection risk with other immunosuppressants | Specialist GI-initiated only, typically extrapolated from inflammatory bowel disease dosing.[1] |
| Vedolizumab | Adults: Specialist-directed protocol | Infusion reaction; gut-selective mechanism gives a favourable systemic safety profile relative to anti-TNF therapy | Fewer systemic drug interactions than anti-TNF agents given its gut-selective mechanism | Real, growing evidence in exactly this refractory population, including a 2022 Canadian multicentre case series of steroid-dependent/biologic-refractory patients.[5] |
Medications Associated With Microscopic Colitis — Review for Discontinuation or Substitution
None of these are contraindicated outright, but each is worth a specific second look at diagnosis — see Choose Initial Treatment. Pooled odds ratios from a 2023 systematic review and meta-analysis, unless otherwise noted.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Lansoprazole | Review: Confirm an ongoing indication exists; consider substitution or discontinuation | As per product monograph; the association with MC is the reason for review here, not a direct adverse effect of ordinary use | Standard PPI interaction profile (reduced absorption of drugs requiring gastric acidity) | Carries a disproportionately strong individual signal among PPIs (OR up to 9.57 in one meta-analysis); review ongoing indication before continuing.[3][1] |
| Omeprazole | Review: Confirm an ongoing indication exists; consider substitution or discontinuation | As per product monograph | Standard PPI interaction profile | PPI class pooled OR 2.34 for MC; review ongoing indication before continuing.[3] |
| Ibuprofen | Review: Consider a non-NSAID alternative or the lowest effective dose/duration | Standard NSAID gastrointestinal, renal, and cardiovascular risks | Standard NSAID interaction profile | NSAID class pooled OR 1.79 for MC.[3] |
| Naproxen | Review: Consider a non-NSAID alternative or the lowest effective dose/duration | Standard NSAID gastrointestinal, renal, and cardiovascular risks | Standard NSAID interaction profile | Same NSAID-class MC association as ibuprofen.[3] |
| Acetylsalicylic acid (aspirin) | Review: Confirm an ongoing indication exists; do not stop without discussing cardiovascular risk with the prescriber | GI upset, bleeding risk | Additive bleeding risk with anticoagulants or other antiplatelets | Pooled OR 2.84 for MC — among the strongest individual associations identified; confirm an ongoing cardiovascular indication before continuing routine use.[3] |
| Sertraline | Review: Coordinate any dose change or substitution with the prescribing clinician | As per product monograph; the association with MC is the reason for review here, not a direct adverse effect of ordinary use | Standard SSRI interaction profile | SSRI class pooled OR 2.34 for MC; do not stop unilaterally given psychiatric relapse risk — coordinate any change with the prescriber.[3] |
References
- European guidelines on microscopic colitis: United European Gastroenterology and European Microscopic Colitis Group statements and recommendations — United European Gastroenterology Journal (Miehlke S, Guagnozzi D, Zabana Y, Tontini GE, Kanstrup Fiehn AM, Wildt S, Bohr J, Bonderup O, Bouma G, D'Amato M, Heiberg Engel PJ, Fernandez-Banares F, Macaigne G, Hjortswang H, Hultgren-Hornquist E, Koulaouzidis A, Kupcinskas J, Landolfi S, et al.). United European Gastroenterol J 2021;9(1):13-37
- American Gastroenterological Association Institute Guideline on the Medical Management of Microscopic Colitis — Gastroenterology, American Gastroenterological Association (Nguyen GC, Smalley WE, Vege SS, Carrasco-Labra A). Gastroenterology 2016;150(1):242-246
- Drug Exposure and Risk of Microscopic Colitis: A Systematic Review and Meta-Analysis — Digestive Diseases (Zhang S-W, Xu R, Chen D). Dig Dis 2023;41(2):217-226
- Autoimmune Thyroid Diseases and Microscopic Colitis: A Nationwide Matched Case-Control Study in Sweden — Journal of Clinical Endocrinology & Metabolism (Bergman D, Kang X, Sun J, Ebrahimi F, Ludvigsson JF). J Clin Endocrinol Metab 2025;110(11):e3730-e3737
- A165 Vedolizumab is an option to treat microscopic colitis in patients dependent on oral steroids or have failed a biologic: a multicentre Canadian case series — Journal of the Canadian Association of Gastroenterology (Kulyk A, Muthiah K). J Can Assoc Gastroenterol 2022;5(Suppl 1):43-44
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.