Infectious Mononucleosis
Clinical Snapshot
Infectious mononucleosis is an acute viral syndrome classically presenting as the triad of fever, pharyngitis, and lymphadenopathy, most often caused by primary infection with Epstein-Barr virus (EBV), a ubiquitous herpesvirus that eventually infects roughly 90% of adults worldwide.[1] Approximately 10% of clinically indistinguishable mono-like illness is instead caused by primary cytomegalovirus (CMV) infection, which characteristically produces a heterophile-negative presentation — a genuinely important distinction covered fully in Assessment & Diagnosis, since it changes both test interpretation and, in a pregnant patient, the clinical stakes.[2] EBV mononucleosis peaks in adolescents and young adults 15-24 years of age, spread through close contact with infected saliva (sharing drinks or utensils, kissing — hence "the kissing disease"), with a long incubation period of roughly 4-7 weeks during which the patient is already contagious.[2][1]
This chapter is built around four teaching points that matter disproportionately to pharmacist practice. First, physical examination for splenomegaly is genuinely unreliable (sensitivity 20-70%), so a normal-feeling abdomen does not lift activity restrictions.[2] Second, the heterophile antibody (monospot) test has a real, clinically important false-negative rate in the first week of illness — a negative test early on does not exclude the diagnosis.[2] Third, and most specific to pharmacy counseling: giving amoxicillin or ampicillin to a patient with unrecognized mono produces a diffuse, itchy, non-allergic drug-virus rash — not a true IgE-mediated penicillin allergy — and this single mislabeling event is a common, avoidable source of a lifelong (and false) "penicillin allergy" on a patient's chart.[3][4] Fourth, splenic rupture, though rare, is the complication that drives this chapter's central safety counseling: a mandatory multi-week restriction from contact sports, heavy lifting, and vigorous exertion. Treatment for essentially every patient is supportive; corticosteroids and antivirals add no benefit in uncomplicated disease and are reserved for a short, specific list of severe complications.[5][6][7]
Recognize the Condition
Classic presentation
The classic triad — fever, pharyngitis, and lymphadenopathy — is neither universal nor, individually, especially reliable for diagnosis; common associated symptoms include malaise, anorexia, fatigue (often the most prominent and longest-lasting complaint), headache, and upper respiratory symptoms (rhinorrhea, nasal congestion), with abdominal pain occurring in a meaningful minority.[2] A systematic review and meta-analysis of diagnostic accuracy found that the single sign most predictive of infectious mononucleosis is posterior cervical lymphadenopathy — more useful than fever, pharyngitis, or fatigue alone, none of which reliably distinguishes mono from other causes of pharyngitis on their own.[2] Axillary or inguinal lymphadenopathy, while less sensitive, is comparably specific and — when present alongside posterior cervical nodes — is a genuinely useful pattern for distinguishing mono from other causes of infectious pharyngitis, most of which do not produce this distribution.[2]
| Finding | What it tells you |
|---|---|
| Posterior cervical lymphadenopathy | The single most useful positive finding for mono on exam; still absent in roughly a third of cases, so its absence does not exclude the diagnosis.[2] |
| Tonsillar exudate | Present in about half of cases; nonspecific — also common in streptococcal and other viral pharyngitis, so exudate alone cannot distinguish mono from strep throat.[2] |
| Palatal petechiae | Less common than tonsillar exudate but more specific for mono when present; can also occur in streptococcal pharyngitis.[2] |
| Splenomegaly | Nearly universal pathologically, but physical examination for it is genuinely unreliable — reported sensitivity 20-70% and specificity 69-100% across studies. A normal-feeling spleen on exam does not rule out clinically significant splenomegaly and must never be used to justify lifting activity restrictions early.[2] |
| Rash (without antibiotic exposure) | Uncommon at baseline — well under 5% of patients develop a maculopapular, urticarial, or petechial rash from the illness itself. A rash appearing after amoxicillin or ampicillin exposure is a very different, far more common phenomenon — see the central teaching point below and in Choose Initial Treatment.[2] |

Pathophysiology in brief
EBV first replicates in the oropharyngeal epithelium and infects B lymphocytes via the CD21 receptor. The clinical illness is driven less by the virus itself than by the massive, often striking CD8+ T-cell response mounted against infected B cells — this expanded, activated T-cell population is what produces the atypical lymphocytes (reactive "Downey cells") seen on peripheral blood smear and used diagnostically (see Assessment & Diagnosis).[1] The incubation period is roughly 32-49 days, and viral shedding in the oropharynx (and, less relevantly for pharmacy counseling, genital secretions) continues for a prolonged period, which is why lifelong intermittent asymptomatic shedding after recovery is the norm rather than the exception — patients do not need isolation once acutely ill, since most transmission occurs from asymptomatic shedders in the general population.[1][2]
Age-related presentation differences
Children younger than 5 years often present less classically — fever, pharyngitis, and lymphadenopathy remain common, but this age group is more likely than adolescents and adults to show a rash, palpable splenomegaly, and prominent upper respiratory symptoms, and upper airway obstruction from tonsillar/adenoidal hypertrophy is specifically more common in young children (see Red Flags & Refer and Special Populations).[2]
Longer-term associations worth knowing
Beyond the acute illness, EBV has been causally linked to two premalignant lymphoproliferative conditions and 9 types of cancer, including Hodgkin lymphoma, non-Hodgkin lymphoma, and nasopharyngeal carcinoma, and prior EBV infection has been associated with an increased risk of several autoimmune diseases — most strikingly, a large prospective case-control study of U.S. military personnel found a roughly 32-fold increased risk of multiple sclerosis following EBV infection.[2] These associations do not change acute management but are useful context when patients or families ask "is this actually serious."
Risk Factors
- Age 15-24 years — the peak incidence age band in higher-income countries (roughly 6-8 cases per 1,000 person-years).[2]
- Communal living environments with close, sustained personal contact — dormitories, military barracks, and similar settings carry a substantially higher incidence (roughly 11-48 cases per 1,000 person-years).[2]
- EBV-seronegative status — roughly one-third of adolescents/young adults and a small minority of older adults remain seronegative and therefore susceptible; most people acquire subclinical EBV infection earlier in childhood and never develop recognized mono.[2]
- Close salivary contact — kissing, and sharing drinks, food, or utensils with an infected (often asymptomatically shedding) person.[2][1]
- Immunocompromised state (HIV, post-transplant immunosuppression, primary immunodeficiency) — not a risk factor for acquiring EBV itself, but a major risk factor for severe, atypical, or malignant EBV-driven disease (see Special Populations).[2]
Red Flags & Refer
Uncomplicated mono is managed supportively, but a specific, short list of complications changes the plan to urgent evaluation:
- Impending upper airway obstruction — stridor, severe dysphagia, drooling/inability to handle secretions, muffled ("hot potato") voice, or respiratory distress from massive tonsillar/adenoidal swelling. This is more common in young children given their relatively smaller airway, but occurs at any age and is one of only 3 situations in this chapter where corticosteroids are genuinely indicated (see Choose Initial Treatment).[2][7]
- Acute or worsening abdominal pain, especially left upper quadrant pain, left shoulder pain (Kehr sign), or hemodynamic instability — evaluate emergently for splenic rupture. Splenic injury is rare (0.1-0.2% of mono cases) but carries up to 9% mortality when it occurs and is nontraumatic (spontaneous) in 80-86% of cases; contrast-enhanced CT is the preferred imaging modality.[2]
- Signs of severe autoimmune hemolytic anemia — new pallor, jaundice, dark urine, or marked fatigue out of proportion to the rest of the illness.[7]
- Signs of severe thrombocytopenia — petechiae, easy bruising, mucosal bleeding, or frank hemorrhage.[7]
- Neurologic signs (severe headache, altered mental status, neck stiffness, focal deficit) — evaluate for meningoencephalitis.[2]
- Chest pain, palpitations, or new arrhythmia — evaluate for myocarditis or a cardiac conduction abnormality.[2]
- Persistent high fever with worsening cytopenias, hepatosplenomegaly, and markedly elevated ferritin — consider hemophagocytic lymphohistiocytosis (HLH), a rare but life-threatening complication.[2]
- Jaundice or marked right upper quadrant pain — evaluate for severe hepatitis (a recognized, though uncommon, cause of hospitalization).[2]
- Any suspected mono-like illness in an immunocompromised or transplant patient — refer promptly; the differential and stakes are meaningfully different (see Special Populations).
Reassuring context: hospitalization for infectious mononucleosis overall occurs in well under 1% of cases — the great majority of patients are managed entirely supportively as outpatients.[2]
Assessment & Diagnosis
Initial testing
Cost-effective, efficient initial testing for suspected acute mono is a complete blood count with differential plus a rapid heterophile antibody (monospot) test.[2] On the CBC, look for absolute or relative lymphocytosis with atypical lymphocytes; the classic Hoagland criteria (greater than 50% lymphocytes and greater than 10% atypical lymphocytes, in the presence of fever, pharyngitis, and adenopathy, with confirmatory serology) are specific but not sensitive — a patient can genuinely have mono without meeting them, particularly early in the illness.[2] As a rough guide to how strongly an atypical lymphocyte count points toward mono: over 10% is modestly suggestive, over 20% more so, and over 40% is a strong, highly specific signal.[2]
The heterophile antibody (monospot) test — know its real limitations
The rapid heterophile antibody latex agglutination test is inexpensive and fast, with a reported sensitivity of roughly 87% and specificity of roughly 91% in a systematic review — figures from controlled study conditions that likely overstate real-world office performance.[2][8] Critically, it carries genuine, clinically important limitations:
- False-negative results in up to 25% of adults during the first week of symptoms — the antibody response has simply not yet developed. A single negative monospot early in a convincing clinical picture does not exclude mono; repeat testing in a week, or move directly to EBV-specific serology, rather than dismissing the diagnosis.[2][8]
- High false-negative rates in children younger than 5 years, who mount a weaker heterophile antibody response overall — a negative monospot is considerably less reassuring in this age group.[2][8]
- Positive results can persist for up to a year after the initial infection, so a positive monospot in a patient with a different, unrelated current illness does not necessarily explain the current presentation.[2]
- False positives can occur with autoimmune disease, viral hepatitis, and HIV infection — and classically with toxoplasmosis, which is why a compatible exposure history (undercooked meat, cat litter box exposure) with a positive heterophile test should prompt confirmatory toxoplasma IgM serology rather than accepting the mono diagnosis at face value.[2]
When heterophile testing is negative but suspicion remains high
EBV-specific serology (viral capsid antigen [VCA] IgM and IgG, EBV nuclear antigen [EBNA] IgG) is more sensitive and specific than heterophile testing but costs more and takes longer to result. VCA IgM appears early and remains detectable for roughly 4-6 weeks; VCA IgG appears around 2 weeks after infection and persists for life; EBNA IgG typically does not become detectable until 6-8 weeks after infection. VCA IgM without EBNA antibody indicates primary (acute) infection; VCA IgG with EBNA antibody indicates past infection. This distinction matters most when diagnostic certainty genuinely changes management — competitive athletes (where the diagnosis drives weeks of activity restriction) and pregnant patients (where distinguishing primary EBV from primary CMV mononucleosis has real clinical stakes — see Special Populations) are the two groups where EBV-specific serology is specifically worth pursuing rather than relying on a heterophile test alone.[2]
When heterophile testing is negative and EBV serology does not confirm the diagnosis, consider CMV IgM serology: primary CMV mononucleosis is clinically almost indistinguishable from EBV mono but is heterophile-negative by definition, and positive CMV IgM is the most practical way to confirm it.[2] Modestly elevated hepatic transaminases are common in mono (reported in a majority of outpatient cases and even more consistently in hospitalized patients) and, while nonspecific, raise clinical suspicion for mono in a heterophile-negative patient with a compatible picture.[2]
Differential diagnosis
| Diagnosis | Key distinguishing features |
|---|---|
| Primary CMV mononucleosis | Clinically nearly indistinguishable from EBV mono; heterophile-negative by definition; confirm with CMV IgM. Accounts for roughly 1 in 10 mono-like presentations.[2] |
| Acute HIV infection | Mucocutaneous lesions, rash, weight loss, diarrhea, nausea/vomiting — a broader systemic picture than typical mono; consider in any patient with a relevant exposure history.[2] |
| Streptococcal pharyngitis | Throat pain typically without hepatomegaly or splenomegaly; fatigue is far less prominent than in mono. Can genuinely coexist with mono, which is why routine strep testing "if indicated" — not reflexive empiric antibiotics — is the right approach (see Choose Initial Treatment).[2] |
| Toxoplasmosis | Recent history of eating undercooked meat or cleaning a cat's litter box; can cause a false-positive heterophile result, so confirm with toxoplasma IgM serology rather than the monospot alone.[2] |
| Other viral pharyngitis | Throat pain without the fuller mono picture; fever, adenopathy, and tonsillar exudate are all individually less likely than in mono.[2] |
Imaging
Routine imaging has no role in diagnosing uncomplicated mono. Ultrasonography can reliably characterize splenic size, but because splenic enlargement is nearly universal in mono, it does not meaningfully change management or reliably predict rupture risk — the American Medical Society for Sports Medicine's Choosing Wisely recommendation is specifically to avoid ordering abdominal ultrasonography routinely in athletes with infectious mononucleosis, since it does not expedite a safe return to play.[2] Reserve imaging — contrast-enhanced CT is preferred — for a patient with acute or worsening abdominal pain concerning for splenic injury (see Red Flags & Refer).[2]
Treatment Targets
- Provide effective symptomatic relief (fever, pharyngitis, malaise) while the illness runs its self-limited course.
- Avoid the single most common, avoidable prescribing error in this condition: empiric amoxicillin or ampicillin for undifferentiated pharyngitis in an adolescent or young adult, which risks the aminopenicillin-associated exanthem and a false lifelong penicillin-allergy label.
- Prevent splenic rupture through clear, specific, time-bound activity restriction counseling — not a vague "take it easy" instruction.
- Recognize the narrow, specific list of complications (impending airway obstruction, severe autoimmune hemolytic anemia, severe thrombocytopenia, and other genuinely severe presentations) where corticosteroids are appropriate, while avoiding routine corticosteroid or antiviral use in uncomplicated disease where neither adds meaningful benefit.
- Identify and refer red-flag presentations (splenic rupture, airway compromise, hepatitis, hematologic or neurologic complications) rather than managing them as routine mono.
- Set realistic expectations for the illness course and, in particular, for often-prolonged post-viral fatigue and a graded return to activity.
- Recognize when a mono-like presentation is actually CMV, acute HIV, toxoplasmosis, or streptococcal pharyngitis, since each changes management.
Choose Initial Treatment
Every patient with mono, regardless of severity
1st line, all patients supportive symptomatic care — rest, hydration, and acetaminophen or an NSAID for fever/pharyngitis (see Drug Tables) — is the actual mainstay of therapy; nothing pharmacologic shortens the illness or reduces complication risk in an uncomplicated case.[2]
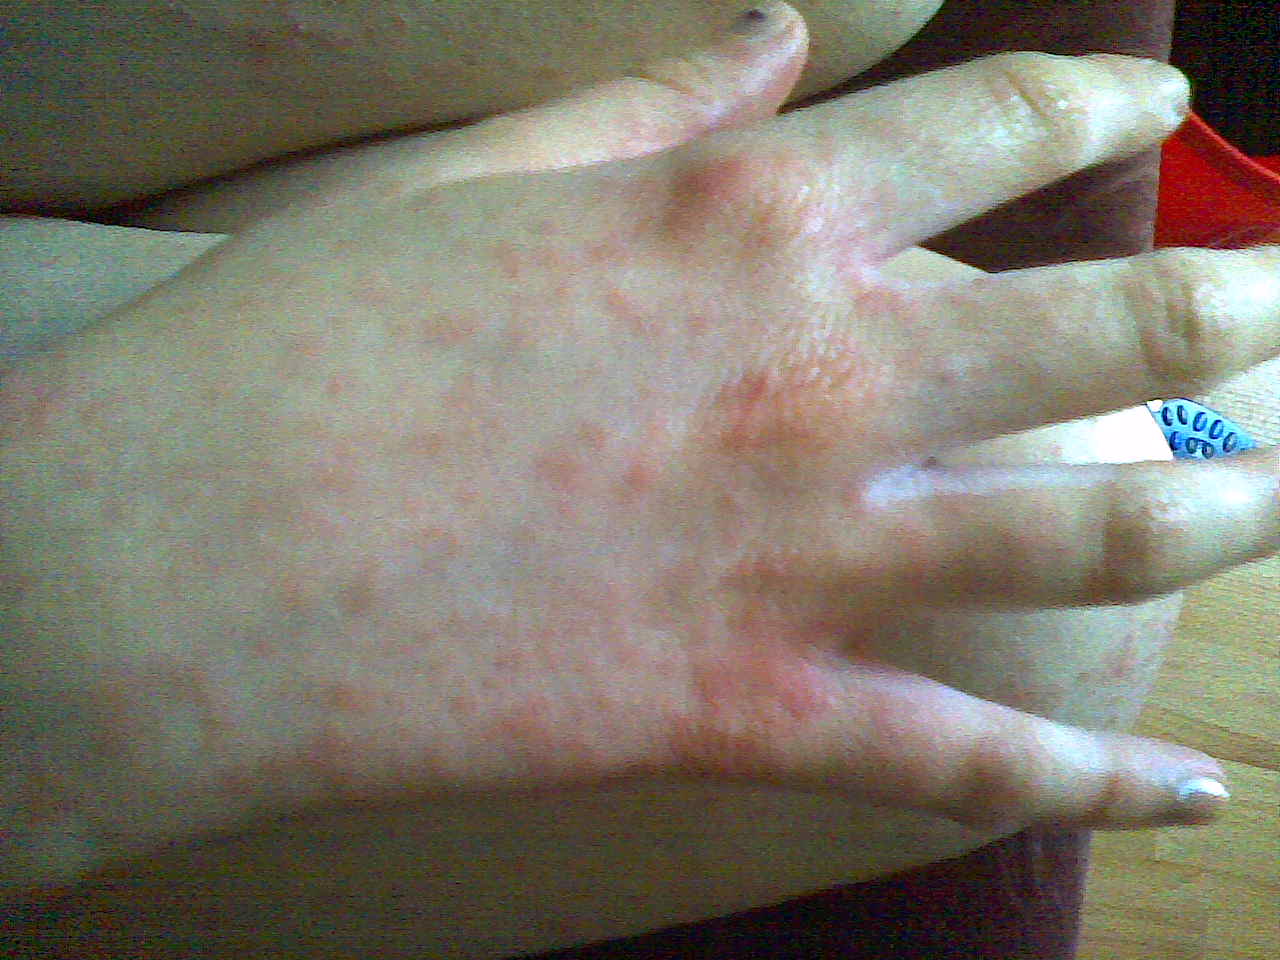
Central teaching point — do not give amoxicillin or ampicillin empirically for undifferentiated sore throat in an adolescent or young adult without a confirmed alternative diagnosis. When either aminopenicillin is given to a patient with unrecognized mono, it produces a diffuse, often pruritic, morbilliform (maculopapular) exanthem — typically appearing several days into the antibiotic course and spreading over the trunk and extremities, sometimes involving the palms and soles. Historical estimates from the ampicillin era put this at 90-100% of mono patients given the drug; more current data, largely reflecting amoxicillin rather than ampicillin and modern diagnostic practice, put the true incidence meaningfully lower — around 15-33% in recent reviews, with one hospitalized-children cohort finding a 29.5% rash rate specifically attributable to amoxicillin.[3][4] The leading explanation is a transient, virus-mediated reduction in antigenic tolerance — essentially a temporary immune-system quirk of acute EBV infection — producing a delayed-type hypersensitivity-like reaction to the drug, rather than a true IgE-mediated penicillin allergy.[3] This distinction has real, lasting consequences: the rash does not, by itself, need to be recorded as a penicillin allergy, and does not automatically require avoiding penicillins in the future. Reserve formal allergy testing for a patient or family who wants diagnostic certainty (for example, before an anticipated future course of a beta-lactam), rather than either reflexively labelling every case a true allergy or dismissing the possibility outright — a modest but real subset of patients has shown persistent sensitization on later testing.[3]
Antibiotics — reserve for a confirmed, separate indication
Confirmed concurrent group A streptococcal pharyngitis routine antibiotic use is not warranted for mono itself, but antibiotics may be considered when a rapid strep test or throat culture confirms true concurrent streptococcal pharyngitis — test "if indicated" by the clinical picture, rather than treating empirically.[2] When treatment is genuinely indicated, choose a non-aminopenicillin option (penicillin V or cephalexin — see Drug Tables) specifically to avoid the exanthem risk described above, particularly before the mono diagnosis has been excluded.
Antivirals — not recommended for uncomplicated disease
Do not use a Cochrane review of antiviral agents (acyclovir, valacyclovir, valomaciclovir) found only very-low-quality evidence of modest, not clearly clinically meaningful, benefit in acute uncomplicated mono — antivirals reduce oropharyngeal viral shedding but do not reliably shorten illness duration or improve symptoms in an immunocompetent host, and routine use is not recommended.[6][2]
Corticosteroids — a genuinely narrow, specific indication list
Not for routine symptom relief a Cochrane review of 7 randomized trials (362 participants, ages 14-30) found that corticosteroids offered, at most, a modest sore-throat pain benefit at 12 hours that had disappeared by 24-36 hours, with no significant benefit for fever, pharyngitis duration, fatigue, or anorexia across most trials — there is no compelling reason to reach for a corticosteroid over acetaminophen or an NSAID for ordinary symptom control.[5]
Reserve for 3 specific situations impending airway obstruction, autoimmune hemolytic anemia, and thrombocytopenia are the specific severe complications where corticosteroids have a genuine, accepted role, alongside other severe disease at a specialist's direction.[7] A single acute dose of dexamethasone (roughly 0.3 mg/kg, up to 10-15 mg) or prednisolone (roughly 30-60 mg) is a reasonable option for impending airway obstruction pending urgent evaluation; a short, specialist-guided tapering corticosteroid course is used for severe hemolytic anemia or thrombocytopenia (see Drug Tables).[8][7]
Activity restriction — the splenic-rupture safety rule
Splenic rupture prevention
Restrict all athletic and strenuous physical activity for a minimum of 3 weeks from symptom onset — current guidelines and 2 large retrospective case series of the rare but dangerous complication of splenic rupture support this window.[2] Splenic rupture occurs in only 0.1-0.2% of mono cases, but 80-86% of cases are spontaneous (nontraumatic) rather than injury-related, carry up to 9% mortality, and cluster early: 73.8% occur within 21 days of symptom onset and 90% by day 31 — though cases have been documented up to 8 weeks after illness onset.[2] For contact or collision sports specifically, extending restriction toward 4 weeks (matching this chapter's Emergency Care BC and sports-medicine literature sourcing) is a reasonable, commonly used extension of the same 3-week minimum, particularly where return timing is being decided through shared decision-making with the patient.[8][9]
Resume activity only once the patient feels clinically well and is afebrile, beginning with light, noncontact activity before any contact sport; use shared decision-making, not a rigid single date, to time the return, and do not use ultrasound-measured spleen size to accelerate the timeline — it has not been shown to reliably do so.[2]
Non-Pharmacologic Treatment
- Rest and adequate hydration — the basic supportive backbone of care for the full symptomatic period.[2]
- Warm saltwater gargles and throat lozenges for pharyngitis, as tolerated.
- Strict avoidance of contact sports, heavy lifting, and any vigorous or high-abdominal-pressure activity for a minimum of 3 weeks (commonly extended toward 4 weeks for contact/collision sports) — see the Activity Restriction rule in Choose Initial Treatment. This is a genuine, specific counseling point, not a vague "take it easy."[2][8]
- Avoid excessive or combined use of acetaminophen and alcohol, and other hepatotoxic exposures, given the common (though usually mild and self-limited) hepatic transaminase elevation seen in mono.[2]
- Avoid aspirin in children and adolescents with any acute viral illness, including mono, given the recognized association with Reye syndrome — use acetaminophen or an NSAID instead (see Drug Tables).[2]
- Do not order routine abdominal ultrasonography, particularly in athletes — it does not reliably predict rupture risk or safely expedite return to play, per the American Medical Society for Sports Medicine's Choosing Wisely recommendation.[2]
- Counsel on transmission: primarily through saliva (kissing, shared drinks/utensils), with a long incubation period (roughly 4-7 weeks) during which the person was already contagious before symptoms appeared — reassure that isolation once ill is not required, since most transmission in the community comes from asymptomatic shedders.[1][2]
- Set explicit expectations for fatigue: the acute illness typically lasts 3 days to about 8 weeks, but a meaningful minority of patients report persistent fatigue for 6 months or longer — this is a genuine, common feature of recovery, not a sign that something is being missed, and warrants proactive counseling rather than waiting for the patient to ask.[2]
Special Populations
Pregnancy
Primary EBV infection in pregnancy is not associated with the same well-documented congenital risk profile as primary CMV infection, which makes distinguishing the two — with EBV-specific serology plus CMV IgM when heterophile testing is negative or ambiguous — genuinely important in a pregnant patient with a mono-like illness, not simply an academic exercise (see Assessment & Diagnosis).[2] Confirmed primary CMV infection in pregnancy should prompt obstetric/maternal-fetal medicine referral given the established risk of congenital CMV infection; confirmed primary EBV mono is managed the same supportively as in a non-pregnant patient, with acetaminophen preferred over NSAIDs for symptom relief per usual pregnancy-safety principles, and the same activity-restriction counseling.
Breastfeeding
Acetaminophen is compatible with breastfeeding and is the preferred symptomatic option. There is no specific breastfeeding restriction related to mono itself once the mother is clinically able to care for her infant as usual.
Pediatrics
Children younger than 5 years present less classically (more rash, more palpable splenomegaly, more prominent upper respiratory symptoms) and have a substantially higher heterophile-test false-negative rate — a negative monospot is considerably less reassuring in this age group, and EBV-specific serology should be pursued with a lower threshold when suspicion remains.[2] Upper airway obstruction from tonsillar/adenoidal hypertrophy is specifically more common in young children given their relatively smaller airway caliber — maintain a lower threshold for urgent evaluation of stridor, drooling, or respiratory distress in this age group.[2] Avoid aspirin in any child or adolescent with mono given the Reye syndrome association with viral illness.[2]
Immunocompromised patients (including transplant recipients)
EBV infection carries meaningfully higher stakes in immunodeficiency: it can drive severe, potentially fatal disease in primary immunodeficiency, including X-linked lymphoproliferative disease, and transplant recipients on immunosuppression are at increased risk of EBV-driven post-transplant lymphoproliferative disease (PTLD), which carries a reported mortality of roughly 50%.[2] Maintain a low threshold for early specialist (infectious diseases/transplant/hematology-oncology) involvement in any immunocompromised patient with a suspected or confirmed EBV illness rather than managing it as routine mono. Patients with HIV can also develop EBV-driven lymphadenopathy, atypical lymphoproliferation, and, less commonly, malignant transformation.[2]
Competitive athletes
Because the diagnosis directly drives weeks of activity restriction, pursue EBV-specific serology when heterophile testing is negative but clinical suspicion remains, rather than accepting diagnostic uncertainty.[2] Time return to play using the activity-restriction rule in Choose Initial Treatment and shared decision-making — not routine ultrasound, which has not been shown to safely expedite return.[2]
Renal and hepatic impairment
Reduce the acetaminophen ceiling dose in significant hepatic impairment or if transaminases are markedly elevated, and avoid NSAIDs in significant renal impairment or volume depletion. No specific mono-related adjustment is needed for the antibiotics or corticosteroids in this chapter beyond their usual product-monograph renal/hepatic dosing guidance.
Monitoring & Follow-Up
- Most patients recover fully with supportive care over 3 days to roughly 8 weeks; proactively counsel that persistent fatigue for 6 months or longer occurs in a meaningful minority and does not, by itself, indicate a missed diagnosis or complication.[2]
- Reinforce and confirm adherence to the activity-restriction timeline at every follow-up contact through at least the 3-4 week window — this is the single most important safety-net message for this condition.
- Safety-net advice: return promptly for new or worsening abdominal pain (splenic rupture), new pallor/jaundice/dark urine (hemolytic anemia), easy bruising or bleeding (thrombocytopenia), or any airway symptoms, at any point during recovery — not only in the first days of illness.
- If a rash developed after amoxicillin or ampicillin, document it clearly as a probable non-allergic, virus-mediated drug-virus reaction rather than a confirmed penicillin allergy, and discuss formal allergy testing as an optional, patient-directed next step rather than a required one (see Choose Initial Treatment).[3]
- Reassess CBC and liver enzymes if they were abnormal at diagnosis, until normalization, particularly if any hematologic or hepatic complication was identified.
- Confirm resolution of fever and that the patient feels clinically well before endorsing any return to activity, using shared decision-making for exact timing.[2]
Common Errors to Avoid
- Prescribing amoxicillin or ampicillin empirically for undifferentiated sore throat in an adolescent or young adult without testing for strep or considering mono — the single most common, avoidable prescribing error in this condition.[3]
- Automatically documenting a "penicillin allergy" after an aminopenicillin-associated rash in mono without recognizing this is typically a non-allergic, virus-mediated reaction — a mislabel that can follow a patient for life and unnecessarily restrict future antibiotic choices.[3]
- Relying on a normal splenic exam to lift activity restrictions early — physical examination for splenomegaly is genuinely unreliable (sensitivity as low as 20%).[2]
- Dismissing the diagnosis based on a single negative monospot obtained in the first week of illness, or in a child under 5 — both are recognized false-negative scenarios.[2]
- Using corticosteroids or antivirals routinely for uncomplicated mono symptom relief — neither adds meaningful benefit over acetaminophen/NSAIDs, per Cochrane-level evidence.[5][6]
- Ordering routine abdominal ultrasonography in athletes to try to expedite return to play — not supported, and specifically discouraged by Choosing Wisely.[2]
- Giving aspirin to a child or adolescent with mono, given the Reye syndrome association with viral illness.[2]
- Missing a heterophile-negative CMV, acute HIV, or toxoplasmosis presentation by treating every mono-like illness as confirmed EBV mono without considering the differential.
- Underestimating splenic rupture risk by giving vague "take it easy" advice instead of an explicit, time-bound (minimum 3-4 week) activity restriction.[2]
- Missing early signs of upper airway obstruction, especially in a young child, by treating tonsillar swelling as routine pharyngitis rather than screening for stridor, drooling, or respiratory distress.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Symptomatic / Supportive Care — First Line for Every Patient
Nothing pharmacologic shortens the illness itself; these agents treat fever, pharyngitis, and malaise while the illness runs its course.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Acetaminophen | Adults: 650-1000 mg PO Q4-6H PRN, maximum 3-4 g/day | Hepatotoxicity with excessive use, alcohol use, or hepatic impairment | Increased hepatotoxicity risk with alcohol or other hepatotoxic drugs | Preferred first choice given the common, usually mild, hepatic transaminase elevation seen in mono. |
| Ibuprofen | Adults: 400-600 mg PO Q6-8H PRN with food | GI upset, renal effects with dehydration, bleeding risk | Increased GI bleed risk with anticoagulants/corticosteroids; reduces antihypertensive/diuretic efficacy | Use cautiously, or avoid, if thrombocytopenia or bleeding signs are present. |
| Naproxen | Adults: 250-500 mg PO BID PRN with food | GI upset, renal effects with dehydration, bleeding risk | Same NSAID-class interactions as ibuprofen | Longer dosing interval than ibuprofen; same thrombocytopenia/bleeding caution. |
Antibiotics to Avoid — Empiric Use in Suspected or Unconfirmed Mononucleosis
The central teaching point of this chapter. Do not prescribe either drug empirically for undifferentiated pharyngitis in an adolescent or young adult without a confirmed alternative diagnosis.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Amoxicillin | Not applicable: Avoid empiric use in this clinical scenario | Causes a diffuse, itchy morbilliform (maculopapular) exanthem in a meaningful proportion of patients with unrecognized mono — modern estimates roughly 15-33%, one hospitalized-children cohort found 29.5% | No specific interaction concern relevant here — the issue is the underlying illness, not a drug interaction | This is a non-allergic, transient virus-mediated drug reaction, not true IgE-mediated penicillin allergy — do not record it as a confirmed allergy without formal testing |
| Ampicillin | Not applicable: Avoid empiric use in this clinical scenario | The original, most extensively documented aminopenicillin-mono exanthem — historical estimates up to 90-100% | Same as amoxicillin | Same non-allergic mechanism and counseling as amoxicillin above |
Antibiotics — Confirmed Concurrent Group A Streptococcal Pharyngitis Only
Antibiotics are not indicated for mono itself; use only when a rapid strep test or culture confirms true concurrent streptococcal pharyngitis, and choose a non-aminopenicillin agent.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Penicillin V | Adults: 300-600 mg (500,000-1,000,000 units) PO QID x 10 days | GI upset, hypersensitivity reactions | May reduce efficacy of the typhoid vaccine; minimal other significant interactions | A non-aminopenicillin beta-lactam — avoids the amoxicillin/ampicillin exanthem risk while still treating confirmed strep. |
| Cephalexin | Adults: 500 mg PO BID-TID x 10 days | GI upset, hypersensitivity reactions (low cross-reactivity with penicillin allergy) | May increase metformin levels; possible increased INR with warfarin | The aminopenicillin-mono exanthem has not been consistently reported with cephalosporins at anywhere near the same frequency. |
Corticosteroids — Reserved for Specific Severe Complications Only
A Cochrane review found no compelling benefit for routine symptom control; reserve for impending airway obstruction, severe autoimmune hemolytic anemia, or severe thrombocytopenia.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Dexamethasone | Adults: 0.3 mg/kg PO/IV single dose, typically 10 mg (up to 15 mg) | Hyperglycemia, insomnia, mood change — minimal with a single dose | May reduce efficacy of live vaccines given concurrently; increased hyperglycemia risk with other glucose-elevating drugs | Single acute dose for impending upper airway obstruction, pending urgent evaluation — not a routine symptom-control measure. |
| Prednisone | Adults: Typically starting around 1 mg/kg/day, short taper per specialist direction | Hyperglycemia, insomnia, mood change, GI upset; adrenal suppression with prolonged use | Increased hyperglycemia risk with other glucose-elevating drugs; increased GI bleed risk with NSAIDs | Short, specialist-directed tapering course for confirmed severe autoimmune hemolytic anemia or severe/bleeding thrombocytopenia — not for uncomplicated fatigue or sore throat. |
| Methylprednisolone | Adults: Per product monograph and specialist direction | Same class effects as prednisone/dexamethasone | Same as prednisone/dexamethasone | IV alternative for the same narrow complication list when the oral route is not feasible (hospitalized/severe presentation). |
Antiviral Agents — Not Recommended for Uncomplicated Disease
Included specifically to correct a common misconception. Cochrane-level evidence shows only very-low-quality, non-clinically-meaningful benefit in an immunocompetent host.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Valacyclovir | Not applicable: Not indicated for uncomplicated mono in an immunocompetent host | Not applicable when not used; headache, GI upset if prescribed | Reduce dose with renal impairment | Reduces oropharyngeal EBV shedding but does not reliably improve symptoms or shorten illness duration — not indicated for routine use. |
| Acyclovir | Not applicable: Not indicated for uncomplicated mono in an immunocompetent host | Not applicable when not used; headache, GI upset, nephrotoxicity with inadequate hydration if prescribed | Reduce dose with renal impairment | Same Cochrane-level conclusion as valacyclovir — not indicated for routine use. |
Symptomatic Relief of the Aminopenicillin-Associated Rash, If It Occurs
The rash itself is generally self-limited over 1-2 weeks and is not, by itself, evidence of a true allergy requiring lifelong avoidance.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Cetirizine | Adults: 10 mg PO once daily PRN | Mild sedation (less than diphenhydramine) | Additive sedation with other CNS depressants | Symptomatic itch relief only; stopping the inciting antibiotic (once no longer needed) and reassurance are the main management. |
References
- Primary Epstein-Barr virus infection — Journal of Clinical Virology (Dunmire SK, Verghese PS, Balfour HH Jr). J Clin Virol 2018;102:84-92
- Infectious Mononucleosis: Rapid Evidence Review — American Family Physician (Sylvester JE, Buchanan BK, Silva TW). Am Fam Physician 2023;107(1):71-78
- Amoxicillin rash in infectious mononucleosis — Cleveland Clinic Journal of Medicine (Kano Y). Cleve Clin J Med 2025;92(6):335-337
- Incidence of Rash After Amoxicillin Treatment in Children With Infectious Mononucleosis — Pediatrics (Chovel-Sella A, Ben Tov A, Lahav E, Mor O, Rudich H, Paret G, Reif S). Pediatrics 2013;131(5):e1424-e1427
- Steroids for symptom control in infectious mononucleosis — Cochrane Database of Systematic Reviews (Rezk E, Nofal YH, Hamzeh A, et al.). Cochrane Database Syst Rev 2015;(11):CD004402
- Antiviral agents for infectious mononucleosis (glandular fever) — Cochrane Database of Systematic Reviews (De Paor M, O'Brien K, Fahey T, Smith SM). Cochrane Database Syst Rev 2016;(12):CD011487
- Corticosteroids for infectious mononucleosis — Canadian Family Physician (Gomes K, Goldman RD). Can Fam Physician 2023;69(2):101-102
- Infectious Mononucleosis: Diagnosis and Treatment — Emergency Care BC (Heilman J, Thurley N). Emergency Care BC, updated 12 Jul 2021
- Determination of safe return to play for athletes recovering from infectious mononucleosis: a review of the literature — Clinical Journal of Sport Medicine (Waninger KN, Harcke HT). Clin J Sport Med 2005;15(6):410-416
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.