Nonpurulent Cellulitis
Nonpurulent Cellulitis
References
- Cellulitis: a review — JAMA (Raff AB, Kroshinsky D). JAMA 2016;316(3):325-337
- Skin diversity erythema description guidance — British Association of Dermatologists (Gass M, Dadzie OE, Dlova N, et al.). February 2021
- Practice guidelines for the diagnosis and management of skin and soft tissue infections: 2014 update by the Infectious Diseases Society of America — Clinical Infectious Diseases (Stevens DL, Bisno AL, Chambers HF, et al.). Clin Infect Dis 2014;59(2):e10-e52
- Compression therapy to prevent recurrent cellulitis of the leg — New England Journal of Medicine (Webb E, Neeman T, Bowden FJ, et al.). N Engl J Med 2020;383(7):630-639
Clinical Snapshot
Nonpurulent cellulitis is an acute infection of the dermis and subcutaneous tissue, usually driven by beta-hemolytic streptococci.[1] It produces diffuse warmth, tenderness, edema, and poorly defined erythema or discoloration. The first therapeutic decision is not "which antibiotic?" but "is this truly cellulitis, and is it uncomplicated?" Bilateral lower-leg redness is far more likely to be a noninfectious mimic than bacterial cellulitis.
Recognize the Condition
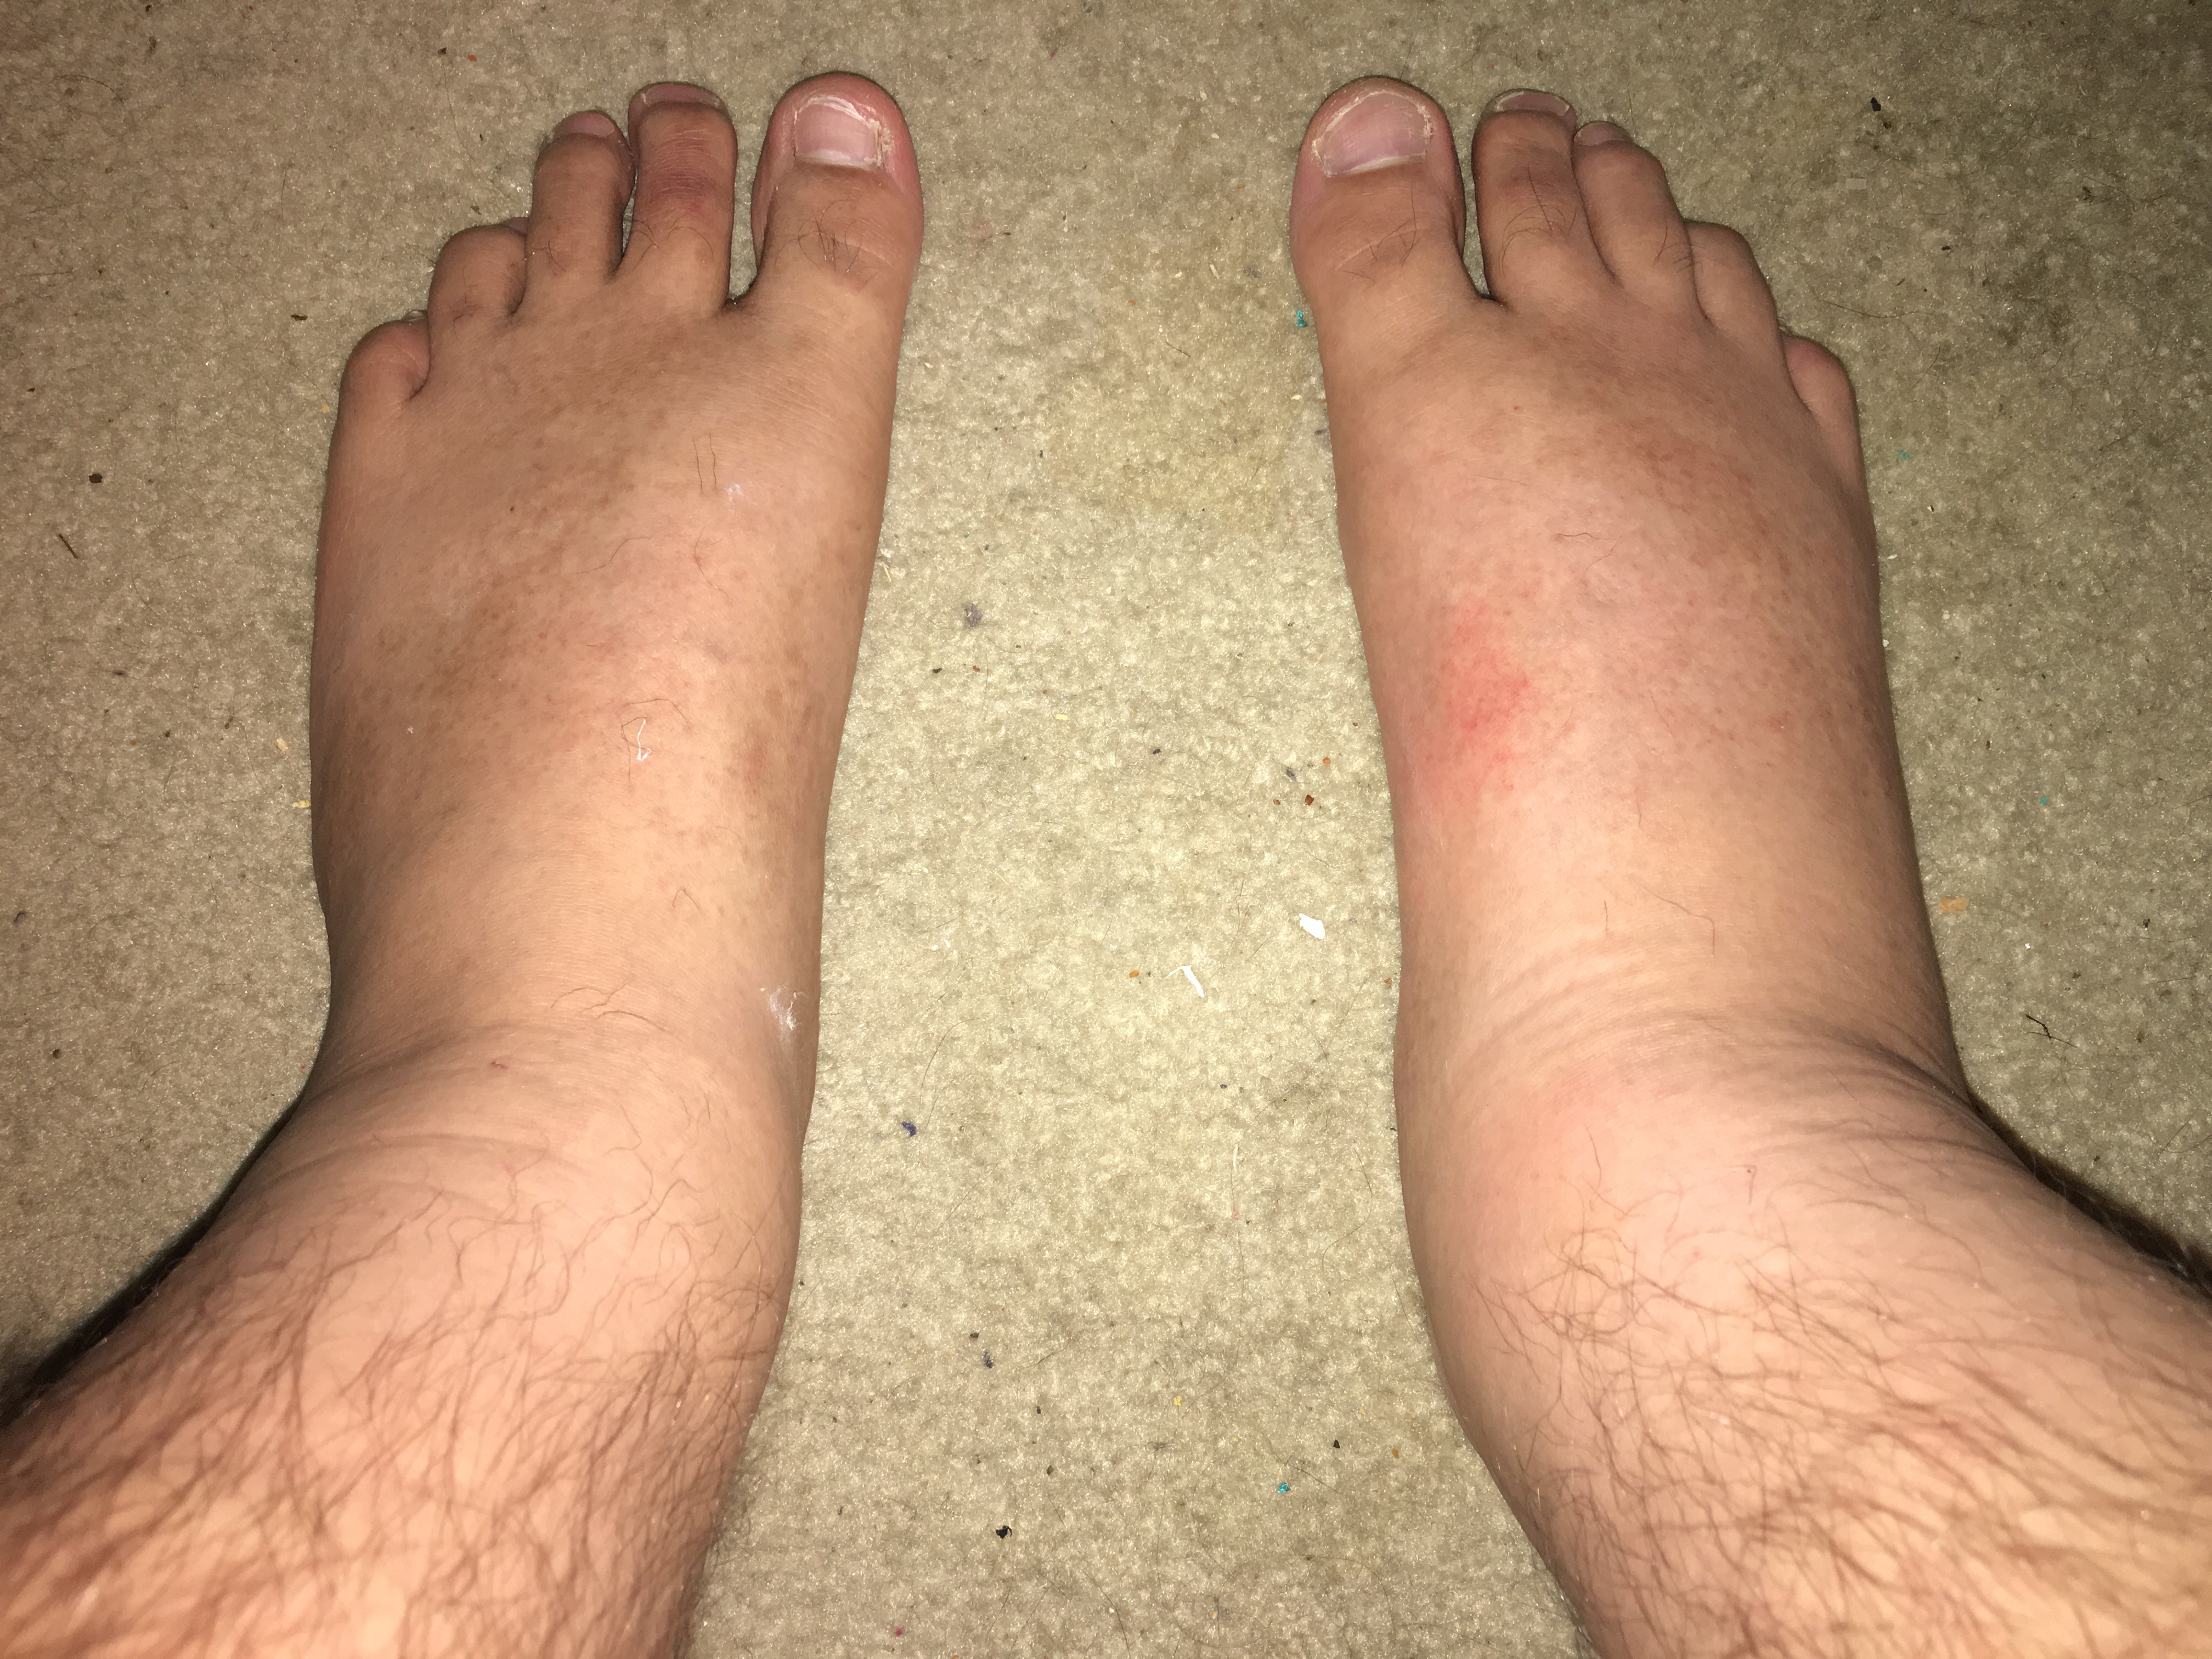
- Acute unilateral warmth, tenderness, and swelling.
- Poorly demarcated erythema in light skin; in darker skin, inflammation may appear purple, brown, grey, or dusky, or may be better detected by warmth, edema, and tenderness than by colour change.[2]
- May have lymphangitic streaking or regional lymphadenopathy.
- No drainable abscess or dominant purulent focus — this is what separates it from purulent cellulitis.
Risk Factors
- Skin breaks, ulcers, wounds, fissures, or excoriations.
- Interdigital tinea pedis.
- Chronic edema/lymphedema and venous disease.
- Previous cellulitis.
- Diabetes, obesity, or immunosuppression.
Red Flags & Refer
Urgent/emergency assessment for any of the following:
- Pain out of proportion to appearance.
- Rapid progression.
- Bullae.
- Necrosis.
- Crepitus.
- Numbness.
- Hypotension.
- Severe systemic toxicity.
- Orbital/facial deep-space involvement.
- Septic joint concern.
- An immunocompromised patient with severe infection.
- Failure of oral therapy.
Assessment & Diagnosis
Confirm infection
Document onset, borders, warmth, tenderness, edema, portal of entry, systemic symptoms, and comorbidities. Check interdigital spaces for tinea. Routine cultures are not useful in uncomplicated nonpurulent cellulitis because there is no accessible infected material to sample.[3]
Actively exclude mimics
Venous stasis dermatitis
Commonly bilateral, chronic, itchy/scaly; improves with elevation.
Deep vein thrombosis
Swelling/pain without the classic superficial inflammatory pattern — investigate when risk is significant.
Gout
Joint-centred severe pain.
Herpes zoster
Grouped vesicles in a dermatomal pattern with a neuropathic prodrome.
Treatment Targets
- Stop spread and systemic progression.
- Resolve pain, warmth, and edema.
- Prevent abscess, bacteremia, and recurrence.
- Correct the portal of entry — tinea pedis, chronic skin breakdown, ulcers.
Choose Initial Treatment
Mild, uncomplicated disease
1st line: oral cephalexin targeting streptococci/MSSA.
Do not add MRSA-active therapy routinely.
Moderate/severe disease, or inability to take oral therapy
1st line: IV cefazolin and urgent higher-level assessment.
Severe beta-lactam allergy
Alternative: clindamycin (oral).
Alternative for severe/parenteral need: vancomycin IV.
Non-Pharmacologic Treatment
- Elevate the affected limb above heart level when feasible.
- Use cool wet compresses for comfort.
- Mark the erythema border and record the time/date for objective follow-up.
- Treat tinea pedis, ulcers, eczema, and edema.
- For chronic lower-limb edema, initiate appropriate compression once acute pain/inflammation permits and contraindications are excluded — daily compression stocking use reduces recurrent cellulitis.[4]
Pharmacologic Treatment Options
| Drug / intervention | Role | Dose / use | Important adverse effects | Teaching points |
|---|---|---|---|---|
| Cephalexin Preferred | Mild outpatient 1st line | 500 mg PO QID, generally 5 days; extend if response is incomplete | GI upset, hypersensitivity | Renal adjustment may be required. |
| Cefadroxil Alternative | Outpatient alternative | 500 mg PO daily-BID | GI upset, hypersensitivity | Similar MSSA/streptococcal coverage to cephalexin. |
| Clindamycin Alternative | Beta-lactam allergy | 300-450 mg PO TID | C. difficile infection risk | Use when a beta-lactam cannot be used and local susceptibility is acceptable. |
| Cefazolin Preferred (parenteral) | Moderate/severe disease requiring IV therapy | 1-2 g IV Q8H | Hypersensitivity, phlebitis | Hospital/ambulatory IV management of streptococcal/MSSA cellulitis. |
| Vancomycin Special situation | MRSA concern or severe beta-lactam allergy | Weight-based IV dosing with institutional AUC monitoring | Nephrotoxicity, infusion reaction | Reserve for severe disease with MRSA concern or when preferred beta-lactams cannot be used. |
| Sulfamethoxazole/Trimethoprim Special situation | Add-on MRSA coverage only | 1-2 DS tablets PO BID | Hyperkalemia, rash, cytopenias | Only when MRSA risk/purulence is present; not preferred as streptococcal monotherapy. |
Special Populations
Pregnancy
Cephalexin, cefazolin, and other appropriate beta-lactams are generally preferred when the organism is susceptible. Clindamycin is an alternative when beta-lactams cannot be used.
Diabetes
Do not automatically treat simple cellulitis as a diabetic-foot infection. If ulceration, ischemia, neuropathy, or deep-foot involvement is present, move to a diabetic-foot-infection pathway instead.
Severe beta-lactam allergy
Confirm the allergy phenotype. Severe delayed reactions such as SJS/TEN require avoidance of implicated beta-lactams; use a non-beta-lactam regimen guided by severity and local susceptibility.
Monitoring & Follow-Up
Reassess within 48-72 hours. The skin can look transiently more inflamed in the first 24-48 hours even when therapy is effective — judge the whole patient (pain, fever, spread rate, systemic status), not the erythema border alone. Improvement is demonstrated by stabilization of borders, less tenderness/warmth, and improved systemic symptoms.
Treatment Failure / Next Step
- Confirm diagnosis — reconsider stasis dermatitis, DVT, gout, and zoster.
- Look for a hidden abscess, foreign body, or deeper focus.
- Check adherence and antibiotic exposure.
- Add MRSA-active therapy only if purulence or MRSA risk emerges.
- Escalate to IV/hospital care if progression continues or systemic illness develops.
Common Errors to Avoid
- Treating bilateral red legs as cellulitis without reconsidering stasis dermatitis.
- Adding MRSA coverage to every nonpurulent cellulitis case.
- Calling mild early inflammatory extension at 24 hours an automatic treatment failure.
- Ignoring tinea pedis and chronic edema as portals of entry.
- Missing necrotizing fasciitis because the erythema is not dramatic.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Oral therapy
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Cephalexin | Adults: 500 mg PO QID, generally 5 days; extend if response is incomplete Children: 25-50 mg/kg/day divided Q6H PO | GI upset, hypersensitivity | Mild outpatient 1st line; renal adjustment may be required. |
| Cefadroxil | Adults: 500 mg PO daily-BID Children: 20 mg/kg PO once daily (max 500 mg/day) | GI upset, hypersensitivity | Outpatient alternative. |
| Cefuroxime | Adults: 500 mg PO BID Children: 20-30 mg/kg/day divided Q12H PO (max 500 mg/dose) | GI upset, hypersensitivity | Selected allergy/second-line option when a first-generation cephalosporin is unsuitable. |
| Clindamycin | Adults: 300-450 mg PO TID Children over 1 month: 25-40 mg/kg/day divided Q8H PO (max 450 mg/dose) | C. difficile infection risk | Beta-lactam allergy option when local susceptibility is acceptable. |
Parenteral therapy (moderate/severe)
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Cefazolin | Adults: 1-2 g IV Q8H Children: 50-100 mg/kg/day divided Q8H IV (max 6000 mg/day) | Hypersensitivity, GI upset, phlebitis | Hospital/ambulatory IV first line. |
| Cloxacillin | Adults: 2 g IV Q6H (common hospital dose) Children: 25-50 mg/kg Q6H IV (max 2000 mg/dose) | Hypersensitivity, hepatic effects, phlebitis | Selected IV MSSA-dominant infection. |
| Vancomycin | Adults: 1 g Q12H (or 15 mg/kg Q8-12H) IV, institutional AUC monitoring Children: 45-60 mg/kg/day divided Q6-8H IV | Nephrotoxicity, infusion reaction | MRSA or severe beta-lactam allergy. |
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.