Pubic Lice
Clinical Snapshot
Pubic lice (pediculosis pubis, "crabs") is an infestation of coarse body hair — almost always the pubic and perianal area — by Phthirus pubis (also written Pthirus pubis), a human louse species with a short, broad, crab-shaped body and thick, claw-tipped second and third legs adapted to grip coarse hair shafts rather than the finer hair of the scalp.[1][2] Unlike head lice (Pediculus humanus capitis) and body lice (Pediculus humanus corporis), which are covered in their own separate chapters in this library, pubic lice is classified as a sexually transmitted infection: it is transmitted primarily through sexual or other close intimate contact, and only uncommonly through sharing contaminated clothing, bedding, or towels.[2][1] This single fact — that pubic lice is confirmation of an STI, not simply a nuisance infestation — drives almost every distinctive element of its management: routine screening for other sexually transmitted infections, notification and simultaneous treatment of sexual partners, and a genuinely different approach when lice or nits are found on the eyelashes of a child.
Global prevalence estimates for pubic lice generally fall in the range of 1-2% of the population, with individual studies reporting figures anywhere from well under 1% to over 10% depending on the population studied.[1] Co-infection with another sexually transmitted infection is genuinely common — a European guideline reports roughly 30% of patients with pediculosis pubis have a concomitant STI, and the Canadian source anchoring this chapter's core clinical content specifically notes that co-infection "can be common" — which is why STI co-testing is a routine, not optional, part of every encounter (see Assessment & Diagnosis and Choose Initial Treatment).[3][2] Incidence has also been declining for decades in step with the rise of pubic hair removal, which destroys the parasite's natural habitat: a UK genitourinary medicine clinic reported rates falling from 3.5% of men and 2% of women in 1991 to under 1% by 2004, and a 2014 analysis found a strong statistical correlation between the population-level rise in pubic hair removal and the fall in pubic lice incidence.[4] Despite this decline, pubic lice remains a real, current presentation pharmacists are well positioned to recognize and manage.
Recognize the Condition
Symptoms
Pruritus in the affected area is the dominant presenting symptom, and is usually what brings a patient to care — either the itching itself, or noticing lice or nits on their pubic hair.[2][5] Itching reflects a hypersensitivity reaction to louse saliva injected during feeding, and the affected skin can also show a diffuse irritant dermatitis from scratching.[2] With extensive infestation, mild fever or malaise can accompany it.[2]
Where to look
Adult lice and nits attach near the base of coarse hair shafts, most often in the pubic and perianal area, but Phthirus pubis can also be found on any other area of coarse body hair — the abdomen, thighs, chest, axillae, moustache and beard — and, especially in children, the eyebrows and eyelashes, since, unlike head lice, this species is not well adapted to fine scalp hair.[2][1] Eyelash and eyebrow involvement (phthiriasis palpebrarum) is proportionally more common in children than adults and carries its own distinct management approach and safeguarding consideration — see Special Populations and the eyelash-specific protocol in Choose Initial Treatment.[1]
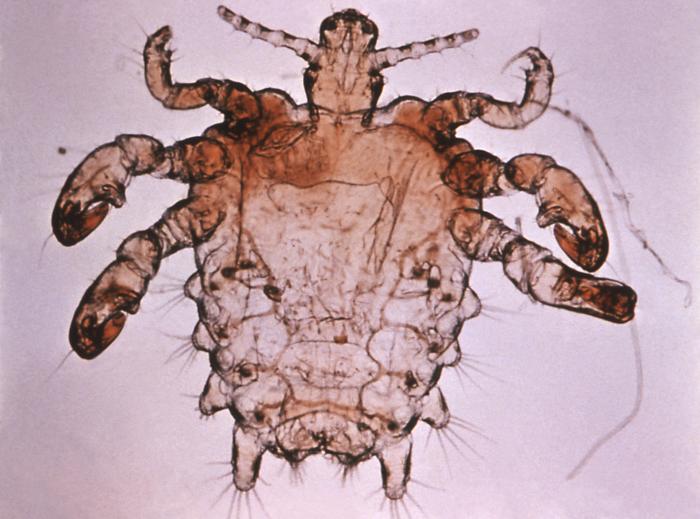
Physical findings
- Nits — small (about 0.8 mm x 0.3 mm), oval, opalescent eggs cemented firmly to the base of the hair shaft; difficult to remove even after treatment.[2]
- Adult lice — about 1 mm long, attached near the base of the hair, appearing as small brown or tan specks; may be hard to identify unless engorged with blood.[2]
- Maculae ceruleae — small (under 1 cm), slate blue-grey macules at bite sites, a genuinely distinctive finding; erythematous papules can also occur at bite sites.[3][2]
- Crusts or rust-coloured flecks of louse fecal material on the skin, and blood staining on underwear.[2]
- Erythema and irritation from scratching, and inguinal lymphadenopathy in some patients.[2]

Life cycle
The adult louse survives less than 1 month on the host and cannot survive more than 24-48 hours away from a human blood meal; the female lays eggs that typically hatch within about a week (nits can hatch after 6-8 days), which is why correctly timed retreatment matters (see Choose Initial Treatment).[3][2]
Risk Factors
- Sexual or other close intimate/body contact with an infested person — the primary and by far the most common transmission route.[2][1]
- Non-sexual close contact, including sharing personal articles such as clothing or bedding with an infested person — a real but uncommon route, since the louse cannot survive more than 24-48 hours away from a human host.[2][3]
- Multiple sexual partners or other markers of elevated STI exposure risk, given the meaningful rate of co-infection with other sexually transmitted infections.[3]
- For children specifically, close non-sexual contact with an infested parent or caregiver — manual transfer from an infested adult's body hair is a recognized and, for eyelash involvement, probably the more common route of transmission in this age group (see Special Populations).[1]
- Crowded living conditions with limited access to bathing or clean clothing, including settings of war or disaster — pubic lice incidence rises in these populations, similar to the other human lice.[3]
Red Flags & Refer
Pubic lice is usually a straightforward, pharmacist- or primary-care-managed presentation. Escalate beyond routine counselling and OTC treatment for any of the following:
- Pregnancy or breastfeeding — confirm the treatment choice with a physician or nurse practitioner before recommending a pediculicide.[2]
- A patient who requires an alternate treatment to the standard first-line options, or who has significant pruritus not controlled by OTC measures.[2]
- Significant skin excoriation, or signs of a developing secondary bacterial infection (spreading erythema, warmth, purulence, fever) potentially requiring antibiotics.[2]
- Symptoms persisting despite correct use of the recommended treatment and appropriate follow-up — reassess rather than simply repeating the same product a third time (see Treatment Failure/Next Step).[2]
- Lice or nits found on the eyelashes or eyebrows of a child — this needs referral both for the eyelash-specific treatment protocol (standard pediculicides must never be used near the eyes) and for a careful, non-alarmist clinical assessment for the possibility of sexual abuse. Manual transmission from an infested parent's or caregiver's body hair is the more common explanation, but the possibility of abuse should be genuinely considered, not automatically dismissed; involve the appropriate child-protection pathway in your jurisdiction if anything in the history or examination raises real concern.[1][3]
- Any positive finding on STI co-testing — route to the appropriate etiology-specific management pathway (chlamydia, gonorrhea, syphilis, or HIV) rather than treating pubic lice as the entirety of the encounter.[5][2]
Assessment & Diagnosis
Diagnosis is clinical
Diagnosis is based on the typical history (itching in the affected area) together with direct visualization of adult lice and/or nits attached to coarse hair, seen with the naked eye or, if uncertain, with a dermatoscope.[2][5] No laboratory testing is required to diagnose pubic lice itself.
Examination
Examine the pubic and perianal area, and — since Phthirus pubis is not restricted to genital hair — also check other coarse-hair areas (abdomen, thighs, chest, axillae, moustache/beard) and the eyebrows and eyelashes, particularly in a child or when genital examination alone is unrevealing despite a strong history.[2][1]
Differential diagnosis
| Condition | Distinguishing features |
|---|---|
| Scabies | Burrows and intense, often nocturnal itching concentrated in finger webs, wrists, and genitals rather than coarse pubic hair specifically; the causative mite is not visible to the naked eye the way lice and nits are. Can coexist with pubic lice. |
| Folliculitis / irritant or contact dermatitis | No lice or nits found on careful examination of the hair shafts; distribution and morphology reflect a specific irritant or an infected follicle rather than organisms cemented to hair. |
| Seborrheic dermatitis or blepharitis (eyelid involvement) | Phthiriasis palpebrarum is frequently misdiagnosed as ordinary blepharitis or conjunctivitis, since the lice and nits on the lashes are easily missed without careful, magnified examination — genuinely consider phthiriasis palpebrarum in a patient (especially a child) with unexplained, persistent eyelid itching, redness, or crusting.[1] |
| Tinea cruris or candidal intertrigo | Diffuse erythematous, often scaling rash without discrete organisms or nits found on hair. |
STI co-testing — a routine part of this diagnosis, not an optional extra
Because pubic lice is confirmation of a sexually transmitted infection, both Canadian and American guidance are explicit: anyone diagnosed with pubic lice should be evaluated for other sexually transmitted and blood-borne infections, specifically HIV, syphilis, chlamydia, and gonorrhea.[5][2] This is not a defensive add-on — concomitant STI infection is genuinely common in this population.[3] Arrange testing per your local STI screening protocol at the same visit wherever possible, rather than leaving it to a separate encounter the patient may not return for. Treatment of any identified co-infection follows its own etiology-specific management pathway and is outside the scope of this chapter.
Treatment Targets
- Confirm the diagnosis by direct visualization of lice and/or nits before treating, and examine all areas of coarse body hair, not the genital area alone.
- Eradicate the infestation with an appropriate pediculicide, matched to the affected site — standard genital/body-hair agents for pubic and other coarse body hair, and a genuinely different, eye-safe protocol for the eyelashes.
- Screen for other sexually transmitted infections at the same visit — HIV, syphilis, chlamydia, and gonorrhea — given the confirmed sexual-transmission risk.
- Notify and simultaneously treat sexual partners within the relevant look-back window to prevent reinfection and further spread.
- Decontaminate clothing and bedding used in the days before treatment, without resorting to unnecessary fumigation of living spaces.
- Relieve pruritus, which can genuinely persist for days to weeks after successful treatment.
- In a child with eyelash or pubic involvement, carefully and non-judgmentally consider the possibility of sexual abuse alongside the much more common explanation of non-sexual transmission from an infested caregiver, and involve the appropriate safeguarding pathway if genuine concern exists.
- Deliver every part of this care confidentially and without stigma, recognizing that this is an STI diagnosis many patients find difficult to discuss.
Choose Initial Treatment
First-line therapy, applied correctly and to every affected area
1st line permethrin 1% cream (crème rinse) or pyrethrins 0.33% with piperonyl butoxide, applied to cool, dry skin over all suspected areas of infestation — genital and perianal hair, and any other coarse-hair area involved (thighs, trunk, axillae, moustache/beard) — and washed off after 10 minutes.[2][5] Never on the eyelashes or eyebrows these agents must not be applied to the eyes or eyelid margins; eyelash and eyebrow involvement needs the separate protocol below.[5][2]
Application technique and the second treatment
Follow the specific product's own instructions closely — pediculicides are absorbed through the skin and can be toxic with overuse, and overuse itself can cause itchy, irritated skin.[2] Nits remain cemented to the hair shaft even after treatment kills the lice; use fingernails, a fine-tooth comb, or tweezers to physically remove remaining nits.[2] Trimming the pubic hair before treatment is a patient's choice, not a requirement — shaving is not necessary for treatment to succeed.[3][2]
Neither permethrin nor pyrethrin is fully ovicidal, and eggs already laid at the time of treatment can still hatch — many guidelines therefore recommend a routinely scheduled second application at 7-10 days to kill newly hatched nymphs, mirroring the same principle used for head lice pediculicides in this library.[3] Canadian and American guidance frame this somewhat differently: rather than an automatic second dose, offer a follow-up assessment at 9-10 days after treatment (nits can hatch after 6-8 days), and if the patient is unlikely to return for that follow-up, consider recommending retreatment at the initial visit; more generally, re-evaluate at about 1 week if symptoms persist, and retreat if live lice are found or eggs are seen at the hair-skin junction.[2][5]
Reported resistance
Reported resistance to permethrin and pyrethrin has been increasing and is now widespread; if treatment genuinely fails with an appropriately applied first-line agent, move to an alternative agent from a different class rather than simply repeating the same product.[5]
Alternative therapy — for treatment failure or resistance
Alternative malathion 0.5% lotion, applied to affected areas and washed off after 8-12 hours; its odour, longer contact time, and flammability (avoid heat sources, including a hair dryer, during the application period) make it a less attractive first choice, but it remains effective when resistance to the recommended pediculicides is suspected.[5][2]
Alternative oral ivermectin 250 mcg/kg body weight, taken with food (which increases bioavailability and epidermal drug penetration), repeated in 7-14 days since ivermectin has only limited ovicidal activity and will not reliably prevent recurrence from eggs already present at the time of the first dose.[5] No dosage adjustment is required for renal impairment; the safety of multiple doses in severe liver disease has not been established.[5] This is not a Health Canada-approved indication for lice, and oral ivermectin should be a prescriber-directed decision, not a pharmacist-initiated one.
Lindane is not recommended for treatment of pediculosis of any kind, given its toxicity, contraindications in pregnant and breastfeeding patients, children under 10, and patients with extensive dermatitis, and the complexity of correct administration; its marketing authorization has also been withdrawn in the European Union.[5][3]
Eyelash and eyebrow involvement — a genuinely different, eye-safe protocol
Standard pediculicides are not used on or near the eyes.[5][2] A few nits/lice only mechanical removal with fine tweezers, a nit comb, or fingernails is sufficient.[2] Heavier involvement apply an ophthalmic-grade petrolatum ointment (for example, Lacri-Lube or Duolube) to the eyelid margins twice daily for 10 days, or as directed on the product's own package insert — this works by physically suffocating the parasites rather than by a neurotoxic mechanism.[2][5] Do not use ordinary petroleum jelly (e.g., plain Vaseline) for this purpose — it is not recommended for eyelid use and can cause irritation; use a product specifically formulated and labelled for ophthalmic use instead.[2] Remove dead lice and nits with tweezers or fingernails once treatment is complete.
STI co-testing and partner management
Arrange STI co-testing (HIV, syphilis, chlamydia, gonorrhea) at the same visit (see Assessment & Diagnosis).[5][2] Though pubic lice is not a reportable infection, it is highly contagious, and notification of sexual partners, household members, and other close contacts is strongly recommended to help prevent further spread and reinfection.[2] Treat sexual partners from within the previous month simultaneously with the index patient, and advise the patient to avoid sexual contact until both the patient and their partner(s) have completed treatment, clothing and bedding have been decontaminated, and reinfestation has genuinely been ruled out — roughly 10 days is a reasonable practical guide.[5][2] Non-sexual household contacts only need treatment if they themselves show signs of infestation.[2]
Non-Pharmacologic Treatment
Decontaminate clothing and bedding
- Wash clothing, bedding, and towels used in the 2-3 days before treatment in hot water (50°C/122°F or higher), then dry on a hot dryer cycle for about 30 minutes, or dry-clean them.[2][5]
- Items that cannot be washed or dry-cleaned can instead be sealed in a plastic bag for 2 weeks — the louse cannot survive more than 24-48 hours away from a human host, so anything sealed this long will no longer be infested.[2][3]
- Mattresses and carpets can simply be vacuumed; fumigant sprays and broader decontamination of living spaces are not needed.[2][5]
Nit and lice removal
Perform daily checks to physically remove any remaining nits or lice with fingernails, a fine-tooth comb, or tweezers, since nits stay cemented to the hair even once the lice themselves are dead.[2]
Patient education
- Pruritus can genuinely persist for several days to weeks after effective treatment — this on its own does not mean treatment failed.[2] Antihistamines, a topical local anesthetic, or a topical steroid cream can control the itch in the meantime, all available OTC.[2]
- Trimming or shaving the pubic area is a personal choice, not a treatment requirement.[2][3]
- Avoid sexual contact for about 10 days, until persistent infestation has genuinely been ruled out.[2]
- Pubic lice cannot live off a human host for more than 1-2 days, which is reassuring context for a patient anxious about environmental spread via furniture — transmission by sitting on a toilet seat is not possible.[2][3]
- Deliver this counselling in a matter-of-fact, non-judgmental way — pubic lice is an STI diagnosis many patients find embarrassing, and a stigma-free conversation measurably improves both disclosure and follow-through with partner notification.
Special Populations
Pregnancy and breastfeeding
Existing human data support treating pregnant and breastfeeding patients with permethrin or pyrethrin with piperonyl butoxide.[5] Because pregnancy and breastfeeding specifically warrant physician or nurse practitioner consultation before treatment in Canadian guidance, involve the prescriber rather than recommending OTC treatment independently in this population.[2] No teratogenicity or toxicity attributable to ivermectin has been observed in human pregnancy experience, and it is considered probably compatible with breastfeeding, but topical first-line therapy remains preferred where it is a reasonable option.[5] Lindane is specifically contraindicated in pregnancy and breastfeeding and should not be used regardless.[5]
Children
Pubic lice in a child deserves a careful, non-alarmist assessment. Manual transmission from an infested parent's or caregiver's body hair — through close, ordinary physical contact rather than sexual contact — is a genuine and probably the more common explanation, particularly for eyelash involvement.[1] At the same time, because pubic lice is confirmation of a sexually transmitted parasite, its presence in a child should prompt the physician to carefully assess for the possibility of sexual abuse, weighing the whole clinical picture rather than treating either explanation as automatic.[1][3] Involve your jurisdiction's child-protection pathway if the history, examination, or any other finding raises genuine concern, and physically examine and treat infested household or caregiving contacts as part of the same assessment.[1] Standard pediculicides are used the same way as in adults for pubic/body-hair involvement; for eyelash involvement, use the ophthalmic-grade petrolatum protocol rather than a standard pediculicide, and prefer mechanical nit/lice removal where the child can tolerate it.[2] Oral ivermectin should be avoided, or used only under specialist direction, in a child weighing under 15 kg, consistent with its use in the other human lice covered in this library.
HIV infection
Patients with pediculosis pubis and HIV infection should receive the same treatment regimen as patients without HIV.[5] A pubic lice diagnosis is also an opportunity to confirm the patient's HIV testing, care, or prevention needs are being met.
Renal and hepatic impairment
Topical permethrin, pyrethrin/piperonyl butoxide, and malathion require no specific renal or hepatic dose adjustment at standard topical use. Oral ivermectin needs no dosage adjustment for renal impairment, but the safety of repeated dosing in severe hepatic impairment has not been established.[5]
Monitoring & Follow-Up
- Offer a follow-up assessment 9-10 days after treatment, since nits can hatch after 6-8 days; if the patient is unlikely to return for follow-up, consider recommending retreatment at the initial visit instead.[2]
- More generally, re-evaluate at about 1 week if symptoms persist, and retreat with the same or an alternative regimen if live lice are found, or if eggs are seen at the hair-skin junction.[5]
- If no clinical response is seen to an appropriately applied first-line regimen, retreat with an alternative agent rather than repeating the same product.[5]
- Confirm that clothing and bedding decontamination was actually completed, and that sexual partners were notified and treated.[2]
- Confirm STI co-testing was completed and results followed up, and that the patient understands and has acted on any positive finding.[5][2]
- Reassure that residual pruritus for days to weeks after effective treatment is expected and, on its own, is not a sign of treatment failure.[2]
- For eyelash involvement, confirm resolution on follow-up examination, ideally with magnification or a slit lamp if available, given how easily residual lice or nits are missed on routine inspection.[1]
Common Errors to Avoid
- Applying a standard pediculicide to the eyelashes or eyebrows — these agents must never be used near the eyes; use the ophthalmic-grade petrolatum protocol instead.[5][2]
- Using ordinary petroleum jelly (e.g., plain Vaseline) instead of an ophthalmic-grade product for eyelash involvement — it is not recommended for this use and can irritate the eyelid.[2]
- Skipping STI co-testing (HIV, syphilis, chlamydia, gonorrhea) — this is a routine part of managing a confirmed pediculosis pubis diagnosis, not an optional extra.[5][2]
- Treating only the index patient and not notifying or simultaneously treating sexual partners from the relevant look-back window — a common, preventable cause of reinfection.[2][5]
- In a child with eyelash or pubic lice, either automatically assuming sexual abuse or automatically dismissing the possibility — both extremes miss the genuinely balanced clinical assessment this finding calls for.[1]
- Using lindane, given its toxicity, contraindications, and withdrawn marketing authorization in several jurisdictions.[5][3]
- Treating residual itching after an effective course as automatic proof of treatment failure, rather than expected post-treatment irritation.[2]
- Recommending unnecessary fumigation of furniture or living spaces — targeted laundering of recently used clothing and bedding is sufficient.[2][5]
- Missing pubic lice on hair-bearing areas beyond the genital region (thighs, trunk, axillae, facial hair) because the examination stopped at the pubic area alone.[2]
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
First-Line Pediculicides — Genital and Other Coarse Body Hair (Never the Eyelashes)
Apply to cool, dry skin over all affected coarse-hair areas. Neither agent is fully ovicidal; see Choose Initial Treatment for the routine-versus-conditional retreatment discussion.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Permethrin 1% cream | Standard use: Apply to all affected areas, leave 10 minutes, then wash off; retreat per follow-up findings, or routinely at 7-10 days | Local skin irritation; overuse can worsen itching | None significant at standard topical doses | Nits remain cemented to hair after treatment and need manual removal. Never apply near the eyes — see the eyelash-specific protocol below. |
| Pyrethrins + piperonyl butoxide | Standard use: Apply to the affected area, leave 10 minutes, then wash off | Local irritation; rare true allergic reaction, particularly with ragweed sensitivity | None significant at standard topical doses | A pyrethrin-family alternative to permethrin with a similar mechanism and similar resistance concerns. No monograph exists in this database for this product; presented as plain text. |
Alternative Therapy — Treatment Failure or Suspected Resistance
Reported resistance to permethrin and pyrethrin is increasing and widespread; if first-line therapy genuinely fails, switch class rather than repeating the same product.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Malathion 0.5% lotion | Standard use: Apply to affected areas, leave 8-12 hours, then wash off | Odour, skin irritation; flammable product | None significant at standard topical doses | Avoid heat sources (including a hair dryer) during application. Not present in this database; presented as plain text. |
| Ivermectin (oral) | Standard use: 250 mcg/kg PO with food, repeated in 7-14 days | GI upset, dizziness | Increased sedation with other CNS depressants (theoretical) | Not a Health Canada-approved indication for lice; prescriber-directed only. Has only limited ovicidal activity, so retreatment is built in. No dosage adjustment needed in renal impairment; safety of multiple doses in severe hepatic impairment is unknown. The platform's only ivermectin monograph (ROSIVER) is a topical rosacea cream, not this oral antiparasitic formulation, so this row is deliberately presented as plain text rather than linked. |
Eyelash and Eyebrow Involvement (Phthiriasis Palpebrarum)
Standard pediculicides must never be applied to or near the eyes. In a child, weigh the more common explanation of non-sexual transmission from an infested caregiver's body hair against a genuine, carefully assessed possibility of sexual abuse — see Special Populations and Red Flags/Refer.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Ophthalmic-grade petrolatum ointment | Heavier involvement: Apply to eyelid margins twice daily for 10 days, or per product insert | Temporary blurring of vision | None significant with topical ophthalmic use | Use a product specifically formulated and labelled for ophthalmic use (e.g., Lacri-Lube, Duolube) — never plain petroleum jelly (e.g., Vaseline), which can irritate the eyelid. Not present in this database; presented as plain text. |
| Mechanical removal | Light involvement: Manual removal, no medication required | None (procedure, not a drug) | Not applicable | Fine tweezers, a nit comb, or fingernails; sufficient on its own when only a few nits or lice are present. |
Symptomatic Relief
For pruritus or mild skin irritation; itching can genuinely persist for days to weeks after effective treatment and, on its own, is not a sign of treatment failure.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Cetirizine | Adults: 10 mg PO once daily | Mild sedation, dry mouth | Additive sedation with other CNS depressants | Non-sedating option preferred for daytime pruritus. |
| Diphenhydramine | Adults: 25-50 mg PO at bedtime PRN | Sedation, anticholinergic effects | Additive sedation with other CNS depressants | Reserve for itching disrupting sleep. |
| Hydrocortisone (topical) | Adults/children: Apply a thin layer 1-2 times daily, short course | Local skin thinning with prolonged use | None significant with short-term topical use | Short course only, for irritation from scratching or the pediculicide itself; do not apply near the eyes. |
References
- Phthiriasis Palpebrarum — StatPearls, National Library of Medicine. StatPearls [Internet], updated October 6, 2024
- Pediculosis Pubis (Pubic Lice) — Non-Certified Practice Decision Support Tool — BC Centre for Disease Control (BCCDC), Clinical Prevention Services — Reproductive Health. BCCDC Reproductive Health Decision Support Tool — Non-certified Practice, 2023
- European guideline for the management of pediculosis pubis — Journal of the European Academy of Dermatology and Venereology, IUSTI/WHO (Salavastru CM, Chosidow O, Janier M, Tiplica GS). J Eur Acad Dermatol Venereol 2017;31(9):1425-1428
- Pubic lice: an endangered species? — Sexually Transmitted Diseases (Dholakia S, Buckler J, Jeans JP, Pillai A, Eagles N, Dholakia S). Sex Transm Dis 2014;41(6):388-391
- Sexually Transmitted Infections Treatment Guidelines, 2021: Ectoparasitic Infections (Pediculosis Pubis) — Centers for Disease Control and Prevention (Workowski KA, Bachmann LH, Chan PA, et al.). MMWR Recomm Rep 2021;70(No. RR-4):1-187
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.