Ringworm (Tinea Corporis and Tinea Capitis)
Clinical Snapshot
"Ringworm" is a lay term for dermatophyte (tinea) infection, named for the classic annular, ring-shaped lesion of tinea corporis — a smooth-skin infection of the trunk, limbs, or neck, most often caused by Trichophyton rubrum or other Trichophyton species, that expands outward while clearing centrally and responds reliably to topical antifungal therapy alone in the great majority of cases.[1] Tinea capitis, the scalp equivalent, is overwhelmingly a disease of young children and looks superficially related, but differs from tinea corporis in a way that is genuinely decisive for treatment: the dermatophyte invades the hair shaft and follicle itself, not just the surface stratum corneum, so a topical cream — however appropriate it would be for a skin lesion — simply cannot reach the infection.[1] Systemic antifungals should be used to treat tinea capitis because topical agents do not penetrate hair follicles, and this single distinction is the organizing principle of this entire chapter: tinea corporis is genuinely a self-care condition with an appropriately chosen topical agent, while any patient with suspected tinea capitis needs to be recognized and referred for oral prescription therapy, not managed with an OTC cream or shampoo alone.[1] Both conditions also carry a transmission dimension worth building into routine counselling: direct contact with an infected person, contact with an infected household pet (cats and dogs, particularly kittens), and contact with a contaminated shared object — a comb, hairbrush, hat, or pillowcase — can all seed a new infection, and spores can remain viable on such objects for months.[2][3]
Recognize the Condition
Tinea corporis: the classic ring
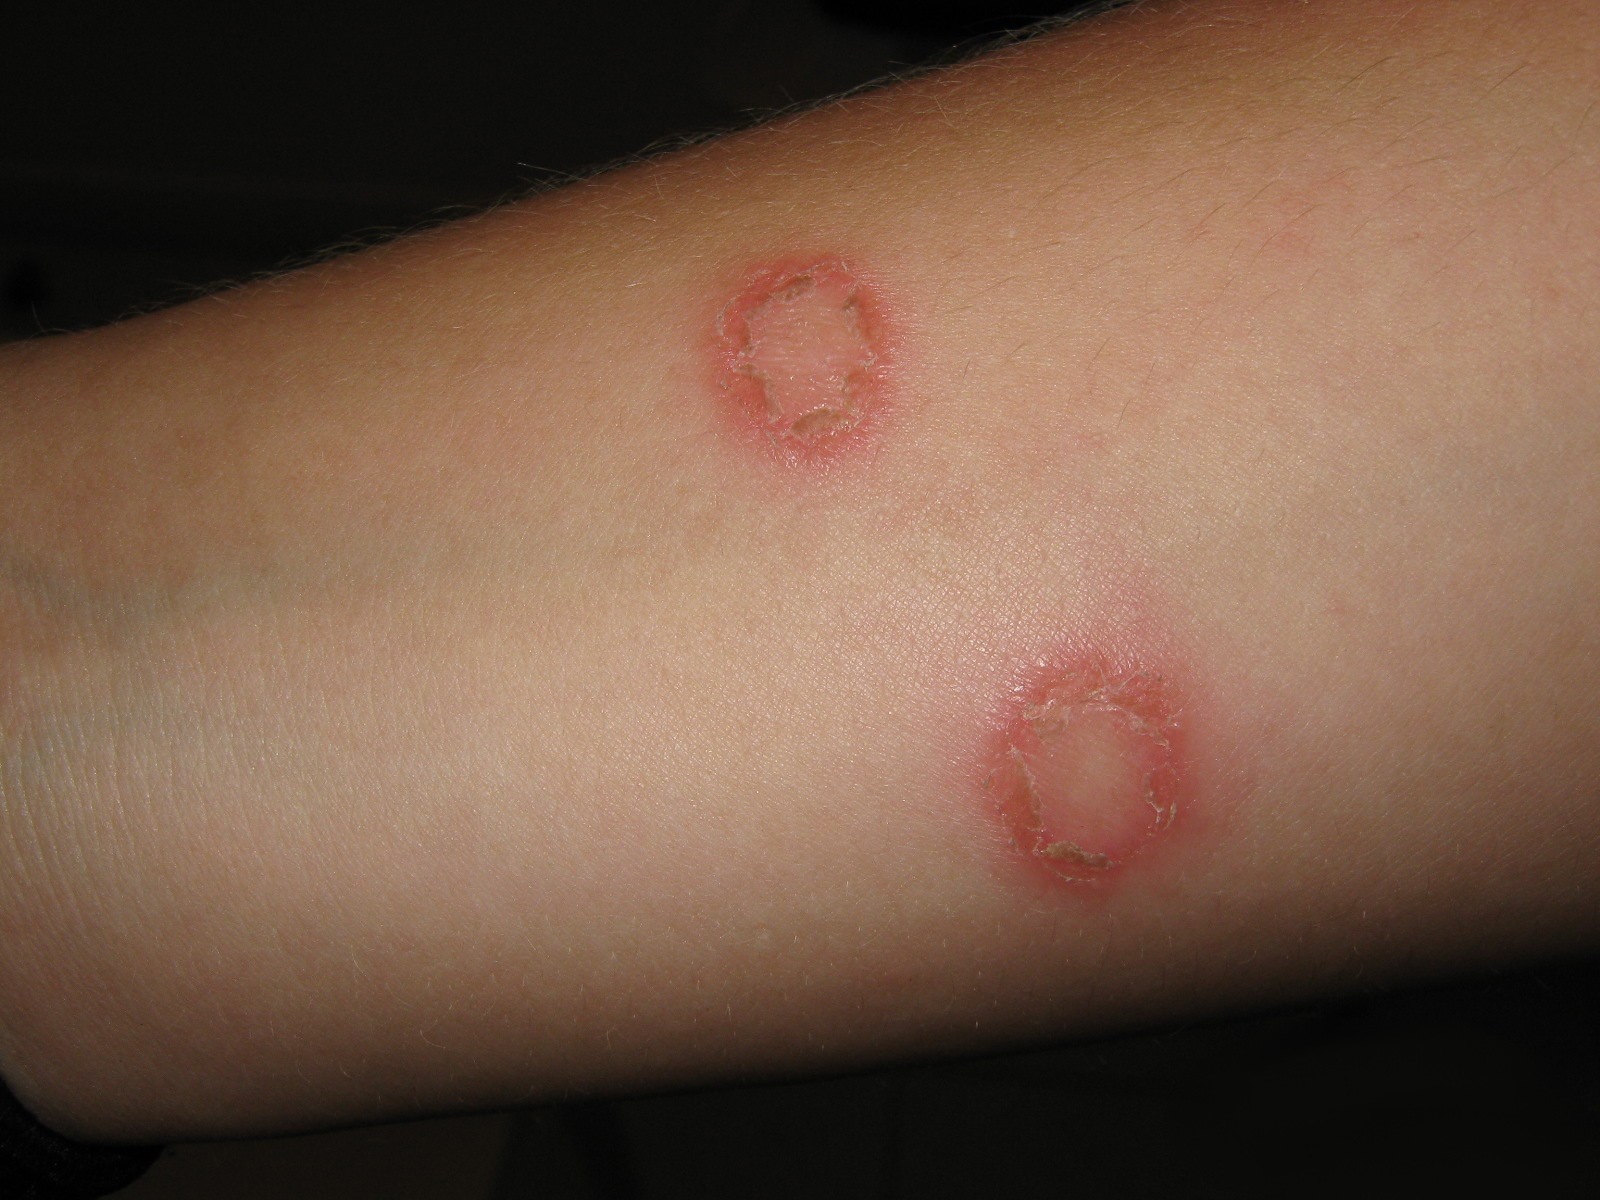
Tinea corporis presents as a red, annular (ring-shaped), scaly, pruritic plaque with an active, raised, scaly border and a zone of central clearing — the lesion expands centrifugally as the fungus advances outward through the stratum corneum, leaving relatively normal-appearing skin behind it in the middle.[1] Lesions are typically 1-5 cm but can be larger, and several lesions can appear at once or merge into a single irregular plaque with multiple advancing edges.[1] A history of pruritus, recent contact with an infected person, pet, or contaminated object, and a well-demarcated advancing border on examination are the key clinical clues.
Tinea capitis: 2 organism-driven presentations in children
Tinea capitis is the most common dermatophyte infection of childhood and presents differently depending on the causative organism and how it invades the hair shaft.[2]
The 2 clinical patterns
"Black dot" pattern — Trichophyton tonsurans (endothrix)
The organism invades inside the hair shaft (endothrix) and the hair breaks off flush with the scalp surface, leaving a stubble of tiny black dots within patches of fine scale and mild alopecia. This is the pattern of T. tonsurans, the predominant organism in North America and an anthropophilic (human-to-human) species that spreads readily through classrooms, daycares, and households, and disproportionately affects children of African heritage, likely reflecting shared hair-care practices and grooming tools.[2][3]
"Grey patch" pattern — Microsporum canis (ectothrix)
The organism coats the outside of the hair shaft (ectothrix) and hairs break a few millimetres above the scalp, producing larger, greyish, scaling patches. M. canis is zoophilic — acquired from an infected cat or dog, especially a kitten — and predominates in Europe and parts of Asia, though it is also seen in North America via pet contact.[2][3]

Beyond hair loss and scale, look specifically for posterior cervical, suboccipital, or postauricular lymphadenopathy — a genuinely useful bedside finding, since tinea capitis (unlike its common mimics, seborrheic dermatitis and psoriasis) frequently produces regional lymph node enlargement.[3]
Kerion: the inflammatory complication
A kerion is a severe, delayed hypersensitivity reaction to the fungal infection presenting as a boggy, tender, fluctuant, often pustular inflammatory mass on the scalp with associated hair loss — it can look alarmingly like a bacterial abscess, but is a fungal-driven immune reaction, not a primary bacterial infection.[3][2] Left untreated, or if incision/drainage and antibiotics are pursued instead of antifungal therapy, a kerion carries a real risk of permanent, scarring alopecia. The Canadian Paediatric Society is explicit that a kerion responds to oral terbinafine and usually does not require antibiotics or surgical drainage — the correct next step is prompt, adequately dosed oral antifungal therapy, not incision and drainage.[2]

Risk Factors
- Household pet ownership, particularly kittens and cats, and stray-cat contact — the classic source of zoophilic Microsporum canis infection.[3]
- Sharing combs, hairbrushes, hats, helmets, headphones, pillowcases, towels, or headrests — fungal spores on these fomites can remain viable for months.[2][3]
- Close-contact activities: wrestling and other skin-to-skin contact sports for tinea corporis; classroom, daycare, and household contact for tinea capitis, which spreads readily among young children.[2]
- Age: tinea capitis is overwhelmingly a disease of preschool and school-age children; it is uncommon, though not absent, in adults — consider it in postmenopausal women and immunosuppressed adults with new scalp scaling or hair loss.
- African heritage and shared hair-care practices/tools (braiding, pomades, communal grooming implements) — a genuine epidemiologic driver of the North American predominance of Trichophyton tonsurans tinea capitis.[2][3]
- Warm, humid climates and occlusive clothing or heavy sweating, which favour tinea corporis on the trunk and limbs.
- A disrupted skin barrier — concurrent atopic dermatitis or minor skin trauma — makes inoculation of tinea corporis easier.
- Immunosuppression, which can produce more extensive or atypical disease at either site.
- An untreated household member, sibling, or classmate with active tinea corporis or tinea capitis.
Red Flags & Refer
Escalate beyond OTC topical self-care for any of the following:
- Any suspected or confirmed tinea capitis, at any severity. This is not a graded referral threshold — topical therapy cannot penetrate the hair follicle, so every patient with scalp involvement needs a prescriber for oral antifungal therapy. The pharmacist's role here is recognition and referral, not attempting topical self-care first.[1]
- Kerion (a boggy, tender, pustular scalp mass) — needs prompt oral antifungal therapy; refer urgently rather than treating as a bacterial abscess.[2][3]
- Suspected Majocchi granuloma — a deeper, follicular dermatophyte infection presenting as firm, follicular papules or nodules on the body, typically arising after shaving over a tinea corporis lesion or after misapplied topical corticosteroid use. Because the infection has moved below the stratum corneum into the follicle, this also requires oral therapy, not a topical cream.
- Extensive tinea corporis covering a large body surface area, or multiple confluent lesions.
- Immunocompromise or diabetes — presentation can be more extensive or atypical, and a lower threshold for oral therapy and prescriber involvement is appropriate.
- Diagnostic uncertainty, or a lesion that has changed appearance after a topical corticosteroid was applied (possible tinea incognito) — confirm the diagnosis with KOH microscopy or culture before treating empirically.
- A single, non-itchy, expanding ring-shaped lesion with a history of possible tick exposure — consider erythema migrans (early Lyme disease) rather than tinea corporis; erythema migrans classically lacks the scaly, raised active border of tinea and will not respond to (and should not be treated empirically with) an antifungal.
- No improvement, or worsening, after a full and adherent topical course for tinea corporis — this needs diagnostic reassessment (mimic, tinea incognito, or Majocchi granuloma), not simply switching topical agents.
Assessment & Diagnosis
History
- Onset, distribution, and whether the lesion is expanding; pruritus; and, for scalp involvement, hair loss, scaling, or a tender/boggy area.
- Exposure history: household pets (especially kittens/cats), stray animal contact, close-contact sports, daycare/school contacts with similar symptoms, and sharing of combs, hats, or pillowcases.[2][3]
- Prior treatment, including any topical corticosteroid applied to the lesion before the correct diagnosis was considered (risk of tinea incognito).
- Immunosuppression or diabetes.
Examination
For tinea corporis, confirm the annular shape with an active, scaly, slightly raised border and central clearing. For suspected tinea capitis, examine for scaling, patchy alopecia, black-dot stubble versus larger grey-patch scaling, a boggy/fluctuant kerion, and regional (posterior cervical, suboccipital, postauricular) lymphadenopathy, which favours tinea capitis over its non-infectious mimics.[3]
Wood's lamp examination
A Wood's lamp (UV-A light) can support the diagnosis of tinea capitis, but its result must be interpreted by organism: hairs infected with Microsporum species fluoresce bright green under Wood's lamp, while Trichophyton tonsurans — the endothrix organism that predominates in North America — does not fluoresce.[3] This is a genuinely important pitfall: a negative Wood's lamp examination does not rule out tinea capitis, since the most common North American organism will not fluoresce regardless of how active the infection is. A positive fluorescence is a useful positive finding; a negative one is not reassuring on its own.
KOH microscopy and culture
Potassium hydroxide (KOH) wet-mount microscopy of a skin scraping taken from the active border (tinea corporis) or of plucked hairs and scale from the affected area (tinea capitis) rapidly confirms hyphae or spores under light microscopy and can be performed at the point of care.[1][3] Fungal culture takes 1-3 weeks to result but is the reference standard for species identification, and the Canadian Paediatric Society specifically recommends it for persistent or recurrent tinea capitis, since the causative species (Trichophyton versus Microsporum) directly changes the expected treatment duration.[2] Because culture is slow, empiric oral therapy for clinically clear tinea capitis should not wait for culture results, but a specimen is worth sending at the outset so species-directed adjustments can be made if the initial response is inadequate.
Differential diagnosis
| Condition | Features that point away from ringworm |
|---|---|
| Nummular eczema | Coin-shaped but lacks a distinctly raised, scaly advancing border and central clearing; often more diffusely distributed and less sharply annular. |
| Granuloma annulare | Annular and can look strikingly similar at a glance, but the border is smooth, firm, and non-scaly — the absence of scale is the key distinguishing feature from tinea. |
| Pityriasis rosea | A single "herald patch" precedes a broader "Christmas-tree" distributed eruption along skin cleavage lines on the trunk; individual lesions have a trailing, not leading, scale. |
| Erythema migrans (early Lyme disease) | A single expanding annular (often "bullseye") lesion following a tick bite, typically non-scaly and non-pruritic, with a smooth rather than raised, scaly active border; ask about tick/outdoor exposure and do not treat empirically with an antifungal. |
| Psoriasis | Well-demarcated, thicker plaques with a silvery scale, usually without central clearing; look for other typical plaques (elbows, knees, scalp) or nail pitting. |
| Contact dermatitis | Distribution matches the contact pattern (jewellery, clothing elastic, plants) rather than a single expanding ring; often more eczematous than sharply annular. |
| Seborrheic dermatitis (scalp) | Greasy yellow scale without hair loss or lymphadenopathy; typically involves the eyebrows, nasolabial folds, or retroauricular skin as well. |
| Alopecia areata | Smooth, completely bald patches without scale, erythema, or broken-hair stubble; look for tapered "exclamation point" hairs at the margin rather than the scale of tinea capitis. |
| Trichotillomania | Irregular patches with hairs broken at varying lengths from repetitive pulling, without scale, erythema, or lymphadenopathy. |
Treatment Targets
- Achieve mycological cure, not just symptomatic improvement.
- Match the treatment route to the site: topical therapy for tinea corporis; oral therapy is mandatory for any tinea capitis, since topical agents cannot penetrate the infected hair follicle.
- For tinea capitis, prevent scarring alopecia, particularly with a kerion, through prompt, adequately dosed oral therapy rather than delay or inappropriate antibacterial/surgical management.
- Reduce household, classroom, and daycare transmission through appropriate antifungal therapy and fomite/pet decontamination.
- Prevent recurrence by identifying and addressing an ongoing reservoir — an infected pet, an untreated household contact, or shared grooming items.
Choose Initial Treatment
Step 1 — confirm the site: this decides everything
Skin only, no scalp/hair involvement proceed with topical self-care below. Any scalp/hair-bearing involvement topical therapy will not work — refer to a prescriber for oral antifungal therapy; do not dispense an OTC antifungal cream or shampoo as sole treatment.[1]
Step 2 — tinea corporis: topical antifungal therapy
1st line the Canadian Paediatric Society reports little difference in efficacy among topical clotrimazole, ketoconazole, miconazole, or terbinafine — apply once or twice daily (per product directions) for 14-21 days, and continue for at least 14 days beyond visible clinical clearing to reduce the risk of relapse.[2] Topical terbinafine, an allylamine, is fungicidal and can achieve cure in as little as 1-2 weeks in some regimens, making it a reasonable preferred first choice for adherence, while the azoles need the fuller 2-4 week course.[1] Broader-spectrum option ciclopirox is a reasonable alternative when secondary bacterial colonization or a possible yeast component is suspected alongside the dermatophyte infection.
Step 3 — tinea capitis: oral therapy is mandatory, dosed and durated by organism
1st line oral terbinafine, weight-based in children (10-20 kg: 62.5 mg/day; 20-40 kg: 125 mg/day; over 40 kg: 250 mg/day; alternatively 4-6 mg/kg/day, max 250 mg/day) or 250 mg once daily in adults.[2][1] Duration is organism-dependent: 4-6 weeks for Trichophyton species (the predominant North American organism, and the reasonable default while culture is pending) versus 8-12 weeks for Microsporum species, which respond more slowly to terbinafine.[2] Historically preferred for Microsporum, limited Canadian availability griseofulvin has excellent efficacy against Microsporum species and the longest-established pediatric safety track record of any oral antifungal for tinea capitis, but it is no longer commercially available in Canada — where genuinely needed, it may still be obtainable through a specialized compounding pharmacy, a real practical limitation worth knowing before assuming it can simply be prescribed.[2] 2nd line oral fluconazole, 6 mg/kg/day (max 400 mg/day) for 3-6 weeks, when first-line terbinafine fails or is not tolerated.[2] Specialist-directed only oral itraconazole (2-5 mg/kg/day in 1-2 divided doses, max 400 mg/day, for 2-3 weeks) has more limited pediatric tinea capitis data and, per the Canadian Paediatric Society, should only be used on an infectious diseases specialist's recommendation.[2]
Step 4 — kerion: treat as tinea capitis, not as an abscess
A kerion responds to oral terbinafine (dosed as above) and usually does not require antibiotics or surgical incision and drainage, despite its dramatic, sometimes fluctuant appearance.[2] Refer promptly for oral antifungal therapy rather than treating it empirically as a bacterial process.
Step 5 — adjunctive antifungal shampoo during oral treatment
Adjunct only, not a stand-alone treatment ketoconazole 2% or selenium sulfide shampoo, applied 2-3 times weekly alongside oral therapy, helps lower the carriage of viable fungal spores on the scalp and reduce transmission risk to household and classroom contacts during the treatment course — but it does not itself cure the infection and should never be used as a substitute for oral therapy.[2]
Non-Pharmacologic Treatment
- Have household pets — particularly kittens and cats — checked and, if infected, treated by a veterinarian when a zoonotic source is suspected or when a household's tinea capitis keeps recurring despite adequate therapy.[3]
- Do not share combs, hairbrushes, hats, helmets, headphones, towels, or pillowcases; disinfect or launder these items in hot water, since fungal spores can remain viable on fomites for months.[2][3]
- For tinea capitis specifically, wash pillowcases, hats, and hair accessories in hot water and consider soaking combs and hairbrushes in a diluted bleach solution during the early treatment period.
- Keep tinea corporis lesions covered during contact sports (wrestling, judo, and similar), and shower promptly after practice or competition to reduce transmission to teammates.
- Screen household members, siblings, and close contacts for similar lesions or scalp scaling, since an unaddressed contact is a common source of reinfection.
- Once appropriate oral antifungal therapy for tinea capitis has begun, most experts do not consider school or daycare exclusion necessary — reinforce ordinary hygiene precautions (no head-to-head contact, no sharing of hats or combs) rather than routine exclusion, unless local public health guidance specifies otherwise.
- Set the expectation explicitly: continue treatment for the full prescribed duration, and for tinea corporis specifically, at least 14 days past the point the skin looks clear — stopping as soon as symptoms improve is a common, avoidable cause of relapse.[2]
Special Populations
Pregnancy
Topical antifungal therapy for tinea corporis is preferred in pregnancy given minimal systemic absorption. Tinea capitis requiring oral therapy in a pregnant patient (most often a caregiver rather than the child, though relevant to counsel about) needs prescriber-directed decision-making: griseofulvin is specifically contraindicated in pregnancy, and oral fluconazole and itraconazole carry teratogenicity signals at systemic-treatment doses — this decision is not one to default to self-care or defer without prescriber input.
Breastfeeding
Topical antifungals are compatible with breastfeeding given minimal systemic absorption. Data on the oral agents in lactation are more limited; the prescribing clinician should weigh the same benefit/risk considerations as in pregnancy.
Pediatrics
Tinea capitis is overwhelmingly a pediatric disease, most common in preschool and school-age children, and disproportionately affects children of African heritage in North America given the predominance of Trichophyton tonsurans and shared hair-care practices.[2] Use weight-based oral terbinafine dosing as above, and remember that most experts do not consider school exclusion necessary once appropriate oral therapy has begun.
Adults
Tinea capitis is uncommon in adults but does occur, particularly in postmenopausal women and immunosuppressed patients, and is frequently misdiagnosed initially as seborrheic dermatitis given the overlapping scalp scaling — a genuine reason to keep tinea capitis on the differential for adult scalp scaling with hair thinning, not just in children.
Immunosuppression
Presentation of either condition can be more extensive or atypical, and warrants a lower threshold for prescriber involvement, culture confirmation, and oral therapy even for what would otherwise be straightforward tinea corporis.
Monitoring & Follow-Up
For tinea corporis, reassess at the end of the planned topical course (14-21 days plus 14 days beyond visible clearing); persistent or worsening lesions warrant reconsidering the diagnosis (mimic, tinea incognito, Majocchi granuloma) rather than simply repeating the same topical agent.[2]
Common Errors to Avoid
- Dispensing or recommending a topical antifungal cream or shampoo as the sole treatment for suspected tinea capitis — topical agents cannot penetrate the hair follicle, and this is the single most consequential error to avoid in this chapter.[1]
- Treating a kerion as a bacterial abscess with antibiotics and/or incision and drainage instead of recognizing it as a fungal-driven inflammatory complication that needs oral antifungal therapy.[2]
- Trusting a negative Wood's lamp examination to rule out tinea capitis — Trichophyton tonsurans, the predominant North American organism, does not fluoresce.[3]
- Applying a topical corticosteroid to an undiagnosed annular lesion, risking tinea incognito and a delayed, more atypical-looking diagnosis.
- Missing erythema migrans by treating a single, non-itchy, non-scaly expanding ring as tinea corporis without asking about tick exposure.
- Assuming griseofulvin is routinely available to prescribe for tinea capitis in Canada without confirming access, given it is no longer commercially available outside compounding pharmacies.[2]
- Recommending an antifungal shampoo alone for tinea capitis, or presenting it as equivalent to oral therapy rather than as an adjunct that reduces spore shedding.[2]
- Not asking about household pets, shared grooming items, or symptomatic contacts, leaving an ongoing transmission or reinfection source unaddressed.
- Unnecessarily excluding a child from school or daycare once appropriate oral therapy has begun, rather than reinforcing simple hygiene precautions.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Allylamines (topical and oral)
First-line class at both sites: fungicidal, generally shorter courses, and — for oral use — fewer clinically significant drug interactions than the oral azoles.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Terbinafine, topical 1% cream | Tinea corporis: Apply once or twice daily for 14-21 days, continued 14 days beyond clearing | Local irritation, burning, stinging, dryness | None clinically significant given minimal systemic absorption | 1st-line topical agent for tinea corporis. Continue at least 14 days beyond visible clearing. Not adequate treatment for tinea capitis — cannot penetrate the hair follicle. |
| Terbinafine, oral | Adults: 250 mg PO once daily; 4-6 weeks (Trichophyton species) or 8-12 weeks (Microsporum species) Children 10 to under 20 kg: 62.5 mg PO once daily Children 20-40 kg: 125 mg PO once daily Children over 40 kg: 250 mg PO once daily Alternative weight-based dosing: 4-6 mg/kg/day (max 250 mg/day) | GI upset, headache, transient taste/smell disturbance, rash; rare hepatotoxicity, blood dyscrasias | Inhibits CYP2D6, raising levels of tricyclic antidepressants, SSRIs (fluoxetine, paroxetine), tramadol, atomoxetine, and CYP2D6-metabolized beta-blockers; cimetidine decreases and rifampin increases terbinafine clearance | 1st-line oral agent for tinea capitis — mandatory, since the infection is intrafollicular. Obtain baseline liver enzymes; monitor periodically if the course exceeds 4-6 weeks. |
Azoles (topical)
CPS reports little difference in efficacy among the topical azoles and topical terbinafine for tinea corporis; choice can reasonably be guided by cost, availability, or patient preference.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Clotrimazole, topical 1% cream | Dosing: Apply once or twice daily for 14-21 days | Local irritation, burning, contact dermatitis (uncommon) | None clinically significant given minimal systemic absorption | Apply once or twice daily for 14-21 days, continued 14 days beyond visible clearing. |
| Ketoconazole, topical 2% cream | Dosing: Apply once daily for 14-21 days | Local irritation, burning | None clinically significant given minimal systemic absorption | Apply once daily for 14-21 days, continued 14 days beyond visible clearing. |
| Miconazole, topical 2% cream | Dosing: Apply once or twice daily for 14-21 days | Local irritation, burning | None clinically significant given minimal systemic absorption | Comparable efficacy and dosing rationale to clotrimazole and ketoconazole for tinea corporis. |
Azoles (oral)
Reserved for tinea capitis when first-line terbinafine fails, is not tolerated, or (for itraconazole) on specialist direction — not first-choice agents.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Fluconazole, oral | Dosing: 6 mg/kg/day (max 400 mg/day) for 3-6 weeks | Nausea, headache; rare hepatotoxic reactions | Inhibits CYP2C9/CYP2C19/CYP3A4 — raises levels of warfarin, phenytoin, sulfonylureas, and other substrates; monitor for toxicity | 2nd-line oral agent for tinea capitis per CPS, used when terbinafine fails or is not tolerated. Monitor hepatic enzymes if therapy is prolonged. |
| Itraconazole, oral | Dosing: 2-5 mg/kg/day in 1-2 divided doses (max 400 mg/day) for 2-3 weeks | GI upset, headache; rare hepatotoxicity, heart failure | Potent CYP3A4 inhibitor — avoid or use with caution with statins metabolized via CYP3A4, calcium channel blockers, digoxin, warfarin, and other CYP3A4 substrates; H2-antagonists and proton pump inhibitors reduce absorption | CPS: use only on an infectious diseases specialist's recommendation — pediatric tinea capitis data are more limited than for terbinafine. |
Griseofulvin (oral)
Historically the gold-standard oral agent for tinea capitis, with the longest-established pediatric track record and particular strength against Microsporum species — but note the Canadian availability issue below before assuming it can be prescribed.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Griseofulvin, oral | Adults (where available): Approximately 500-1,000 mg PO daily for 6-12 weeks Canadian availability: Not commercially available — compounding pharmacy access only | Photosensitivity, GI upset, headache, hepatic dysfunction; contraindicated in pregnancy | Induces hepatic CYP enzymes — reduces efficacy of warfarin and hormonal contraceptives | No longer commercially available in Canada; may still be accessible through a specialized compounding pharmacy where genuinely needed. Where available, historical dosing is weight-based in children and roughly 500-1,000 mg/day in adults, for 6-12 weeks depending on species and response — especially preferred historically for Microsporum species. |
Adjunctive antifungal shampoos
Reduce fungal spore shedding and household/school transmission during tinea capitis treatment. These are adjuncts only and are never a substitute for oral antifungal therapy.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Ketoconazole 2% shampoo | Dosing: Apply 2-3 times weekly, in conjunction with oral therapy | Scalp irritation, dryness | None clinically significant given minimal systemic absorption | Use alongside oral therapy for tinea capitis to lower carriage of viable fungal spores. |
| Selenium sulfide shampoo | Dosing: Apply 2-3 times weekly, in conjunction with oral therapy | Scalp irritation, dryness; discoloration of light-colored hair | None clinically significant given minimal systemic absorption | Alternative adjunct shampoo with the same role as ketoconazole shampoo — reduces spore shedding, does not cure the infection alone. |
Hydroxypyridones (topical)
Broader-spectrum topical option for tinea corporis when secondary bacterial or candidal colonization is also suspected.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Ciclopirox, topical 0.77% cream | Dosing: Apply twice daily for 14-21 days, continued 14 days beyond visible clearing | Local irritation | None clinically significant given minimal systemic absorption | Combined antifungal, anticandidal, and antibacterial activity — a reasonable alternative for tinea corporis with a macerated or colonized presentation. |
References
- Diagnosis and Management of Tinea Infections — American Family Physician (Caplan AS, Gold JAW, Smith DJ, Ely JW). Am Fam Physician 2025;112(4):382-392
- Antifungal agents for common outpatient paediatric infections — Canadian Paediatric Society, Infectious Diseases and Immunization Committee (Audcent T, Barton M, Top K; originally Bortolussi R, Martin S). CPS Position Statement, posted June 20, 2019, reaffirmed November 21, 2024
- Tinea capitis — DermNet (Oakley A, Bell H). DermNet, updated September 2020
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.