Rosacea
Clinical Snapshot
Rosacea is a chronic, relapsing inflammatory disorder of the central face. It typically begins with recurrent, transient flushing and persistent centrofacial erythema, and can progress — though not inevitably — to visible telangiectasia (dilated blood vessels), inflammatory papules and pustules, and, in a minority of patients, irreversible thickening and glandular overgrowth of the skin (phymatous change), most often affecting the nose.[1] Its pathophysiology is not fully elucidated but is thought to involve a combination of genetic predisposition, neurovascular dysregulation, and an overactive innate immune response, with ultraviolet exposure and Demodex folliculorum mite density proposed as contributors to this inflammatory cascade.[1] More than half of patients with cutaneous rosacea also have some degree of ocular involvement — irritation, dryness, blepharitis — which can precede the skin findings entirely and is frequently under-recognized unless specifically asked about. Current management is organized around the specific features (phenotype) a patient has, rather than around older subtype labels, since treatment genuinely differs by phenotype and a single patient commonly has more than one at once.[2]
Recognize the Condition
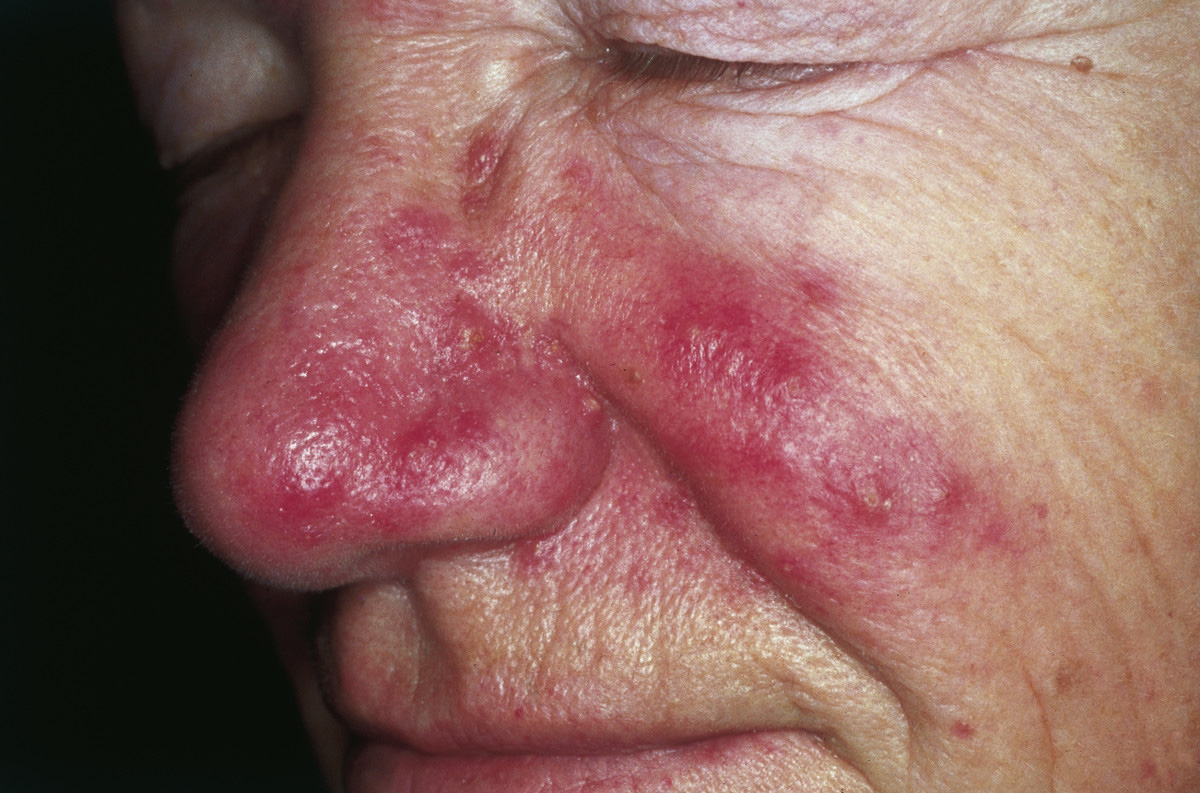
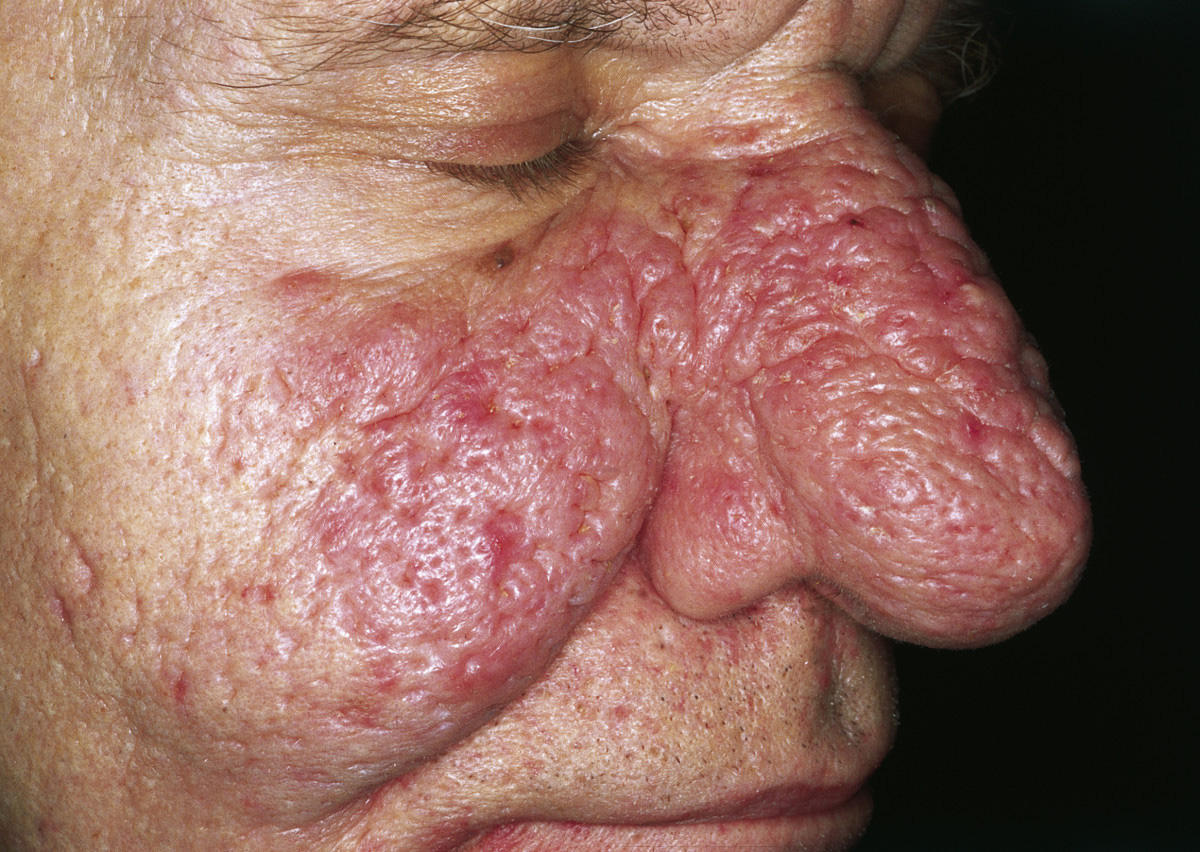

Diagnostic approach (2017 National Rosacea Society classification)
Rosacea is diagnosed clinically using a phenotype-based approach rather than a fixed checklist.[1][3]
| Category | Features |
|---|---|
| Diagnostic features (either one alone is diagnostic) | Persistent centrofacial erythema (forehead, nose, cheeks, chin) that periodically intensifies with triggers; and/or phymatous change (widened or spreading follicles, skin thickening/fibrosis, glandular hyperplasia, bulbous appearance of the nose). |
| Major features (2 or more support the diagnosis) | Flushing; inflammatory papules and pustules; telangiectasia; ocular manifestations strongly suggestive of rosacea (lid margin telangiectasia, interpalpebral conjunctival injection, corneal spade-shaped infiltrates, scleritis or sclerokeratitis). |
| Secondary (minor) features (may accompany diagnostic or major features) | Burning sensation; stinging sensation; edema; dryness; ocular findings not specific to rosacea ("honey crust"/collarette at the base of the lashes, irregular lid margin, rapid tear breakup time). |
In darkly pigmented skin, erythema, flushing, and telangiectasia often do not appear as redness and can instead look dusky to dark brown, grey, or light to dark purple — or may not be easily visualized at all. This contributes to real underdiagnosis and delayed treatment; ask specifically about warmth, flushing sensation, and burning/stinging even when redness itself is not obvious on inspection.
The 4 rosacea phenotypes
Treatment differs meaningfully by phenotype, and a single patient often has more than one at once.
Erythematotelangiectatic
Persistent centrofacial redness with periodic flushing and visible telangiectasia, without inflammatory papules or pustules.
Papulopustular
Inflammatory papules and pustules superimposed on a background of centrofacial erythema, with no comedones — a key feature distinguishing it from acne vulgaris.
Phymatous
Thickened, bumpy, enlarged skin from sebaceous gland hyperplasia and fibrosis, most often affecting the nose (rhinophyma) but also possible on the chin, forehead, ears, or cheeks. More common in men and develops over years.
Ocular
Eyelid margin telangiectasia, conjunctival injection, blepharitis, dry eye, and recurrent styes; severe cases can involve the cornea. Can precede visible skin findings and is frequently under-recognized unless specifically asked about.
Risk Factors
- Family history of rosacea.
- Lightly pigmented skin — though rosacea occurs in all skin tones and is likely underdiagnosed in darkly pigmented skin because the visual findings differ (see Recognize the Condition).
- Onset typically in the late 20s to 40s — later than the usual onset of acne vulgaris, a useful clue when the two are hard to distinguish.
- Similar prevalence between sexes overall, though phymatous change is more common in men.
- A personal history of frequent flushing or sun sensitivity.
- Comorbid conditions with growing evidence of association — migraine, inflammatory bowel disease, depression, and cardiovascular disease — suggesting rosacea may be a marker for, not just a consequence of, a broader inflammatory process.
Red Flags & Refer
Most rosacea is managed safely in primary care and community pharmacy, but escalate for any of the following:
- Vision changes, significant eye pain, photophobia, or a red eye that does not improve with lid hygiene — refer urgently to ophthalmology; corneal involvement in ocular rosacea can threaten vision if untreated.
- Rapidly progressive or severe rhinophyma causing nasal obstruction or airway compromise — refer urgently for surgical/laser assessment.
- An asymmetric, ulcerated, bleeding, or rapidly changing lesion on a phymatous nose — biopsy to exclude a skin cancer arising on or mimicking rhinophyma, rather than assuming it is simply rosacea progression.
- Features suggesting a different diagnosis rather than rosacea itself — a malar rash that spares the nasolabial folds, photosensitivity with a clear temporal relationship to sun exposure or a new medication, comedones (suggesting acne vulgaris instead), or a perioral distribution that spares a rim around the lips (suggesting perioral dermatitis) — see the comparison table in Assessment & Diagnosis and reconsider the diagnosis before starting rosacea-specific treatment.
- Systemic symptoms accompanying facial redness — joint pain, oral ulcers, photosensitivity, or unexplained fatigue — consider systemic or discoid lupus erythematosus and refer for further workup rather than treating as rosacea alone.
Assessment & Diagnosis
Differentiating rosacea from its common mimics
Rosacea is diagnosed clinically, and its most important mimics are managed completely differently — some (a steroid-induced rosacea-like eruption) actually get worse with the instinctive reflex reach for a topical corticosteroid, and others (discoid lupus erythematosus) need a systemic workup, not a skin cream.


| Feature | Rosacea | Acne vulgaris | Perioral dermatitis | Seborrheic dermatitis | Steroid-induced rosacea-like eruption | Discoid lupus erythematosus | Photosensitivity reaction |
|---|---|---|---|---|---|---|---|
| Distribution | Centrofacial: forehead, nose, cheeks, chin | Face, and often chest/back/shoulders; follicular | Perioral/periorificial, classically sparing a clear rim right around the vermilion border; may involve perinasal or periocular skin | Nasolabial folds, eyebrows, scalp margin, and other greasy/scaly areas | Exactly the area where a topical corticosteroid was applied to the face | Disc-shaped plaques on the face, scalp, or ears; can extend beyond the centrofacial area | All sun-exposed skin — face, V of the neck, forearms/hands — not limited to the centrofacial area |
| Comedones | Absent | Present — the key differentiator | Absent | Absent | Absent | Absent (follicular plugging can mimic but true comedones are absent) | Absent |
| Scale | Minimal, except within phyma | None typically | Fine scale sometimes present | Greasy, yellow, prominent scale | Variable; skin atrophy and prominent telangiectasia often present | Adherent scale that can extend into follicles ("carpet-tack" sign); heals with scarring and pigment change | Can include vesicles or an eczematous change in more severe reactions |
| Telangiectasia | Prominent, especially in the erythematotelangiectatic phenotype | Absent | Usually absent | Absent | Often present, from corticosteroid-induced atrophy | Can occur within plaques but is not the dominant feature | Not a typical feature |
| Key history clue | Flares with known triggers (sun, heat, alcohol, spicy food, hot beverages, emotional stress) | Onset in the teens/twenties, comedogenic products, hormonal pattern | Recent topical corticosteroid use, or heavy moisturizer/cosmetic use, on the perioral area | Worse in cold, dry weather; associated dandruff | History of topical corticosteroid use on the face — worsens (rebounds) on stopping, which can be mistaken for treatment failure | Photosensitivity, other systemic lupus features (joint pain, oral ulcers, fatigue), scarring alopecia if the scalp is involved | A new medication or product plus recent sun exposure; more acute onset than rosacea |
| Distinguishing pearl | No comedones, centrofacial distribution, trigger-related flushing | Comedones are the single most reliable differentiator from rosacea | Sparing of the rim around the lips is the classic clue | Greasy scale plus a nasolabial/eyebrow/scalp distribution | The corticosteroid history is the single most important clue — stop the steroid, do not add more, and expect a rebound flare before improvement | Scarring and dyspigmentation on resolution; biopsy and ANA testing if uncertain | Extends to all sun-exposed skin, not just the centrofacial area; resolves with photoprotection and removing the trigger |
History
- Onset age and pattern — rosacea typically starts in the late 20s to 40s, later than the usual onset of acne vulgaris.
- Ask specifically about flushing triggers (sun, heat, wind, exercise, hot beverages, spicy food/vinegar, alcohol, emotional stress, astringent skincare products) and about medications that can worsen rosacea (see Non-Pharmacologic Treatment).
- Ask specifically about eye symptoms — irritation, grittiness, dryness, recurrent styes, or blepharitis — since ocular involvement can precede skin findings and is easy to miss if not asked about directly.
- Ask about any topical corticosteroid use on the face, prescribed or over-the-counter, which can both cause a rosacea-like eruption and worsen true rosacea.
- Family history of rosacea.
Examination
- Inspect the pattern and distribution of erythema, remembering that redness may appear dusky, brown, grey, or purple rather than red in darkly pigmented skin.
- Look specifically for the absence of comedones — their presence points away from rosacea and toward acne vulgaris (combined rosacea plus acne does occur).
- Examine the nose, chin, forehead, ears, and cheeks for early phymatous change (thickened, bumpy texture) even before frank rhinophyma is obvious.
- Examine the eyelid margins and conjunctiva for telangiectasia, injection, or blepharitis in every patient with cutaneous rosacea, not only those who report eye symptoms.
Investigations
Rosacea is a clinical diagnosis — no laboratory test or biopsy is routinely needed.[4] Consider a skin biopsy or referral for further workup specifically when the presentation is atypical or a mimic is suspected: an asymmetric or ulcerated phymatous lesion (exclude skin cancer), a photosensitive or scarring eruption with systemic symptoms (exclude discoid or systemic lupus erythematosus), or a presentation that does not respond as expected to standard rosacea therapy.
Treatment Targets
- Build the patient's awareness of their individual triggers and how to avoid or minimize them.
- Build the patient's awareness of ocular rosacea signs and symptoms and how to manage them.
- Reduce erythema, flushing, telangiectasia, and inflammatory papules/pustules.
- Improve the visible appearance of the skin, particularly where it is affecting the patient's quality of life.
- Reduce the frequency and severity of cutaneous and ocular flares over time.
- Slow or prevent progression to phymatous change where possible, and refer early when phymatous change is already present.
Choose Initial Treatment
Persistent erythema and telangiectasia
1st line, persistent erythema topical brimonidine 0.33% gel once daily[5] — counsel on the rebound-erythema risk before starting (see Non-Pharmacologic and Pharmacologic Treatment Options).
Telangiectasia itself, or erythema not adequately controlled with brimonidine refer for vascular laser or intense pulsed light (IPL) treatment — brimonidine has no effect on visible dilated vessels themselves.
Inflammatory papules and pustules
1st line, mild-moderate disease a topical agent — metronidazole, azelaic acid, or ivermectin — chosen on tolerability and patient preference; all three have comparable 1st-line evidence.[2][6]
Inadequate response to the first topical after an adequate trial (4-8 weeks minimum) switch to a different topical agent, or combine two topical agents.
Moderate-severe disease, or inadequate response to topical therapy alone add an oral agent — anti-inflammatory (subantimicrobial) dose doxycycline 40 mg modified-release once daily is preferred; standard-dose doxycycline 100 mg daily is an alternative, particularly when ocular rosacea is also present, since the modified-release product has not been studied in that population.[5]
Treatment-resistant papules/pustules despite an adequate combined topical-plus-oral trial low-dose oral isotretinoin, prescribed and monitored as detailed in the Acne Vulgaris chapter (pregnancy prevention program, baseline and periodic laboratory monitoring).
Phymatous change
Early, inflamed phyma oral doxycycline or tetracycline at standard anti-inflammatory dosing, based on anecdotal evidence of benefit.
Mild-moderate phyma, to slow progression a topical retinoid or low-dose oral isotretinoin may be considered, though evidence for this specific use is limited.[7]
Established, noninflamed phymatous change refer for laser resurfacing or electrosurgery — physical debulking is the only way to reverse established phymatous tissue change.
Ocular rosacea
Mild ocular involvement eyelid hygiene and artificial tears are 1st line and often sufficient.
Moderate-severe ocular involvement, or inadequate response to lid hygiene add oral doxycycline or tetracycline at standard anti-inflammatory dosing; discontinue once symptoms subside and continue lid hygiene/artificial tears as maintenance.
Persistent or severe ocular involvement refer to ophthalmology — topical cyclosporine ophthalmic emulsion can then be considered under specialist care.
Non-Pharmacologic Treatment
Trigger identification and avoidance
Ask every patient about their personal triggers and counsel on avoidance — this is one of the highest-yield, lowest-risk interventions in rosacea and should be addressed at every visit, not just at diagnosis.[5]
Environmental/lifestyle triggers
- Sunlight (the most consistently reported trigger)
- Heat, wind, and intense cold
- Exercise
- Hot beverages
- Spicy foods and vinegar
- Alcohol
- Emotional stress
- Astringent, alcohol- or acetone-based skincare products
Medications that can trigger or worsen rosacea
- Vasodilators — calcium channel blockers, niacin (nicotinic acid), nitrates, phosphodiesterase-5 inhibitors (e.g., sildenafil)
- Topical corticosteroids, unless low-potency or used only briefly
- Medications that cause dry eyes (e.g., anticholinergics) can specifically aggravate ocular rosacea
Sun protection and general skin care
- Daily broad-spectrum sunscreen, SPF 30 or higher, is one of the most important interventions in rosacea — reinforce this at every visit.
- Use gentle, fragrance-free, non-soap cleansers and moisturizers; avoid astringents and other skincare products that sting or burn on application.
- Avoid topical corticosteroids on the face — they can precipitate or worsen rosacea by adding to the underlying dermal changes, even when used for an unrelated concern.
- Camouflage makeup can help patients whose appearance is affecting their quality of life — green- or yellow-tinted foundation is particularly effective at masking redness in lightly pigmented skin; patients with darkly pigmented skin may benefit from professional cosmetic colour-matching support.
Eyelid hygiene for ocular rosacea
- Gently wash the lids and lashes twice daily with warm water and either a diluted baby shampoo or a commercial lid-care product — apply to a wet washcloth or cotton swab, gently scrub the lid margins and lash base, then rinse with warm water. There is no single consensus technique; some sources recommend a hand-soap-like lather, others undiluted shampoo — either approach is reasonable.
- Use preservative-free artificial tears as needed for dryness.
- Long-chain omega-3 fatty acid supplementation may have a role in dry eye disease including ocular rosacea, though the supporting evidence is inconsistent.
- Evidence for tea tree oil in Demodex-associated blepharitis is limited and uncertain — it is a reasonable adjunct to discuss but should not replace standard lid hygiene.
Laser and light-based procedures
Vascular laser systems and broadband light/intense pulsed light (IPL) devices can significantly improve persistent erythema and telangiectasia after a small number of treatments by selectively targeting the blood vessels causing the redness.[7] Laser resurfacing and electrosurgery are the definitive options for established, noninflamed phymatous change. All of these are non-pharmacologic, procedure-based options performed by a trained practitioner — pharmacists should know they exist and refer appropriately, but they are not initiated in pharmacy practice. Use caution — and refer to a practitioner experienced with darkly pigmented skin — for any of these procedures in patients with darker skin tones, since hyper- or hypopigmentation, and a higher risk of post-procedure dyschromia and scarring, can occur at higher treatment fluences.
Counsel patients starting brimonidine (or completing a course of laser treatment) that visible blood vessels can appear more prominent once the surrounding redness is reduced — this is the redness that was previously masking the vessels becoming less visible, not the treatment creating or worsening telangiectasia.
Special Populations
Breastfeeding
Azelaic acid and topical metronidazole are both considered compatible with breastfeeding given limited absorption/low milk transfer — avoid direct infant skin contact with treated areas. Topical brimonidine has no human lactation data but low systemic levels are expected with the cutaneous route; case reports of the related ophthalmic product show no harm to nursing infants. Topical ivermectin has not been studied in breastfeeding but low milk levels are expected given low systemic absorption. Doxycycline, minocycline, and tetracycline transfer into breast milk in low concentrations — short-term use is generally considered compatible with breastfeeding, but prolonged or repeated courses (as often needed in rosacea) should be avoided as a theoretical precaution. Oral isotretinoin is not recommended during breastfeeding — safety has not been documented. Topical cyclosporine ophthalmic emulsion: use with caution — systemic levels after topical ophthalmic use are undetectable, but human lactation data specific to this route are lacking.
Pediatrics
Rosacea is uncommon in children. Azelaic acid, ivermectin, and topical brimonidine have not had safety/effectiveness established under 18, and topical brimonidine is specifically contraindicated under 2 years and not recommended between 2 and 18. Doxycycline, minocycline, and tetracycline are contraindicated up to age 8 because of permanent tooth discolouration and decreased bone growth — pediatric oral therapy is specialist-directed. Oral isotretinoin follows the same age policy detailed in the Acne Vulgaris chapter. Topical cyclosporine ophthalmic emulsion has no authorized pediatric indication.
Renal/hepatic impairment
Doxycycline (either dose) should be used with caution in hepatic impairment or with other hepatotoxic medications; the modified-release product is not recommended after gastrectomy, gastric bypass, or other surgery affecting the duodenum, since its release depends on normal gastric acidity. Isotretinoin needs hepatic and lipid monitoring as detailed in the Acne Vulgaris chapter. Topical agents (azelaic acid, ivermectin, topical metronidazole, topical brimonidine) and topical cyclosporine have minimal systemic absorption and generally need no renal/hepatic dose adjustment.
Older adults
No specific dose adjustment is needed for the topical agents; trials of topical brimonidine, topical metronidazole, and ophthalmic cyclosporine specifically found comparable safety/effectiveness in patients over 65. Watch for drug interactions with oral doxycycline in patients on warfarin (potentiated anticoagulant effect) or a sulfonylurea (potentiated hypoglycemic effect), both more likely to be relevant in an older, more polypharmacy-exposed population.
Monitoring & Follow-Up
Reassess topical therapy for papulopustular disease no sooner than 4-8 weeks — topical metronidazole in particular can take up to 3-9 weeks to show its full effect, and judging it a failure earlier risks an unnecessary switch or escalation.[5] Reassess an oral antibiotic course at about 12 weeks (3 months); many patients can then taper or stop the oral agent while continuing topical maintenance. Because rosacea is a chronic, relapsing disease, relapse after stopping any effective therapy — topical or oral — is expected rather than a sign the wrong drug was chosen; long-term topical maintenance is often needed indefinitely. Specifically monitor for rebound erythema in the first 1-2 weeks of topical brimonidine, and reassess whether to continue, stop, or attempt a cautious retrial with a smaller test area. Ask about ocular symptoms at every follow-up visit for cutaneous rosacea, even when they are not the presenting complaint. For phymatous change, monitor for progression and refer for laser/surgical options before disfigurement or functional (airway) impairment becomes severe. Isotretinoin monitoring (pregnancy testing where applicable, liver enzymes, lipids) follows the schedule detailed in the Acne Vulgaris chapter.
Common Errors to Avoid
- Prescribing or continuing a topical corticosteroid on rosacea-affected facial skin — this worsens rosacea and can itself cause a steroid-induced rosacea-like eruption.
- Judging a topical agent a failure before an adequate trial — topical metronidazole and azelaic acid can take several weeks to show their full effect.
- Not asking about ocular symptoms in a patient with cutaneous rosacea — ocular involvement is common and easy to miss unless specifically asked about.
- Starting brimonidine without counselling on rebound erythema — an unwarned patient may believe the medication has made their redness worse when a brief, expected phenomenon is at play, or may fail to recognize a genuine reaction requiring discontinuation.
- Confusing anti-inflammatory (subantimicrobial) dose doxycycline with standard antimicrobial-dose doxycycline — the modified-release, subantimicrobial-dose product must not be used to treat or prevent infections, and only the standard-dose product has supporting evidence for ocular rosacea.
- Combining doxycycline (either dose) with an oral retinoid (isotretinoin) — increased risk of pseudotumor cerebri (benign intracranial hypertension).
- Assuming a papulopustular presentation is acne vulgaris (or vice versa) without checking for comedones — their absence in rosacea and presence in acne is the single most reliable differentiator.
- Missing a rosacea mimic that needs entirely different management — most importantly, a genuine steroid-induced rosacea-like eruption, which needs the corticosteroid stopped, not a stronger rosacea regimen added.
- Assuming oxymetazoline cream is readily available in Canada the way it is in the United States — confirm local product availability before recommending it (see Drug Tables).
- Forgetting sun protection counselling — one of the highest-yield, lowest-risk interventions in rosacea management.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation, including renal/hepatic adjustment. Select any drug name to open its complete Pharmasist Drug Database page.
Topical agents for inflammatory papules and pustules
All three are considered comparable 1st-line options; selection is based on tolerability and patient preference.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Azelaic acid | Adults: 15% gel applied twice daily | Burning, stinging, pruritus, scaling, dryness -- usually mild and transient, most pronounced early in treatment | None established for the topical route | 1st-line agent; can be used for initial therapy or long-term maintenance. Applying moisturizer before or after application may lessen irritation. Relapse can occur if discontinued. |
| Ivermectin | Adults: 1% cream applied once daily | Dry skin, pruritus, skin-burning sensation | None established for the topical route | 1st-line agent; thought to act via an anti-Demodex and immunomodulatory effect. Once-daily dosing may aid adherence. Beneficial effects may continue after stopping. |
| Metronidazole (topical) | 1% strength: Applied once daily 0.75% strength: Applied twice daily, morning and evening | Local irritation, dryness, redness, burning; occasional conjunctivitis with facial application | None established given minimal systemic absorption | 1st-line agent. Significant improvement is usually seen within 3 weeks, continuing through 9 weeks. Relapse can occur if discontinued. Not the same product as oral or intravaginal metronidazole. |
Topical agents for persistent erythema
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Brimonidine (topical) | Adults: 0.33% gel, pea-sized amount to each of 5 facial zones (forehead, chin, nose, each cheek), once daily; start with less than the maximum for at least 1 week and titrate up as tolerated | Erythema, flushing, skin-burning sensation, contact dermatitis, headache; rebound (aggravated) erythema in a meaningful proportion of patients, usually within the first 2 weeks | Caution with CNS depressants, MAO inhibitors, other agents affecting circulating amines, and other antihypertensive/alpha-adrenergic agents, given systemic absorption potential | Onset about 30 minutes, peak effect about 3 hours; effect wears off over the day. Counsel specifically on the rebound-erythema phenomenon before starting. Has no effect on visible telangiectatic vessels themselves. |
| Oxymetazoline | US-approved dosing: 1% cream, pea-sized amount applied once daily to the entire face (forehead, nose, each cheek, chin), avoiding the eyes and lips | Application-site dermatitis, pruritus, worsening erythema, pain | None established for the topical route | An alpha-1A adrenergic agonist with a similar rationale to brimonidine (vasoconstriction of dilated dermal vessels). Approved and marketed in the United States but not currently available as an authorized product in Canada -- confirm local availability before recommending it. |
Oral antibiotics
Used chiefly for their anti-inflammatory rather than antimicrobial effect in rosacea.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Doxycycline (modified-release, anti-inflammatory dose) | Adults: 40 mg PO once daily, morning, on an empty stomach, for up to 16 weeks | Diarrhea, headache, upper abdominal pain, fungal infection, nausea, elevated liver enzymes | Reduced absorption with antacids/mineral supplements; avoid with oral retinoids (pseudotumor cerebri risk); can potentiate warfarin and sulfonylureas | 1st-line oral agent for moderate-severe papulopustular disease. Delivers a subantimicrobial plasma level -- must not be used to treat or prevent infections, and has not been studied in ocular rosacea (use standard-dose doxycycline instead in that population). No meaningful effect on erythema. |
| Doxycycline (standard-dose) | Adults: 100 mg PO once daily for about 12 weeks, then reassess | GI upset, photosensitivity, yeast overgrowth; rare azotemia, pseudotumor cerebri; contraindicated in pregnancy | Reduced absorption with antacids/mineral supplements; avoid with oral retinoids | Alternative oral agent, and preferred over the modified-release product specifically when ocular rosacea is present, since standard-dose doxycycline has supporting evidence there. No food restriction required. |
| Minocycline | Adults: 50-100 mg PO once daily for 6-8 weeks | GI upset, photosensitivity, yeast overgrowth, dizziness/vertigo, abnormal skin pigmentation, rare drug-induced lupus-like syndrome, rare hepatic dysfunction | Absorption reduced by oral iron and aluminum-/calcium-/magnesium-containing antacids | Reserve for when tetracycline/doxycycline has failed after an adequate trial with good adherence -- minocycline carries rarer but more serious risks than doxycycline or tetracycline. No food restriction required. Also useful for improving ocular rosacea. |
| Tetracycline | Initial: 500 mg PO twice daily for 2 weeks Step-down: 500 mg PO once daily for 3-4 weeks Maintenance/taper: 250 mg PO once daily for a further 3-4 weeks as rosacea is controlled | GI upset, photosensitivity, yeast overgrowth; rare azotemia, pseudotumor cerebri; contraindicated in pregnancy | Absorption reduced by iron, bismuth, and aluminum-/calcium-/magnesium-containing products and dairy foods -- separate by 2 hours | Lowest-cost oral option. Also useful for improving ocular rosacea. Taper the dose as symptoms improve rather than stopping abruptly. |
| Erythromycin (base) | Typical adult dosing: 250-500 mg PO two to four times daily | GI upset (common, often dose-limiting), rare hepatotoxicity, QT prolongation at high doses | Numerous CYP3A4-mediated interactions; caution with other QT-prolonging drugs | Low-quality evidence specifically in rosacea -- reserve for patients who cannot use doxycycline or tetracycline (e.g., pregnancy, where an antibiotic is genuinely needed and the tetracycline class is contraindicated). |
| Trimethoprim | Typical adult dosing: Per current standard adult dosing for its approved indications; rosacea-specific dosing is not well established | GI upset, rash, rare blood dyscrasias, hyperkalemia | Increased effect of warfarin and methotrexate; caution with potassium-sparing diuretics/ACE inhibitors/ARBs given hyperkalemia risk | Low-quality evidence specifically in rosacea -- reserve for patients who cannot use doxycycline, tetracycline, or minocycline. |
Retinoids
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Isotretinoin (low-dose, oral) | Adults: 0.2-0.3 mg/kg/day PO for 4-5 months | Teratogenicity (major concern), cheilitis, dry skin/mucous membranes, myalgia, possible mood/psychiatric effects | Avoid with tetracyclines (pseudotumor cerebri risk); standard oral-contraceptive interaction cautions as reviewed in the Acne Vulgaris chapter | For treatment-resistant papulopustular disease, and sometimes considered for mild-moderate phyma to slow progression despite limited evidence for that specific use. Prescribing, the mandatory pregnancy-prevention program, and monitoring follow the same protocol detailed in the Acne Vulgaris chapter -- not repeated in full here. |
| Tretinoin (topical) | Adults: Apply a pea-sized amount once daily in the evening, per standard topical retinoid counselling | Erythema, peeling, dryness, irritation, photosensitivity | None established for the topical route | A topical retinoid sometimes used, despite limited direct evidence, to slow progression of mild-moderate phymatous change. |
Ocular rosacea
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Artificial tears (preservative-free) | Adults: 1-2 drops in the affected eye(s) as needed | Generally well tolerated; transient blurring immediately after instillation | None | 1st line for mild ocular involvement, alongside eyelid hygiene. Many OTC brands/formulations are available; preservative-free formulations are preferred for frequent use. |
| Cyclosporine (ophthalmic) | Adults: 1 drop in each affected eye twice daily, about 12 hours apart | Ocular burning (most common), irritation, foreign-body sensation, transient blurred vision, headache | None established -- systemic absorption is negligible | For persistent or severe ocular involvement, typically after ophthalmology referral. Distinct formulation from oral/IV cyclosporine -- not interchangeable. Full benefit can take weeks to months. |
References
- Standard classification and pathophysiology of rosacea: the 2017 update by the National Rosacea Society Expert Committee — Journal of the American Academy of Dermatology (Gallo RL, Granstein RD, Kang S, et al.). J Am Acad Dermatol 2018;78(1):148-155
- Recommendations for rosacea diagnosis, classification and management: update from the global ROSacea COnsensus (ROSCO) 2019 panel — British Journal of Dermatology (Schaller M, Almeida LMC, Bewley A, et al.). Br J Dermatol 2020;182(5):1269-1276
- Updating the diagnosis, classification and assessment of rosacea: recommendations from the global ROSacea COnsensus (ROSCO) panel — British Journal of Dermatology (Tan J, Almeida LMC, Bewley A, et al.). Br J Dermatol 2017;176(2):431-438
- Canadian Clinical Practice Guidelines for Rosacea — Journal of Cutaneous Medicine and Surgery (Asai Y, Tan J, Baibergenova A, et al.). J Cutan Med Surg 2016;20(5):432-445
- Standard management options for rosacea: the 2019 update by the National Rosacea Society Expert Committee — Journal of the American Academy of Dermatology (Thiboutot D, Anderson R, Cook-Bolden F, et al.). J Am Acad Dermatol 2020;82(6):1501-1510
- Interventions for rosacea based on the phenotype approach: an updated systematic review including GRADE assessments — British Journal of Dermatology (van Zuuren EJ, Fedorowicz Z, Tan J, et al.). Br J Dermatol 2019;181(1):65-79
- British Association of Dermatologists guidelines for the management of people with rosacea 2021 — British Journal of Dermatology (Hampton PJ, Berth-Jones J, Duarte Williamson CE, et al.). Br J Dermatol 2021;185(4):725-735
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.