Tinea Versicolor (Pityriasis Versicolor)
Tinea Versicolor (Pityriasis Versicolor)
References
- Tinea Versicolor — StatPearls [Internet], StatPearls Publishing (Karray M, McKinney WP). StatPearls, last updated 2024 Feb 12
- Pityriasis versicolor — DermNet (Oakley A). DermNet, updated September 2014, revised August 2021
- Pityriasis Versicolor—A Narrative Review on the Diagnosis and Management — Life (Basel) (Łabędź N, Navarrete-Dechent C, Kubisiak-Rzepczyk H, Bowszyc-Dmochowska M, Pogorzelska-Antkowiak A, Pietkiewicz P). Life (Basel) 2023;13(10):2097
- Dermacase. Tinea versicolor. — Canadian Family Physician (Prajapati V, Mydlarski R). Can Fam Physician 2008;54(11):1558
Clinical Snapshot
Tinea versicolor — also called pityriasis versicolor, a name still preferred in much of the international literature — is a common superficial skin condition caused by yeasts of the genus Malassezia, organisms that live as normal, permanent residents on essentially everyone's skin rather than being acquired from another person, an animal, or a contaminated object.[1][2] This is the single most important starting point for understanding the condition, and it is what genuinely separates tinea versicolor from the dermatophyte "ringworm" infections (tinea corporis, tinea capitis, tinea pedis) covered elsewhere on this platform: those organisms are not normal skin flora and must be transmitted to cause any infection at all, while tinea versicolor develops when an organism already present on virtually every patient's skin shifts from its usual harmless yeast form into an actively growing, pigment-disrupting one.[1][3] Despite the name, this is not an infection in the ordinary contagious sense, and household or contact-based transmission is not a meaningful clinical concern the way it is for ringworm.[1]
Clinically, it presents as multiple well-demarcated, finely scaling, round-to-oval macules and patches that are either lighter (hypopigmented) or darker (hyperpigmented) — sometimes pink or coppery-brown — than the surrounding skin, most often on the trunk, neck, and upper arms.[1][2][4] Reported prevalence varies enormously with climate, from roughly 1% in cold northern climates to as much as 50% in some tropical regions, and the condition is most common in adolescents and young adults, when sebaceous gland activity is at its peak.[1][3] A genuinely important, frequently under-counselled point anchors this entire chapter: after successful antifungal treatment the yeast is cleared quickly, but the pigment change it leaves behind — particularly hypopigmentation — can take weeks to several months to fully normalize, because melanocyte function recovers on its own separate timeline from mycological cure. This lag is the single most common, and most avoidable, source of patients, and sometimes clinicians, mistakenly concluding that treatment has failed.[1][2]
Recognize the Condition
Pathophysiology — an overgrowth of resident flora, not an acquired infection
Malassezia species — principally M. globosa, M. furfur, and M. sympodialis — are lipophilic yeasts that depend on skin-surface lipids for growth and are present on the skin of essentially every person from shortly after birth onward.[1][2] In most people they remain in their harmless, round budding-yeast form indefinitely and cause no disease whatsoever. Tinea versicolor develops when local conditions favour the yeast's conversion into an actively proliferating mycelial (hyphal) form, a transition driven by a recognizable set of environmental and host factors: heat and high humidity, heavy sweating (hyperhidrosis), naturally oily skin or the use of oily or occlusive emollients and sunscreens, topical or systemic corticosteroid use (including endogenous Cushing syndrome), oral contraceptive use, pregnancy, malnutrition, and any form of immunosuppression.[1][3] A genetic predisposition also appears to play a role — roughly 1 in 5 affected patients report a positive family history — and prolonged occlusion, including from tight synthetic clothing or, as newly recognized, prolonged face-mask wear, is a further contributing factor.[3]
This mechanism is this chapter's central organizing idea, and it is worth stating plainly because it is so easy to blur with the platform's Ringworm chapter given the shared "tinea" label: dermatophytes such as Trichophyton and Microsporum species are not normal skin residents, so tinea corporis and tinea capitis are genuinely acquired infections with real person-to-person, animal, and fomite transmission that warrant household decontamination counselling. Malassezia, by contrast, is already there — tinea versicolor is a disease of local overgrowth and transformation of an organism the patient already carries, not one they caught, and neither the patient nor their household needs the pet-check, comb/hat/pillowcase decontamination, or school-exclusion counselling that anchors the Ringworm chapter.[1]
Why the pigment changes, and why they lag behind cure
The two pigment patterns have distinct, well-described mechanisms. Hypopigmentation — the more common and more cosmetically noticeable pattern, especially in richly pigmented skin — is caused by dicarboxylic acids, principally azelaic acid, that the yeast produces as a metabolic byproduct; these diffuse into the epidermis and competitively inhibit tyrosinase, the rate-limiting enzyme melanocytes need to produce melanin, and may also have a direct effect on melanocyte viability.[1][3] Hyperpigmentation, seen more often on already darker or more sun-exposed skin, instead reflects the skin's inflammatory response to the yeast and its metabolites, together with abnormally large melanosomes within the affected keratinocytes.[1][3] Because both mechanisms act on melanocyte biology rather than on the yeast itself, clearing the yeast with antifungal therapy does not immediately reverse either pigment change — melanocyte tyrosinase activity and melanosome transfer need their own time to normalize, which is why hypopigmented patches in particular can remain visibly pale for weeks to several months after a genuinely successful, mycologically confirmed cure.[1][2]
What it looks like, and where
Lesions are typically multiple, well-demarcated, round-to-oval macules or thin patches, individually often 1 cm or less but frequently coalescing into larger, irregular areas; a fine, powdery scale becomes more obvious when the skin is gently stretched or scraped — the "evoked scale sign" — even when it is not obviously visible at rest.[3][1] Colour ranges from pale hypopigmented to tan, reddish-pink, or dark coppery-brown, which is exactly what gives the condition its Latin name — versicolor, "of various colours" — since different patients, and even different patches on the same patient, can show different shades at once.[1][4] The classic distribution is the upper trunk, back, chest, neck, and proximal upper arms; facial involvement is uncommon in adults but seen more often in children.[1][2]

Most patients are asymptomatic or report only mild itch, and many present primarily for cosmetic reasons — the pigment change, not discomfort, is usually what actually brings someone to a pharmacy or clinic.[2][1] A minority of presentations depart from this classic picture and are worth recognizing by name: inverse tinea versicolor involves flexural sites (axillae, groin, antecubital fossae) rather than the trunk and is seen more often in immunosuppressed patients; a follicular (folliculitis-like) form produces discrete, itchy, follicle-centred papules and pustules and is associated with diabetes, occlusion, and corticosteroid use; and a less common papular/inflammatory form produces small erythematous papules on the trunk rather than flat, scaling macules.[3]
Risk Factors
- Adolescence and young adulthood — the age of peak sebaceous gland activity and the single strongest demographic predictor.[1][3]
- Hot, humid climate and season — prevalence is dramatically higher in tropical and subtropical regions, and in temperate climates flares characteristically cluster in summer.[1][2]
- Hyperhidrosis and heavy sweating from exercise, occupation, or climate.[1][3]
- Naturally oily skin, and use of oily or occlusive moisturizers, sunscreens, and cosmetic products.[1][3]
- Occlusive clothing, tight synthetic fabrics, and prolonged face-covering wear.[3]
- Topical or systemic corticosteroid use, including endogenous hypercortisolism (Cushing syndrome).[1][3]
- Oral contraceptive use and pregnancy.[3]
- Immunosuppression from any cause, and diabetes — both associated with more extensive or atypical (inverse, follicular) presentations.[3]
- Malnutrition and generally poor health.[3]
- Family history — roughly 1 in 5 affected patients report an affected first-degree relative, suggesting a genuine genetic predisposition layered on top of the environmental triggers.[3][1]
- A personal history of tinea versicolor — recurrence, discussed under Monitoring & Follow-Up and Choose Initial Treatment, is the norm rather than the exception.[3]
Red Flags & Refer
Most tinea versicolor is straightforward to recognize and manage with topical or, when needed, oral antifungal therapy. Escalate assessment for any of the following:
- Diagnostic uncertainty, particularly persistent or treatment-refractory patches that do not respond to an adequate, adherent antifungal course — reconsider the diagnosis (see Assessment & Diagnosis) rather than repeating or intensifying the same antifungal regimen; genuinely refractory, atypical, or infiltrated lesions occasionally warrant biopsy to exclude a mimic such as early mycosis fungoides.[1][3]
- Widespread, unusually inflammatory, or atypical (inverse or follicular) disease in a patient with no previously identified predisposing factor — consider and evaluate for underlying diabetes, corticosteroid use, or immunosuppression rather than treating the skin finding in isolation.[3]
- Non-scaling, non-itchy pale or coppery patches on the palms, soles, or genital area, especially with any systemic symptoms or a relevant sexual history — consider secondary syphilis, which can superficially mimic tinea versicolor but will not show hyphae or spores on KOH and needs an entirely different work-up.[1]
- Suspected pityriasis alba or vitiligo being treated empirically as tinea versicolor without confirmation — neither will respond to an antifungal, and continuing to treat the wrong diagnosis only delays appropriate counselling or referral (see Common Errors to Avoid).
- A patient requesting oral therapy who is pregnant or breastfeeding — needs prescriber-directed decision-making rather than self-care (see Special Populations).
- Very frequent recurrence, on the order of several episodes per year — a genuine trigger to proactively discuss a structured prophylactic regimen rather than simply re-treating each new flare acutely (see Treatment Targets and Choose Initial Treatment).
Assessment & Diagnosis
Diagnosis is usually clinical
The distinctive, well-demarcated, finely scaling, variably pigmented macules in a trunk/neck/upper-arm distribution are often diagnostic on inspection alone, especially once the evoked scale sign is elicited by gently scratching or stretching a patch.[3][1] Confirmatory testing is most useful when the diagnosis is not obvious, when treatment has already failed, or when a mimic needs to be excluded.
KOH microscopy: "spaghetti and meatballs"
Potassium hydroxide (KOH) preparation of a gentle skin scraping, taken preferentially from the periphery of an active patch, is the most useful point-of-care confirmatory test. Under the microscope, Malassezia in its pathogenic form produces a characteristic mixture of short, curved hyphae and round budding yeast cells — classically described as looking like "spaghetti and meatballs" — a finding that is essentially diagnostic when seen.[1][3] Adding a drop of methylene blue, chlorazol black, or even ordinary blue-black ink to the KOH preparation improves contrast and makes the organisms easier to identify.[3] A genuinely important caveat: KOH microscopy is a sensitive test in experienced hands but is not 100% sensitive, so a negative preparation in a clinically classic presentation does not rule out the diagnosis.[3]
Wood's lamp examination
Under a Wood's lamp (UV-A light), affected patches can show a yellow-green to golden or coppery-orange fluorescence.[1][2] This is a useful positive finding when present, but — in a genuinely different way from the organism-specific fluorescence pattern discussed in this platform's Ringworm chapter — fluorescence in tinea versicolor is simply inconsistent from patient to patient: it is reported in well under half of confirmed cases, so a negative Wood's lamp examination provides essentially no reassurance and should never be used on its own to exclude the diagnosis.[1][3] A useful side note for the differential: erythrasma, a superficial bacterial infection caused by Corynebacterium minutissimum that can mimic tinea versicolor in a body-fold distribution, instead fluoresces coral-red under Wood's lamp — a genuinely different colour that helps separate the two when fluorescence is present.
Dermatoscopy
Dermatoscopy can support the diagnosis when available: hypopigmented lesions show fine, diffuse scale over a relatively well-defined pale area, while hyperpigmented lesions show tan-to-brown structureless areas with furrowed scale; a peripheral halo of the opposite pigment change (the "contrast halo sign") and small satellite globules are further supportive features.[3]
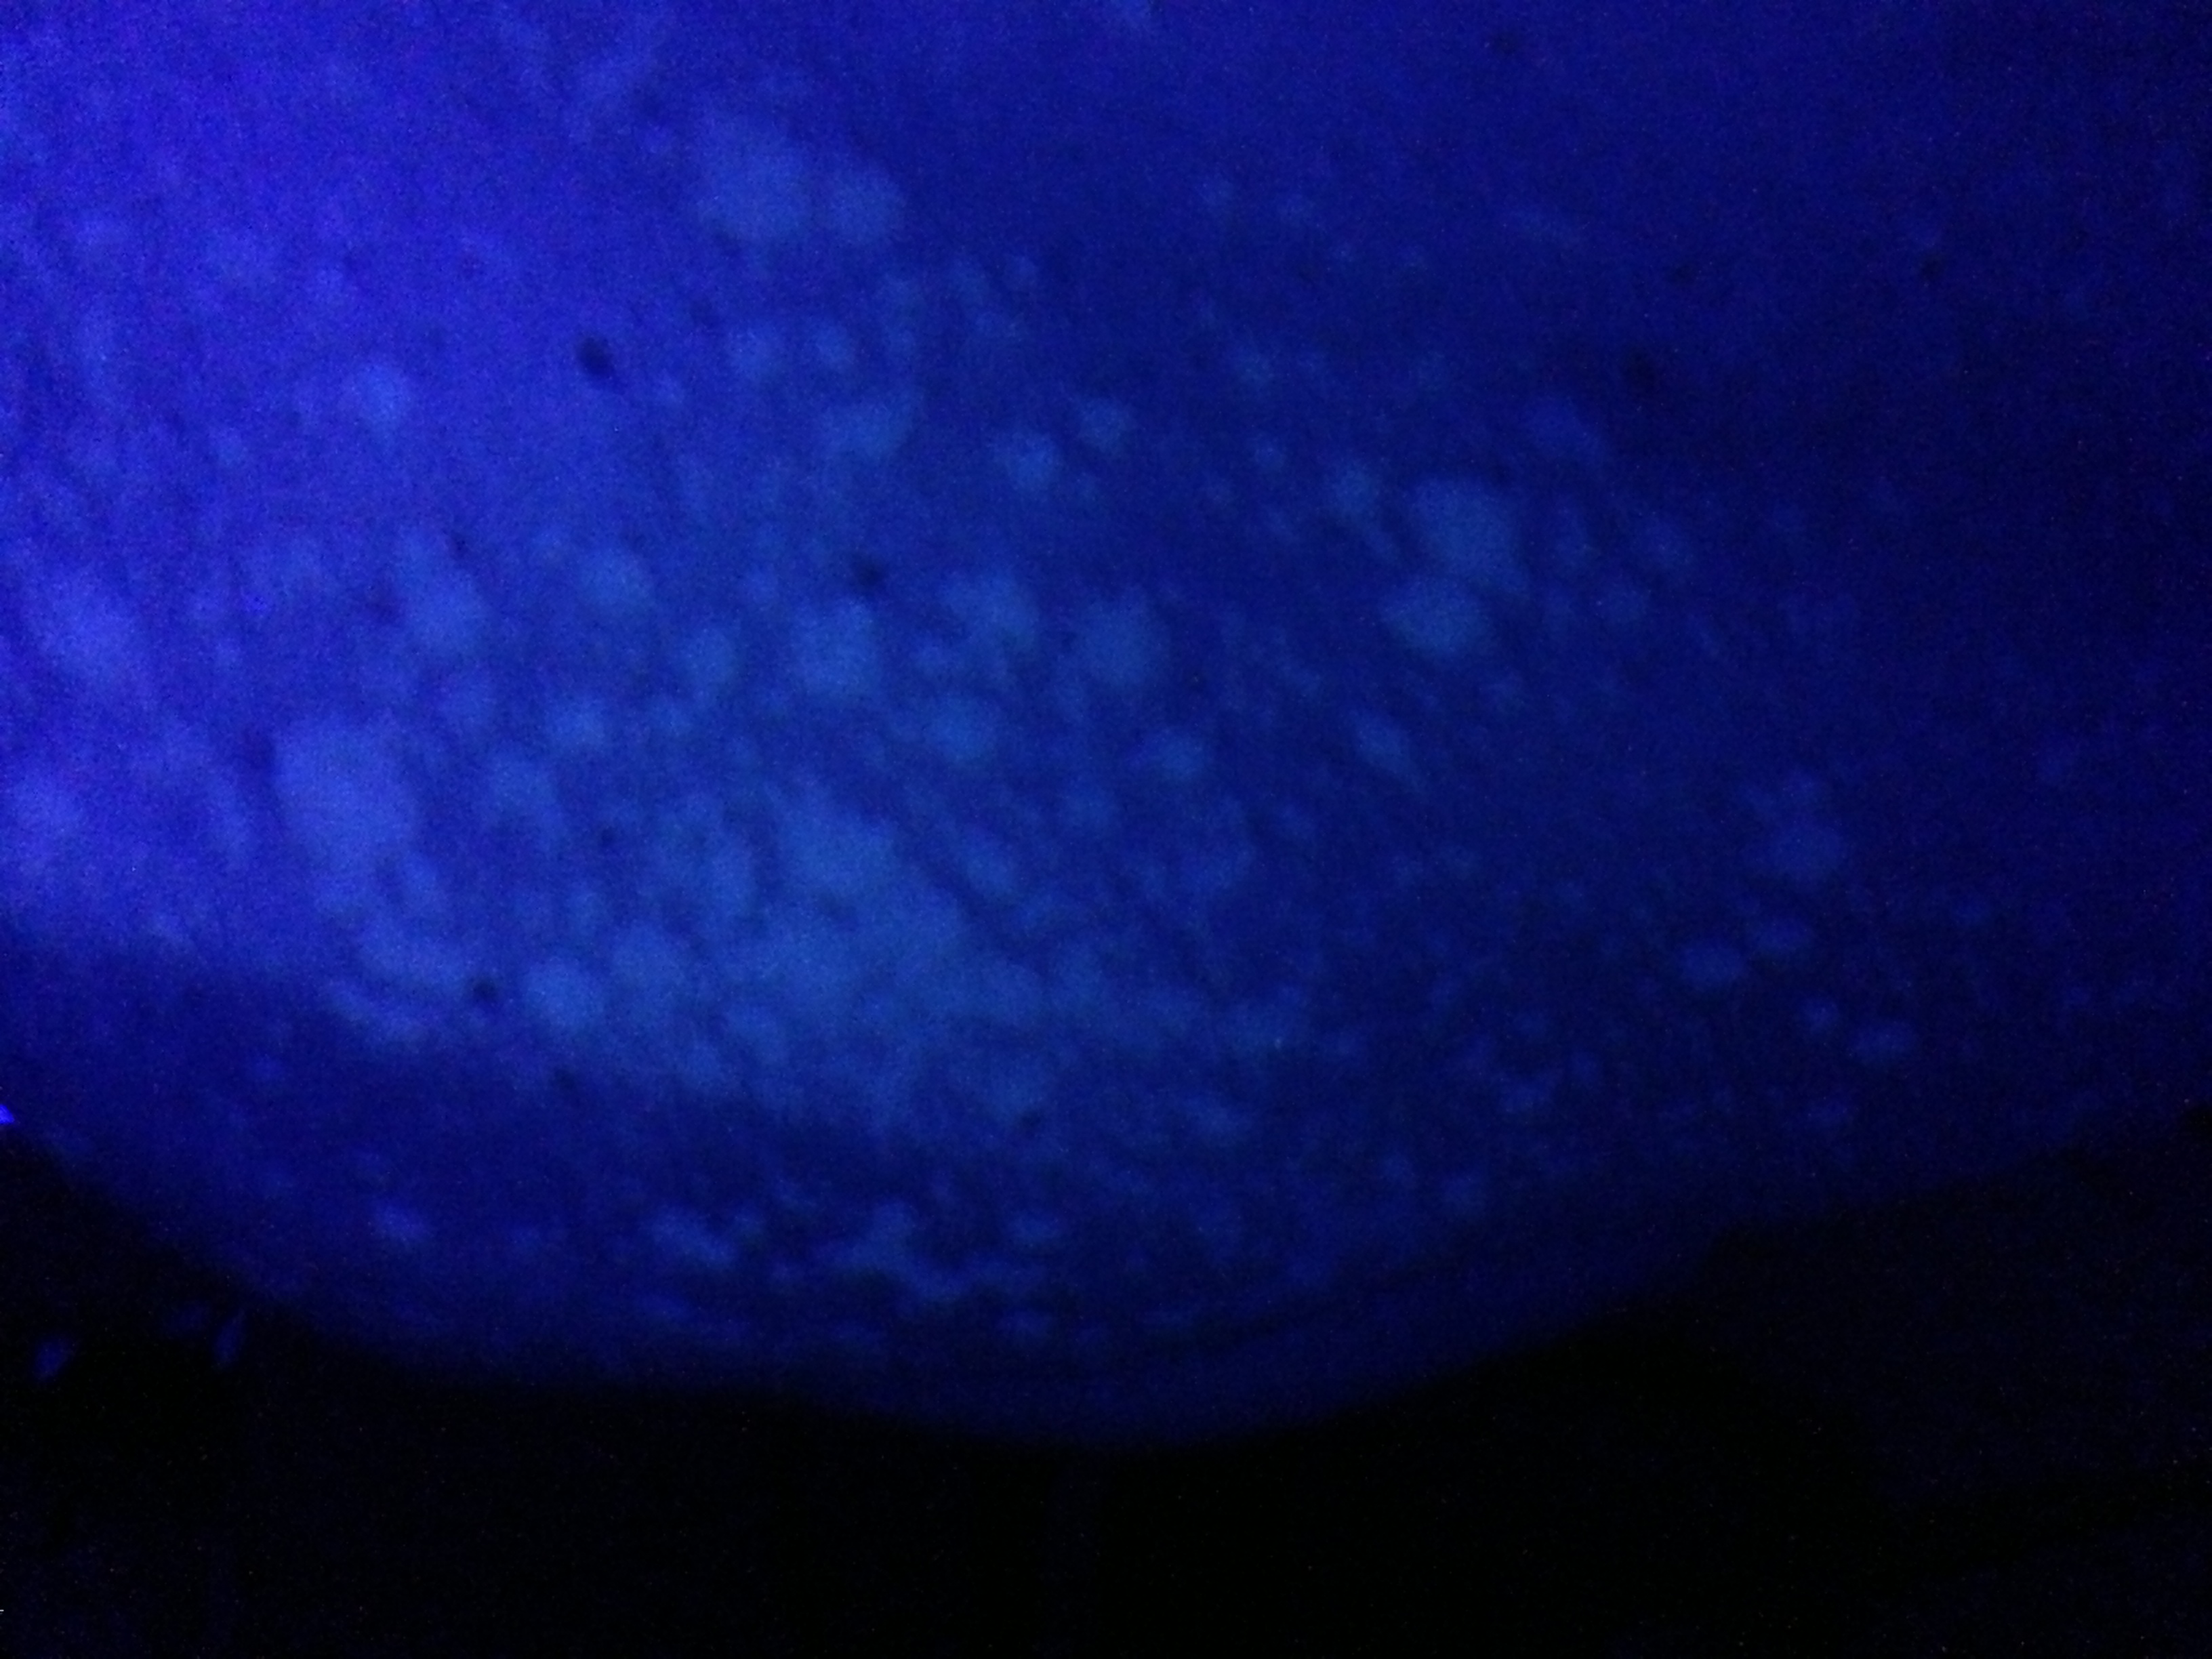
Differential diagnosis
| Condition | Features that point away from tinea versicolor |
|---|---|
| Vitiligo | Completely depigmented (not just hypopigmented), smooth, non-scaling, sharply demarcated white macules, often symmetric and favouring periorificial and acral sites; KOH is negative and Wood's lamp shows a stark chalk-white fluorescence rather than the tinea versicolor pattern. |
| Pityriasis alba | Ill-defined, mildly scaly, pale patches on the face and upper arms of children and adolescents, typically with a personal or family history of atopic dermatitis; lacks the well-demarcated border and trunk-predominant distribution of tinea versicolor. |
| Postinflammatory hypo- or hyperpigmentation | A clear history of a preceding inflammatory dermatosis (eczema, psoriasis, acne, an injury) at that exact site, without active scale or a positive KOH. |
| Seborrheic dermatitis | Erythema with thicker, greasy, yellow-white scale concentrated in sebum-rich sites (scalp, eyebrows, nasolabial folds); a genuinely different, inflammatory rather than pigmentary, Malassezia-related condition — see the platform's separate Seborrheic Dermatitis chapter. |
| Pityriasis rosea | A single herald patch followed by a "Christmas-tree" distributed eruption of oval lesions along skin cleavage lines, each with a trailing (inward-facing) collarette of scale rather than diffuse fine scaling. |
| Guttate psoriasis | Numerous small, thicker plaques with a silvery-white scale, often following a streptococcal pharyngitis; scale is coarser and more adherent than the fine, powdery scale of tinea versicolor. |
| Tinea corporis | An annular, expanding lesion with an active, raised, scaly border and central clearing, caused by a dermatophyte rather than Malassezia — see the platform's Ringworm chapter. |
| Erythrasma | A superficial bacterial (Corynebacterium) infection of body folds — reddish-brown, sharply marginated patches with fine scale that fluoresce coral-red, not yellow-green/copper, under Wood's lamp. |
| Secondary syphilis | Often involves the palms and soles, may be accompanied by systemic symptoms and lymphadenopathy, and does not show hyphae or spores on KOH; consider in a patient with a relevant sexual history. |
| Confluent and reticulated papillomatosis (Gougerot-Carteaud) | Hyperpigmented, verrucous-feeling papules that coalesce into a reticulated (net-like) pattern, classically on the central chest/back; KOH-negative and needs an entirely different treatment approach, typically minocycline. |
| Mycosis fungoides (early/patch stage) | Persistent, often asymmetric patches that do not clear with antifungal therapy and do not show organisms on KOH; consider biopsy for any genuinely treatment-refractory or atypical presentation. |
Investigations
Fungal culture is not useful for tinea versicolor — Malassezia requires specialized lipid-supplemented culture media that most laboratories do not routinely offer, and culture is neither needed nor helpful for diagnosis or management in ordinary practice.[3] Reserve skin biopsy for genuine diagnostic uncertainty, particularly persistent or atypical disease where a mimic such as mycosis fungoides needs to be excluded.[1]
Treatment Targets
- Achieve mycological clearance of the yeast's pathogenic form, confirmed clinically by resolution of active scale and the evoked scale sign, rather than by waiting for pigment to fully normalize.
- Set the pigment-lag expectation explicitly, and before treatment starts, so that a mycologically cured but still visibly discoloured patch weeks later is correctly recognized as expected healing, not treatment failure.
- Treat the entire affected area, including the scalp and hairline as a genuine reservoir, not just the most visible trunk patches.
- Match treatment route and intensity to extent: topical therapy for localized or moderate disease; oral therapy for extensive, hard-to-reach, or topical-refractory disease.
- Correctly exclude non-fungal mimics — vitiligo and pityriasis alba above all — before committing a patient to a course of antifungal therapy that cannot help them.
- Build a realistic, sustainable long-term plan for patients with frequent recurrence, since the causative organism is never eliminated from the skin the way an acquired dermatophyte infection can be — the practical goal is durable control, not a one-time permanent cure.
Choose Initial Treatment
Step 1 — localized or moderate disease: topical therapy
1st line selenium sulfide 2.5% lotion or shampoo, applied to all affected areas — and, importantly, up onto the neck and into the scalp and hairline, a genuine fungal reservoir even when the scalp itself looks unaffected — left on for about 10 minutes before rinsing, once daily for 1-2 weeks, then continued weekly to monthly as maintenance.[1][3] 1st line a topical azole — ketoconazole 2% shampoo applied to wet skin, lathered, left on for about 5 minutes, then rinsed, once daily for 3-5 days (or ketoconazole 2% cream applied once or twice daily for 2 weeks for smaller, well-defined areas) — is an equally reasonable first choice and, unlike selenium sulfide, has no odour or discoloration drawback.[1][3] Alternative topical terbinafine 1% solution or cream, once or twice daily for 1-2 weeks (up to 4 weeks for more resistant disease), or topical ciclopirox, clotrimazole, or miconazole, applied once or twice daily for about 2 weeks, are all reasonable alternatives with broadly comparable efficacy.[1][3]
Step 2 — extensive, widespread, hard-to-reach, or topical-refractory disease: oral therapy
1st line oral itraconazole 200 mg once daily for 5-7 days is the most consistently supported oral regimen for extensive or recurrent tinea versicolor.[1][3] Alternative oral fluconazole, most often given as 300 mg once weekly for 2-4 weeks, is a reasonable alternative, particularly when once-weekly dosing will genuinely improve adherence compared with a daily course.[1][3] A short course of a topical agent (selenium sulfide or a topical azole) can reasonably be layered on top of either oral regimen over the treated body surface to speed clearance, and either oral agent should still be paired with the same scalp and hairline coverage described in Step 1.[3]
Agents that do not work for this indication — despite working well for dermatophyte "ringworm"
Avoid — ineffective oral terbinafine and oral griseofulvin, both mainstays of this platform's Ringworm chapter, are not effective for tinea versicolor: terbinafine given orally is not delivered to the skin surface in effective concentration through sweat and sebum the way it needs to be to reach Malassezia, and griseofulvin has essentially no useful activity against yeasts at all.[3] Do not substitute either for the oral azoles above under the assumption that "an oral antifungal is an oral antifungal." Avoid oral ketoconazole is no longer recommended for this or any indication, given its risk of clinically significant hepatotoxicity and adrenal insufficiency relative to the equally effective, safer oral azole alternatives above.[1][3]
Frequent recurrence: move from acute treatment to planned prophylaxis
For patients with frequent relapse once acute disease has cleared, a structured maintenance regimen meaningfully reduces relapse and is worth proactively offering rather than waiting for the next flare to be brought in: topical selenium sulfide or ketoconazole shampoo applied to the trunk once monthly, or more intensively during the warmer or more humid months when recurrence risk is highest; or oral itraconazole 200 mg (two 100 mg capsules) taken once monthly for 6 consecutive months, a regimen shown in a placebo-controlled trial to keep 88% of patients disease-free at follow-up versus 57% with placebo.[3][1]
Non-Pharmacologic Treatment
- Shower promptly after heavy sweating or exercise, and favour looser, more breathable fabrics over tight synthetic clothing in hot or humid conditions.
- Switch to oil-free, non-comedogenic ("dry-touch") moisturizers and sunscreens, particularly on the trunk and neck, since oily and occlusive products are a recognized trigger for conversion to the pathogenic yeast form.[1][3]
- Do not rely on sun exposure or tanning as a treatment. It does not clear the underlying yeast overgrowth, and because unaffected surrounding skin tans normally while a hypopigmented patch generally cannot, sun exposure often makes the contrast between affected and unaffected skin more obvious rather than less — counsel patients explicitly against this common, well-intentioned but counterproductive habit, and continue routine sun protection.[2]
- Set the pigment-lag expectation clearly and in advance: continued visible lightening or darkening for weeks to a few months after a completed, effective treatment course is the expected healing process, not a sign that treatment did not work — repeating or escalating antifungal therapy for pigment alone, without persistent scale or a positive KOH, is not indicated.[1][2]
- Reassure that tinea versicolor is not caused by poor hygiene and, unlike the dermatophyte "ringworm" infections, is not meaningfully contagious to others — no household screening, pet check, or fomite decontamination is needed.[1]
- For patients with a clear seasonal pattern, plan and start a maintenance regimen before the next high-risk season rather than waiting for the next visible flare.[3]
- Laundering recently worn clothing, towels, and bedding in hot water during active treatment is a reasonable, low-burden adjunct measure, even though — unlike dermatophyte ringworm — fomite transmission is not the primary driver of this condition.[3]
Pharmacologic Treatment Options
| Drug / intervention | Role | Dose / use | Important adverse effects | Teaching points |
|---|---|---|---|---|
| Selenium sulfide 2.5% (lotion/shampoo) Preferred | 1st line, localized or extensive disease, and maintenance | Apply to all affected skin plus the neck and scalp/hairline, leave 10 minutes, once daily for 1-2 weeks; then weekly to monthly for maintenance | Scalp/skin irritation, oiliness or dryness of hair, odour, discoloration of light-coloured hair or fabric with overuse | No Pharmasist Drug Database monograph exists for this OTC product; named as text only. Effective, inexpensive first choice — treat the scalp reservoir even if only the trunk is visibly affected. |
| Ketoconazole 2% (shampoo/cream) Preferred | 1st line, localized or extensive disease | Shampoo: apply to wet skin, lather, leave 5 minutes, rinse, once daily for 3-5 days. Cream: apply once or twice daily for 2 weeks for smaller areas | Local burning/stinging (uncommon) | No odour or discoloration drawback of selenium sulfide; a reasonable default first choice. |
| Terbinafine 1% (topical solution/cream) Alternative | Alternative topical agent | Apply once or twice daily for 1-2 weeks, up to 4 weeks for resistant disease | Local irritation | Topical terbinafine works well against Malassezia — do not confuse with the oral form, which does not (see below). |
| Ciclopirox (topical) Alternative | Alternative topical agent | Apply once or twice daily for about 2 weeks | Local irritation | Broad-spectrum agent with fungistatic, mild antibacterial, and anti-inflammatory activity. |
| Clotrimazole 1% (cream) Alternative | Alternative topical agent; pregnancy-preferred | Apply once or twice daily for about 2 weeks | Local irritation | One of the topical agents specifically considered a reasonable pregnancy option given minimal systemic absorption. |
| Miconazole 2% (cream) Alternative | Alternative topical agent | Apply once or twice daily for about 2 weeks | Local irritation | Comparable efficacy to the other topical azoles for this indication. |
| Itraconazole (oral) Preferred | 1st-line oral agent, extensive/recurrent/topical-refractory disease | 200 mg PO once daily for 5-7 days for acute treatment; 200 mg PO once monthly for 6 months for prophylaxis in frequent recurrence | GI upset, headache; rare hepatotoxicity, heart failure | Most consistently supported oral regimen for this indication. Potent CYP3A4 inhibitor — screen the full medication list before dispensing. |
| Fluconazole (oral) Alternative | Alternative oral agent, extensive/recurrent/topical-refractory disease | 300 mg PO once weekly for 2-4 weeks | Nausea, headache; rare hepatotoxic reactions | Once-weekly dosing can genuinely improve adherence compared with a daily itraconazole course. |
| Terbinafine (oral) Avoid | NOT effective for tinea versicolor | Not recommended for this indication at any dose | GI upset, headache, transient taste/smell disturbance; rare hepatotoxicity | Does not reach the skin surface in adequate concentration to treat Malassezia, despite being 1st-line oral therapy for dermatophyte ringworm — do not substitute. |
| Griseofulvin (oral) Avoid | NOT effective for tinea versicolor | Not recommended for this indication at any dose | Photosensitivity, GI upset, headache, hepatic dysfunction | No useful activity against yeasts — a dermatophyte-only agent, despite its role in the Ringworm chapter. |
| Ketoconazole (oral) Avoid | No longer recommended for this indication | Not recommended given safer alternatives | Hepatotoxicity, adrenal insufficiency | Superseded by oral itraconazole/fluconazole, which achieve comparable efficacy without this risk. |
Special Populations
Pregnancy
Topical therapy is preferred in pregnancy given minimal systemic absorption; selenium sulfide, clotrimazole, and miconazole are all reasonable first choices.[3] Oral itraconazole and fluconazole are reserved for genuinely extensive disease not controlled with topical therapy and need prescriber-directed decision-making — fluconazole in particular carries a dose-dependent teratogenicity signal at the higher, repeated doses sometimes used for other indications, so an oral therapy decision in pregnancy should not default to self-care.
Breastfeeding
Topical antifungals are compatible with breastfeeding given minimal systemic absorption. Oral itraconazole and fluconazole both pass into breast milk in small amounts; the prescribing clinician should weigh the same benefit/risk considerations as in pregnancy before selecting an oral agent.
Children
Tinea versicolor is less common before adolescence but does occur, and facial involvement — uncommon in adults — is seen more often in this age group.[1] Topical selenium sulfide and azole therapy are generally used, with reduced contact time reasonable for younger or more sensitive skin; oral therapy in children needs weight-based, prescriber-directed dosing rather than adult fixed dosing.
Adolescents and young adults
This is the population with by far the highest baseline incidence, driven by peak sebaceous gland activity, and the group most likely to present repeatedly with recurrence — proactive counselling on maintenance or prophylaxis is particularly worthwhile here rather than only reactive treatment of each new flare.[1][3]
Immunosuppression and diabetes
More extensive disease, and the atypical inverse (flexural) and follicular presentations described in Recognize the Condition, are seen more often in patients with diabetes, corticosteroid use, or other immunosuppression.[3] A new, unusually extensive, or atypical presentation without an already-known predisposing factor is worth using as a prompt to ask about these rather than treating the skin finding in isolation.
Darker skin tones
Pigment contrast is generally most cosmetically apparent, and most likely to prompt care-seeking, in more richly pigmented skin, and the post-treatment pigment-lag counselling described throughout this chapter is especially important here — set the expectation explicitly, since the visible gap between mycological cure and full pigment normalization is largest, and most likely to be misread as treatment failure, in exactly this population.[1][2]
Monitoring & Follow-Up
Reassess for mycological response — resolution of active scale and the evoked scale sign — at 2-4 weeks after starting topical therapy, or at completion of a 5-7 day itraconazole course or a 2-4 week fluconazole course for oral therapy.[1][3] Explicitly separate this assessment from pigment normalization, which is expected to lag by weeks to several months and should not, on its own, be treated as evidence that therapy failed — see Treatment Failure/Next Step for how to actually tell the two apart.[1][2]
Patient education
Every patient should leave the visit understanding: this is caused by yeast that already lives on their own skin, not caught from anyone else, so no household screening or decontamination is needed;[1] pigment change resolves on its own timeline, separate from and slower than the infection itself, over weeks to months, and that lag is not treatment failure;[1][2] sun exposure does not treat the condition and often makes the colour contrast more obvious rather than less;[2] and recurrence is common because the organism is never eliminated from the skin, which is exactly why a maintenance plan is worth setting up in advance for anyone with a pattern of repeated episodes.[3]
Treatment Failure / Next Step
- Confirm the original diagnosis was correct before assuming the chosen antifungal has failed — vitiligo and pityriasis alba are the two most commonly confused mimics and will never respond to any antifungal regimen; obtain KOH microscopy if it was not already done.
- Distinguish genuine treatment failure from expected pigment lag: repeat a gentle scrape/scratch for the evoked scale sign, and KOH microscopy if available. No active scale and a negative KOH, with only a residual colour difference, is expected healing — continue reassurance and routine follow-up, not further antifungal treatment.
- Confirm genuine adherence and correct technique — inadequate shampoo contact time, treating only the most visible patch while skipping the scalp/hairline reservoir, or stopping a topical course as soon as symptoms felt better are all common, easily corrected causes of apparent failure.
- If active scale and a positive KOH persist despite an adequate, adherent topical course, escalate to oral therapy (itraconazole or fluconazole) rather than switching to a different topical agent of the same class.
- If active disease persists despite an adequate oral course, reconsider the diagnosis, consider a different oral agent or a combined oral-plus-topical approach, and consider referral to dermatology.
- For a patient who clears reliably but relapses repeatedly, shift the conversation from repeated acute treatment to a structured prophylactic regimen (see Choose Initial Treatment) rather than treating each recurrence as a fresh, unrelated problem.
Common Errors to Avoid
- Treating vitiligo or pityriasis alba with an antifungal because of superficial resemblance to tinea versicolor — confirm with KOH microscopy when there is any real uncertainty, since neither mimic will respond.
- Interpreting persistent pigment change, on its own, as treatment failure and escalating or repeating antifungal therapy that is not actually needed — check for active scale and, if available, KOH status before re-treating.
- Reaching for oral terbinafine or griseofulvin, expecting the same efficacy they have against dermatophyte ringworm — neither is effective against Malassezia.
- Prescribing oral ketoconazole when safer, equally effective oral azole alternatives (itraconazole, fluconazole) are available.
- Treating only the visible trunk lesions while leaving the scalp and hairline untreated, allowing the reservoir to reseed the trunk shortly after apparent clearance.
- Recommending sun exposure or tanning as a way to even out the pigment difference — it does not treat the underlying condition and often makes the contrast more visible.
- Applying this platform's Ringworm-chapter counselling — household pet checks, comb/hat/pillowcase decontamination, school exclusion — to tinea versicolor, which is not a transmissible, acquired infection in the same sense.
- Treating tinea versicolor and seborrheic dermatitis as interchangeable because both involve Malassezia — they are genuinely different conditions, a pigmentary disease of overgrowth versus an inflammatory dermatitis, with different core treatment goals; see Recognize the Condition and the platform's separate Seborrheic Dermatitis chapter.
- Not proactively discussing a maintenance or prophylactic regimen with a patient who has a clear pattern of recurrence, leaving them to re-present for acute treatment of the same problem repeatedly.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Topical Antifungals and Keratolytics (First-Line)
Applied to all affected skin AND the scalp/hairline, a genuine fungal reservoir even when the scalp itself looks unaffected. Reduce to weekly-to-monthly maintenance once clear in patients with frequent recurrence.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Selenium sulfide 2.5%, lotion/shampoo | Acute treatment: Apply to all affected skin plus neck/scalp, leave 10 minutes, once daily for 1-2 weeks Maintenance: Apply once weekly to once monthly | Scalp/skin irritation, oiliness or dryness of hair, odour, discoloration of light-coloured hair or fabric with overuse | None clinically significant given minimal systemic absorption | No Pharmasist Drug Database monograph currently exists for this OTC product; named as text only. Effective, inexpensive first choice. |
| Ketoconazole 2%, shampoo | Dosing: Apply to wet skin, lather, leave 5 minutes, rinse, once daily for 3-5 days | Local burning/stinging (uncommon) | None clinically significant given minimal systemic absorption | Equally effective first choice; no odour or discoloration drawback of selenium sulfide. |
| Ketoconazole 2%, cream | Dosing: Apply once or twice daily for 2 weeks | Local burning/stinging (uncommon) | None clinically significant given minimal systemic absorption | Reasonable for smaller, well-defined areas rather than widespread disease. |
Topical Antifungals (Alternative)
Broadly comparable efficacy to the first-line agents above; a reasonable substitute where cost, availability, or patient preference favours a different agent.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Terbinafine 1%, topical solution/cream | Dosing: Apply once or twice daily for 1-2 weeks, up to 4 weeks for resistant disease | Local irritation | None clinically significant given minimal systemic absorption | Effective topically against Malassezia. Do not confuse with oral terbinafine, which is NOT effective for this indication (see below). |
| Ciclopirox, topical | Dosing: Apply once or twice daily for about 2 weeks | Local irritation | None clinically significant given minimal systemic absorption | Broad-spectrum agent with fungistatic, mild antibacterial, and anti-inflammatory activity. |
| Clotrimazole 1%, cream | Dosing: Apply once or twice daily for about 2 weeks | Local irritation | None clinically significant given minimal systemic absorption | Considered a reasonable topical option in pregnancy given minimal systemic absorption. |
| Miconazole 2%, cream | Dosing: Apply once or twice daily for about 2 weeks | Local irritation | None clinically significant given minimal systemic absorption | Comparable efficacy to the other topical azoles for this indication. |
Oral Antifungals (Extensive, Recurrent, or Topical-Refractory Disease)
Reserved for disease that is extensive, hard to reach with topical therapy, or has not adequately responded to an adherent topical course. Pair with the same scalp/hairline coverage used for topical therapy.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Itraconazole, oral | Acute treatment: 200 mg PO once daily for 5-7 days Prophylaxis, frequent recurrence: 200 mg PO once monthly for 6 consecutive months | GI upset, headache; rare hepatotoxicity, heart failure | Potent CYP3A4 inhibitor — avoid or use with caution with statins metabolized via CYP3A4, calcium channel blockers, digoxin, warfarin, and other CYP3A4 substrates; H2-antagonists and proton pump inhibitors reduce absorption | Most consistently supported oral regimen for this indication. The 6-month monthly regimen is a genuine prophylactic option for frequent recurrence, not just an acute-treatment dose. |
| Fluconazole, oral | Dosing: 300 mg PO once weekly for 2-4 weeks | Nausea, headache; rare hepatotoxic reactions | Inhibits CYP2C9/CYP2C19/CYP3A4 — raises levels of warfarin, phenytoin, sulfonylureas, and other substrates; monitor for toxicity | Once-weekly dosing can genuinely improve adherence compared with a daily itraconazole course. |
Agents to Avoid for This Indication
Each of these is an important, effective option elsewhere on this platform (see the Ringworm chapter for dermatophyte infections) but is specifically NOT appropriate for tinea versicolor — include this distinction explicitly in counselling to prevent a reasonable-sounding but ineffective substitution.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Terbinafine, oral | Dosing: Not recommended for this indication at any dose | GI upset, headache, transient taste/smell disturbance, rash; rare hepatotoxicity, blood dyscrasias | Inhibits CYP2D6, raising levels of tricyclic antidepressants, SSRIs, tramadol, and other CYP2D6 substrates | NOT effective for tinea versicolor — unlike topical terbinafine, the oral form is not delivered to the skin surface in adequate concentration via sweat/sebum to treat Malassezia, despite being 1st-line oral therapy for dermatophyte ringworm. |
| Griseofulvin, oral | Dosing: Not recommended for this indication at any dose | Photosensitivity, GI upset, headache, hepatic dysfunction; contraindicated in pregnancy | Induces hepatic CYP enzymes — reduces efficacy of warfarin and hormonal contraceptives | NOT effective for tinea versicolor — has no useful activity against yeasts; a dermatophyte-only agent. |
| Ketoconazole, oral | Dosing: Not recommended given safer alternatives | Hepatotoxicity (including rare fatal cases), adrenal insufficiency, QT prolongation | Potent CYP3A4 inhibitor with extensive interactions | No longer recommended for tinea versicolor or any indication given its hepatotoxicity/adrenal-insufficiency risk — oral itraconazole and fluconazole achieve comparable efficacy without this risk. |
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.