Tooth Abscess (Periapical and Periodontal Abscess)
Clinical Snapshot
A tooth abscess is a localized collection of pus caused by a bacterial infection of dental origin. Choosing Wisely Canada and the Canadian Dental Association define it precisely: an acute dental abscess is "characterized by spontaneous pain, formation of purulent material, and localized swelling," caused by an infection of the dental pulp — and this is explicitly what separates it from a simple toothache (irreversible pulpitis), which is pain from an inflamed but not yet infected pulp.[1] Getting this distinction right matters immediately for treatment: neither condition is treated with antibiotics, but for different reasons — pulpitis because there is no infection to treat, and an abscess because the infection is walled off in a way antibiotics alone cannot reliably penetrate or resolve.[1][2]
The single most important message in this chapter, repeated deliberately throughout: definitive treatment of a tooth abscess is always dental — incision and drainage, root canal (endodontic) therapy, or extraction — and antibiotics alone are never curative. They are, at most, an adjunct used alongside or while awaiting that definitive dental treatment, and for most well-localized abscesses with prompt dental access, they are not indicated at all.[1][3] This is a genuinely common real-world pharmacy encounter: a patient in dental pain, hoping a course of antibiotics from a pharmacist or walk-in clinic will let them avoid seeing a dentist. It will not, and saying so clearly — while still helping with pain control and making sure the patient actually gets to a dentist — is the correct, evidence-based response.[1][2]
The second essential message is a triage skill: most tooth abscesses are uncomfortable but not emergencies, needing a same-day-to-few-days dental appointment. A minority are genuine emergencies. Spreading facial or neck swelling, trismus (difficulty opening the mouth), difficulty swallowing or breathing, drooling, or tongue elevation signal that infection may be spreading beyond the tooth into the deep spaces of the neck — and Ludwig's angina, a specific, rapidly progressive, life-threatening cellulitis of the floor of the mouth arising almost always from an infected lower molar, is the single highest-yield "must not miss" complication in this entire chapter (see Red Flags & Refer).[4]
Recognize the Condition
Two mechanisms, one presenting complaint
Both types of tooth abscess present with localized pain and swelling, but they arise from genuinely different disease processes, and telling them apart shapes both prognosis and dental management.
Periapical (apical) abscess — the common one
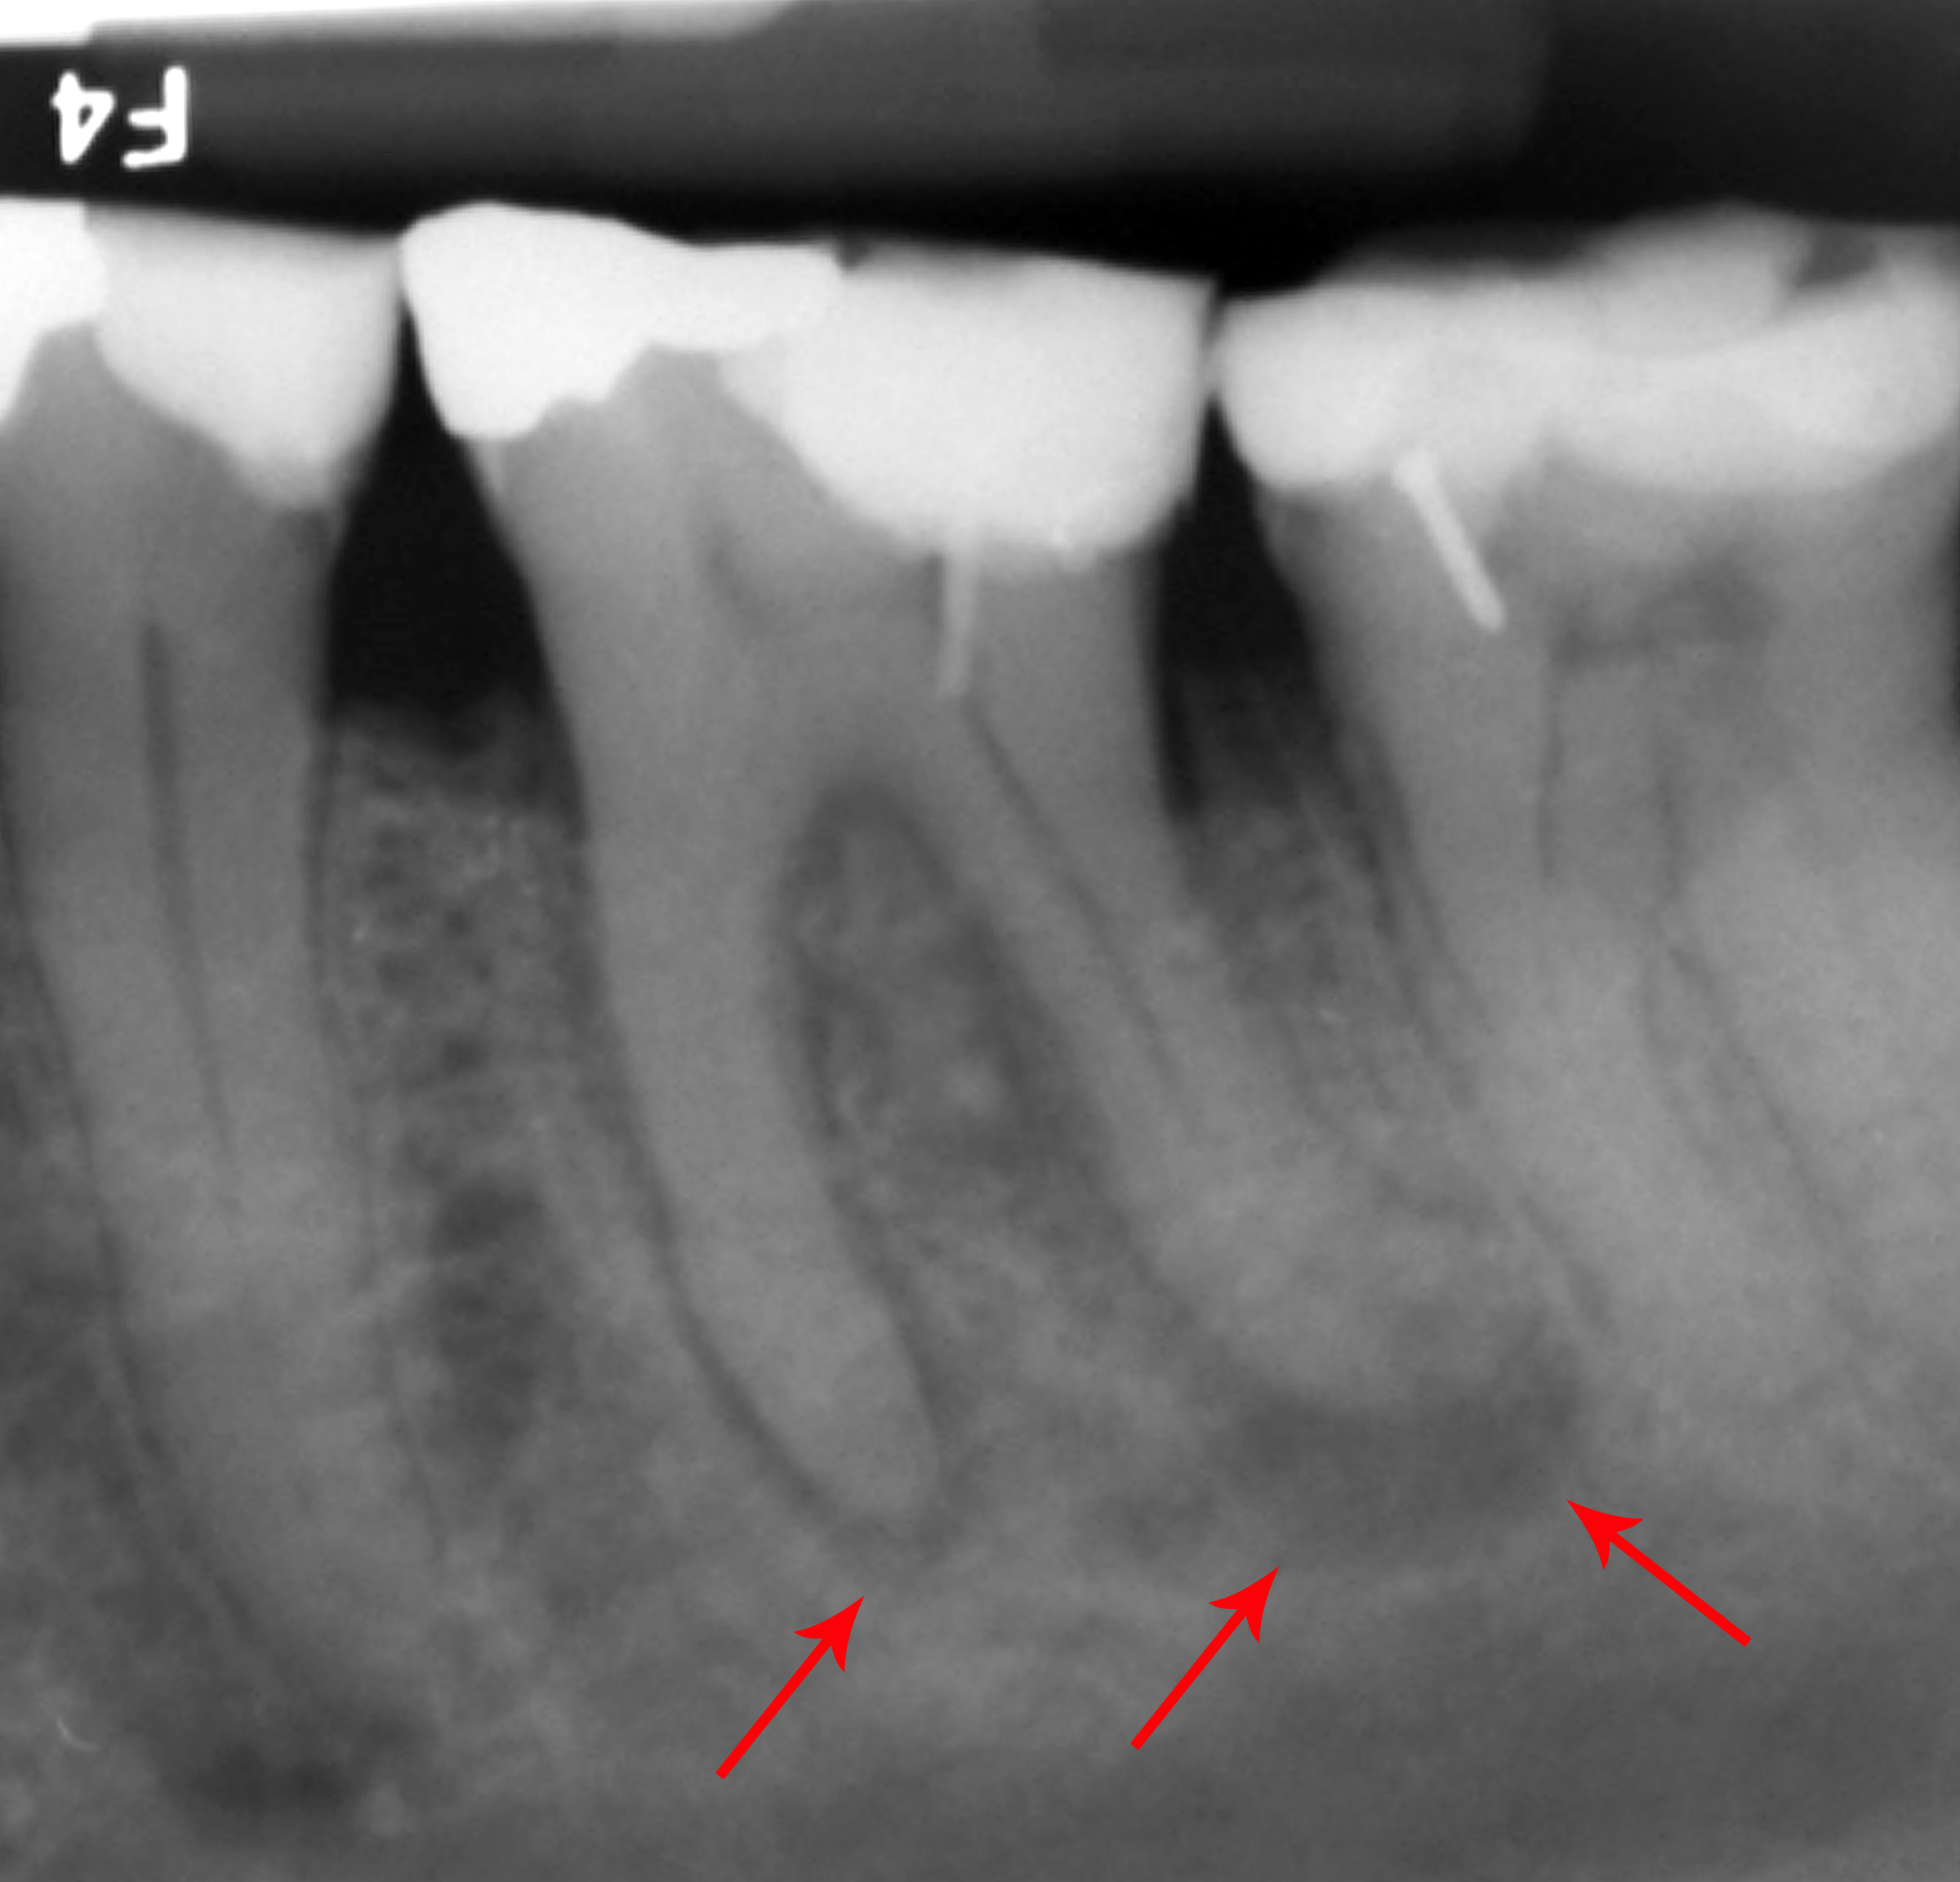
A periapical abscess — also called an acute apical abscess or dentoalveolar abscess — originates inside the tooth. Untreated dental caries erodes through enamel and dentin into the pulp, causing pulpitis (inflammation); if this progresses to irreversible pulpitis and then pulp necrosis, the now-dead, infected pulp tissue allows bacteria to spread out through the root canal system to the tip (apex) of the root, provoking a localized infection and pus collection in the surrounding alveolar bone.[5][6] Dental trauma (a cracked or fractured tooth) or a failed, leaking restoration can cause the same pulp-necrosis pathway without new caries. On dental testing, the tooth is non-vital (does not respond normally to cold or electric pulp testing) and is typically tender to percussion (tapping). A periapical radiolucency — a dark area around the root tip — is often visible on a dental x-ray once the infection has been present for a while, though early infection can precede any visible radiographic change.
Periodontal abscess — arises from the gum, not the pulp
A periodontal abscess originates outside the tooth, in a periodontal pocket — the space between the tooth root and the surrounding gum and bone that deepens with periodontal disease. When that pocket becomes blocked (by calculus, food debris, or a foreign object), trapped bacteria and gingival fluid cause a localized infection within the soft tissue of the pocket wall; most of the actual tissue destruction comes from the host's own neutrophil enzymes responding to the trapped bacteria, not the bacteria alone.[6] Critically, and counterintuitively for a "dental" infection, the tooth itself is usually still vital on pulp testing, because the infection has not entered the pulp — this positive vitality response is the key finding that distinguishes a periodontal from a periapical abscess when a dentist tests it.[6] Periodontal abscesses occur almost exclusively in patients with existing periodontal disease or a recent dental procedure that disturbed a pocket, present with increased probing depths (often over 6 mm) and possible suppuration on probing, and carry a meaningfully worse long-term prognosis for the affected tooth — roughly 45% require extraction even with supportive periodontal therapy.[6]
| Feature | Periapical abscess | Periodontal abscess |
|---|---|---|
| Origin | Necrotic, infected dental pulp | A blocked periodontal pocket |
| Usual cause | Untreated caries, or trauma/a failed restoration | Existing periodontal disease; sometimes recent dental/periodontal treatment |
| Pulp vitality | Non-vital (negative/absent response) | Usually vital (positive response) |
| History | Often a known cavity, a cracked tooth, or old large filling | Known gum disease; deep pockets; recent scaling |
| Radiograph | Periapical radiolucency at the root tip | Widened periodontal ligament space and lateral bone loss, not centred on the apex |
| Definitive dental treatment | Root canal therapy or extraction | Drainage, periodontal debridement, and long-term periodontal therapy; extraction if the tooth's prognosis is poor |
What this distinction means for a pharmacist
Pulp vitality testing and periodontal probing require dental training and instruments a pharmacist does not have — so a pharmacist is not expected to tell these apart definitively. What matters practically is recognizing that either type is a true dental infection that needs dental drainage, asking enough history to support the referral (a known cavity or crack points toward periapical; known gum disease or recent dental work points toward periodontal), and — far more importantly than the periapical/periodontal distinction — screening every presentation for the emergency red flags in the next section before assuming this is a routine referral.
Classic presentation
- Well-localized, often severe, throbbing pain in a specific tooth or area, sometimes worse with chewing, biting, or pressure on the tooth (suggesting periapical inflammation of the surrounding ligament).
- Localized swelling of the adjacent gingiva, and sometimes the adjacent face, that may be soft and fluctuant (feels like a fluid-filled pocket when gently palpated) once pus has collected — a genuinely useful sign, since a fluctuant, well-localized swelling is amenable to drainage, while a firm, diffusely spreading, "woody" induration is a red flag for cellulitis rather than a discrete drainable abscess (see Red Flags & Refer).[7][4]
- A draining sinus tract ("gum boil") on the gum near the affected tooth, sometimes with a foul taste from ongoing drainage — pain can actually decrease once an abscess starts draining spontaneously, which patients can misread as improvement rather than an ongoing infection still needing dental treatment.
- Low-grade fever, malaise, or regional lymph node tenderness/swelling can accompany a larger or longer-standing abscess even without frank spreading infection.
- Tooth mobility or a sense the tooth feels "high" or is the first one to touch when biting, from swelling of the surrounding ligament.
Risk Factors
- Untreated dental caries — the leading cause of periapical abscess, by far the most common single risk factor.
- Dental trauma — a cracked, fractured, or previously injured tooth can undergo pulp necrosis even without new decay.
- A failed, cracked, or leaking dental restoration (filling or crown) allowing bacterial ingress to the pulp.
- Existing periodontal disease and deep periodontal pockets — the primary risk factor specifically for a periodontal abscess.
- A recent dental or periodontal procedure that can transiently block or disturb a periodontal pocket.
- Poor oral hygiene and infrequent dental care, which allow both caries and periodontal disease to progress unchecked.
- Limited access to regular, affordable dental care — a genuinely common and often under-acknowledged driver of patients presenting to a pharmacy or walk-in clinic with an already-established abscess rather than earlier, preventive dental care.
- Smoking, which independently worsens both caries risk and periodontal disease progression.
- Immunocompromise (poorly controlled diabetes, HIV infection, chemotherapy, chronic corticosteroid or other immunosuppressive therapy) and older age — these do not cause an abscess to form, but they raise the risk that a local infection spreads rather than staying contained, and lower the threshold for urgent escalation (see Red Flags & Refer and Special Populations).{C(spLudwig)}
- Recent significant dental work or poor dental hygiene together with immunosuppression, oral trauma, alcohol use, and age over 65 are the specific factors most associated with a dental infection progressing to a deep space infection such as Ludwig's angina.{C(spLudwig)}
Red Flags & Refer
Most tooth abscesses are well-localized and need a same-day-to-few-days dental appointment, not an emergency department. The findings below change that — they signal infection spreading beyond the tooth into the deep tissue planes of the face and neck, and specifically raise concern for Ludwig's angina, a life-threatening emergency. When any of these are present, this is no longer a routine dental referral.
- Facial or neck swelling that is spreading beyond the immediate area of the tooth, or that is firm, diffuse, and "woody"/non-fluctuant on palpation rather than a discrete, soft, fluctuant pocket — suggests cellulitis spreading through the fascial spaces of the face or neck rather than a contained, drainable abscess.[7][4]
- Trismus — difficulty or inability to open the mouth normally — indicates involvement of the muscles of mastication or the deeper fascial spaces, and is itself listed as a specific sign requiring emergency management once significant.[4]
- Difficulty swallowing (dysphagia) or difficulty breathing (dyspnea), drooling (inability to manage secretions), a muffled "hot potato" voice, or visible elevation/protrusion of the tongue — these are the classic warning signs of airway involvement and demand immediate emergency assessment, not a scheduled dental visit.[4]
- Suspected Ludwig's angina specifically — a rapidly progressive, bilateral cellulitis of the floor of the mouth involving the submandibular, sublingual, and submental spaces, arising in about 90% of cases from an infection of a lower second or third molar (a periapical abscess of one of these teeth is the single most common specific source).[4] It classically produces a firm, "bull neck" appearance from submental and submandibular swelling and induration, tongue elevation, trismus, drooling, and dysphagia — and, somewhat counterintuitively, palpable lymphadenopathy is typically absent, which can falsely reassure an examiner expecting to feel enlarged nodes with a spreading infection.[4] Airway compromise is the leading cause of death; mortality exceeded 50% before antibiotics existed and is now roughly 8% with prompt recognition and treatment — a dramatic improvement, but still a genuinely dangerous condition that requires immediate emergency department care, not routine dental referral.[4] If there is any suspicion of Ludwig's angina or airway compromise, call emergency services or send the patient to the nearest emergency department immediately — do not wait to see if it improves.
- Fever, chills, marked malaise, or a rapidly worsening, spreading course — systemic signs of infection beyond a well-localized abscess, particularly concerning if combined with any of the above.[1][2]
- Immunocompromised patients (poorly controlled diabetes, HIV infection, chemotherapy, chronic immunosuppressive therapy) with any dental infection — have a genuinely lower threshold for urgent escalation, since local signs can be blunted while the infection still spreads.[4]
- No access to definitive dental care within a reasonable timeframe for even a well-localized abscess — this does not itself make the presentation an emergency, but it changes the antibiotic decision (see Choose Initial Treatment) and means the pharmacist needs to actively help the patient find a dentist, an emergency dental clinic, or a hospital dental service rather than simply advising "see a dentist."
Assessment & Diagnosis
History
- Which tooth or area, when the pain started, and its character — a well-localized, severe, throbbing pain worsened by chewing or hot/cold points toward a periapical process; pain concentrated at the gumline with a history of gum disease points toward periodontal.
- Any known cavity, cracked tooth, recent dental work, or existing gum disease.
- Swelling — where exactly, whether it is confined to the mouth or extends onto the face/neck, and whether it is spreading.
- Specifically and directly ask about difficulty swallowing, difficulty breathing, drooling, and whether the mouth opens normally — patients do not always volunteer these on their own, and they are the findings that change the entire management plan (see Red Flags & Refer).[4]
- Fever, chills, or feeling generally unwell.
- Immunocompromising conditions, diabetes control, and a full medication list, including any antibiotic already started before this visit.
- Access to a dentist — whether the patient has a regular dentist, and realistically how soon they can be seen.
Examination — within pharmacy scope
Look at and gently palpate the area of swelling: is it confined to the gum/alveolar area near the tooth, or does it extend onto the face or into the neck? Is it soft and fluctuant (suggesting a contained, drainable collection of pus), or firm, diffuse, and spreading (suggesting cellulitis)? Check whether the patient can open their mouth normally, swallow their own saliva without drooling, and speak with a normal voice. Note any visible facial asymmetry, and ask the patient to show you if the swelling has changed size or extent recently. A formal diagnosis — confirming pulp vitality, periodontal probing depth, and radiographic findings that distinguish a periapical from a periodontal abscess — requires a dentist and dental equipment a pharmacist does not have; the pharmacist's exam is for triage (routine dental referral versus emergency), not for making that distinction.[6]
Differential diagnosis
| Condition | Distinguishing features |
|---|---|
| Irreversible pulpitis (simple toothache, no abscess) | Pain only, no purulence, no swelling — the pulp is inflamed but not yet infected; antibiotics are not indicated for this either, but for a different reason than for an abscess.[1] |
| Periodontal abscess | Vital tooth, existing periodontal disease, swelling centred lateral to the tooth in the gum rather than at the apex.[6] |
| Pericoronitis | Inflammation/infection around a partially erupted tooth, classically a lower third molar (wisdom tooth); localized to the operculum (gum flap) over the erupting tooth rather than a discrete apical or pocket abscess. |
| Sialadenitis (salivary gland infection) | Swelling centred over a salivary gland (parotid or submandibular), often with pain on eating (stimulating salivary flow) rather than on biting a specific tooth. |
| Maxillary sinusitis | Upper posterior tooth pain can mimic or coexist with sinusitis (the maxillary molars sit near the sinus floor); consider when multiple upper teeth are tender, or with nasal congestion/facial pressure worse on bending forward. |
| Temporomandibular joint (TMJ) disorder | Pain with jaw movement/chewing without a specific tooth source, no swelling or purulence, often with a history of jaw clicking or clenching. |
| Ludwig's angina / deep neck space infection | The critical "cannot miss" differential — bilateral floor-of-mouth swelling, trismus, tongue elevation, drooling, dysphagia; see Red Flags & Refer.[4] |
No laboratory testing is routinely needed for a straightforward, well-localized abscess assessed and managed by a dentist. Blood work (CBC, blood cultures) and imaging beyond a dental x-ray are reserved for the hospital-level assessment of a patient with systemic or spreading infection.[7]
Treatment Targets
- Achieve source control — drainage of the infection via dental treatment — since this, not antibiotics, is what actually cures a tooth abscess.
- Control pain effectively while the patient is arranging or awaiting dental treatment.
- Recognize and immediately refer any presentation with signs of spreading infection, airway compromise, or systemic sepsis rather than managing it as a routine dental referral.
- Use antibiotics only when genuinely indicated — systemic involvement, or dental drainage that is not promptly accessible — and never as a substitute for dental treatment.
- Correct, clearly and directly, the common misunderstanding that a course of antibiotics from a pharmacist or walk-in clinic can resolve a tooth abscess without seeing a dentist.
- Make sure the patient actually has a realistic plan and timeframe to see a dentist before they leave, not just a prescription.
Choose Initial Treatment
Definitive treatment is always dental — antibiotics are never a substitute
Root canal therapy, extraction, or incision and drainage is what actually resolves a tooth abscess; antibiotics alone do not reliably penetrate a walled-off pus collection and cannot repair the underlying dental problem. Every pathway below assumes the patient still needs to see a dentist for definitive treatment — the only question is whether an antibiotic is also indicated in the meantime.[1][3]
No red flags present — build the plan from here
Well-localized abscess, patient systemically well, prompt dental drainage available no antibiotics — arrange dental drainage (incision and drainage, root canal access, or extraction) and manage pain with an NSAID, with or without acetaminophen (see Drug Tables). Choosing Wisely Canada and the Canadian Dental Association are explicit that antibiotics provide no additional benefit once drainage is achieved for a localized abscess without systemic complications, and this is echoed by the ADA's strong recommendation (from very-low-certainty but consistent evidence) against antibiotics as an adjunct to definitive dental treatment for pulp necrosis with a localized acute apical abscess.[1][3]
Well-localized abscess, systemically well, but definitive dental care is genuinely not accessible promptly the guidance above specifically addresses situations where dental treatment is available in the same visit; when a dentist genuinely cannot be seen for several days, a short antibiotic course as a temporizing bridge is reasonable clinical practice — provided the patient clearly understands this does not replace the dental treatment they still need, and a dental appointment is actively being arranged, not just suggested.
Systemic involvement present (fever, malaise, lymphadenopathy) but no facial/neck spreading, trismus, dysphagia, or other red flag: antibiotics are indicated as an adjunct to urgent dental drainage, not instead of it. Preferred: amoxicillin 500 mg PO 3 times daily for 3-7 days, or penicillin V potassium 500 mg PO 4 times daily for 3-7 days (amoxicillin is generally preferred — broader gram-negative anaerobic coverage and fewer GI adverse effects). Non-severe penicillin allergy: cephalexin 500 mg PO 4 times daily for 3-7 days. Severe penicillin allergy (history of anaphylaxis, angioedema, or hives with penicillin, ampicillin, or amoxicillin): clindamycin 300 mg PO 4 times daily for 3-7 days, or azithromycin 500 mg PO on day 1 followed by 250 mg once daily for 4 more days. If first-line treatment fails to improve symptoms: add metronidazole 500 mg PO 3 times daily for 7 days for broadened anaerobic coverage, or switch to amoxicillin-clavulanate 500/125 mg PO 3 times daily for 7 days.[3] If the clinical condition worsens at any point, or there is any concern about a deeper space infection or an immediate threat to life, refer for urgent emergency evaluation rather than continuing outpatient management.[3]
Any red flag from the list above do not manage this in pharmacy or routine outpatient primary care. Refer immediately to the emergency department, or call emergency services if there is any concern about the airway — this needs IV antibiotics, airway assessment/management, and likely surgical drainage under specialist care, not an oral antibiotic prescription.[4]
Pain control
NSAID monotherapy (ibuprofen), or an NSAID plus acetaminophen in combination, is first-line analgesia for acute dental pain and is more effective than either agent alone or than an opioid alone.[8] Reserve a short course of an opioid analgesic (added to, not instead of, the NSAID/acetaminophen combination) for pain not controlled by first-line therapy, at the lowest effective dose and for as short a duration as possible — rarely more than a few days.[8] See Drug Tables for specific doses.
Non-Pharmacologic Treatment
- Make sure the patient leaves with an actual plan to see a dentist, not just advice to do so — help identify a same-day/emergency dental clinic, a hospital dental/oral surgery service, or the patient's regular dentist's emergency line if they do not have one readily available.
- Do not attempt to lance, squeeze, or otherwise drain the abscess at home — this does not achieve adequate source control and risks pushing infection further into surrounding tissue.
- Avoid applying heat to a swollen face or jaw — a cold compress applied externally can help with pain and swelling, while heat is conventionally avoided over a facial swelling because of concern it may encourage the spread of infection.
- Warm salt-water rinses (about 1/2 teaspoon of salt in a cup of warm water), swished gently and spat out, can provide mild comfort and help keep the area clean while awaiting dental treatment.
- A soft diet and avoiding chewing on the affected side reduces pain and irritation until definitive treatment is completed.
- Maintain good oral hygiene elsewhere in the mouth, brushing gently around the affected area rather than avoiding it entirely.
- Advise the patient explicitly to seek emergency care immediately, rather than waiting for their scheduled dental appointment, if any red-flag symptom develops or worsens — spreading swelling, trismus, difficulty swallowing or breathing, or drooling.
Special Populations
Pregnancy
Untreated dental infection itself carries risk in pregnancy, so definitive dental treatment should not be delayed on account of pregnancy alone — coordinate timing with the dental and prenatal care teams. Amoxicillin, penicillin V, and cephalexin are generally considered compatible in pregnancy at standard doses. Clindamycin is commonly used in pregnancy when a penicillin-class option is not appropriate. Confirm current guidance with the prescriber/pharmacist before metronidazole or azithromycin in pregnancy, and manage pain first-line with acetaminophen; NSAID use in pregnancy needs individualized discussion with the prescriber, particularly regarding timing in the third trimester.
Breastfeeding
Amoxicillin, penicillin V, cephalexin, clindamycin, metronidazole, and azithromycin are all generally considered compatible with breastfeeding at standard doses. Acetaminophen and ibuprofen are standard first-line analgesic choices in breastfeeding.
Pediatrics
All antibiotic and analgesic dosing in this chapter reflects adult doses — pediatric dosing must be calculated on a weight basis per the current product monograph. Children can decompensate faster than adults with a spreading infection or airway threat, so maintain an even lower threshold for emergency referral with any red-flag finding in a child. A "baby tooth" (primary tooth) abscess still needs dental assessment — untreated infection can affect the developing permanent tooth underneath, and the same emergency red flags apply.
Older adults and immunocompromised patients
Poor dental hygiene, recent dental work, alcohol use, and age over 65 are specifically associated with a higher risk of a dental infection progressing to a deep space infection such as Ludwig's angina, and immunocompromise (poorly controlled diabetes, HIV infection, chemotherapy, chronic immunosuppressive therapy) raises the risk that a local infection spreads while producing fewer or milder local warning signs.[4] Maintain a lower threshold for both antibiotic use and urgent/emergency referral in these patients rather than applying the same watchful-waiting approach used for an otherwise healthy adult with a well-localized abscess.
Monitoring & Follow-Up
- Before the patient leaves, confirm they have an actual dental appointment or plan — not just advice to "see a dentist" — and that the timeframe matches the urgency of their presentation (same-day for systemic involvement, promptly for a well-localized abscess).
- For a patient started on an antibiotic: reassess within about 3 days to confirm systemic symptoms are resolving; instruct the patient to stop the antibiotic 24 hours after symptoms have fully resolved, regardless of how many days of the original course remain, rather than automatically completing a fixed longer course.[3]
- Explicitly counsel the patient on which new symptoms mean "go to the emergency department now, do not wait for your appointment" — spreading facial/neck swelling, difficulty opening the mouth, difficulty swallowing or breathing, or drooling.[4]
- If pain is not adequately controlled by the first-line NSAID/acetaminophen combination, reassess rather than simply escalating analgesia further — worsening or poorly controlled pain can itself be a sign the infection is progressing and dental treatment is more urgent than initially thought.
Common Errors to Avoid
- Providing a course of antibiotics without confirming the patient has an actual, realistic plan to see a dentist — the antibiotic is not the treatment, the drainage is.[1][3]
- Agreeing to a patient's request for "just antibiotics" so they can avoid seeing a dentist, rather than clearly and directly correcting this expectation.[1][2]
- Prescribing or recommending an antibiotic for a well-localized abscess with no systemic signs and prompt dental drainage available — the evidence-based recommendation is specifically against this.[1][3]
- Prescribing an antibiotic for irreversible pulpitis (a simple toothache with no swelling or purulence) — there is no infection present to treat.[1]
- Missing early signs of Ludwig's angina by attributing trismus, drooling, or tongue elevation to "just a bad toothache" rather than recognizing them as emergency red flags.[4]
- Assuming the absence of palpable lymphadenopathy makes a spreading infection less likely — lymphadenopathy is typically absent in Ludwig's angina specifically, which can be falsely reassuring.[4]
- Reaching for clindamycin or azithromycin as a default choice rather than reserving them for a genuine, specifically severe penicillin allergy — amoxicillin remains preferred first-line.[3]
- Continuing a fixed antibiotic course rather than stopping 24 hours after symptoms have resolved, or failing to reassess within about 3 days.[3]
- Recommending heat applied externally to a swollen face or jaw.
- Not directly asking about difficulty swallowing or breathing — patients often do not volunteer these symptoms unprompted, and they are the findings that change the entire management plan.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Antibiotics — Adjunct to Dental Drainage Only
Indicated when systemic involvement is present (fever, malaise, lymphadenopathy) alongside urgent dental drainage, or as a short temporizing bridge when dental drainage is genuinely not promptly accessible. Never a substitute for dental drainage. Reassess within about 3 days; stop 24 hours after symptoms fully resolve regardless of days remaining in the original course.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Amoxicillin | Adults: 500 mg PO 3 times daily for 3-7 days | GI upset, diarrhea, hypersensitivity/rash | Reduced efficacy of estrogen-containing oral contraceptives has been described anecdotally; caution with allopurinol (rash risk) | Preferred 1st-line agent — broader gram-negative anaerobic coverage and fewer GI adverse effects than penicillin V. |
| Penicillin V potassium | Adults: 500 mg PO 4 times daily for 3-7 days | GI upset, hypersensitivity/rash | None significant at standard doses | Reasonable 1st-line alternative to amoxicillin; requires more frequent (4 times daily) dosing. |
| Cephalexin | Adults: 500 mg PO 4 times daily for 3-7 days | GI upset, hypersensitivity/rash | None significant at standard doses | For a non-severe penicillin allergy (no history of anaphylaxis, angioedema, or hives with a penicillin) — confirm the specific allergy history before use. |
| Clindamycin | Adults: 300 mg PO 4 times daily for 3-7 days | GI upset, diarrhea, a genuine risk of Clostridioides difficile infection | Increased neuromuscular blockade with neuromuscular blocking agents | For a severe penicillin allergy (history of anaphylaxis, angioedema, or hives); counsel to stop and seek care for severe or persistent diarrhea. |
| Azithromycin | Adults: 500 mg PO on day 1, then 250 mg PO once daily for 4 more days | GI upset, QT interval prolongation | Caution with other QT-prolonging drugs | Alternative to clindamycin for a severe penicillin allergy. |
| Metronidazole | Adults: 500 mg PO 3 times daily for 7 days | GI upset, metallic taste, disulfiram-like reaction with alcohol | Avoid alcohol during and for 24-48 hours after use; may increase warfarin effect | Add to first-line therapy (not a stand-alone treatment) for broadened anaerobic coverage if symptoms are not improving. |
| Amoxicillin / clavulanic acid | Adults: 500/125 mg PO 3 times daily for 7 days | GI upset, diarrhea, hypersensitivity | May increase INR with warfarin; may increase methotrexate levels | Step-up alternative to adding metronidazole if first-line therapy is not improving symptoms. |
Analgesia
An NSAID alone, or an NSAID combined with acetaminophen, is more effective for acute dental pain than either agent alone or than an opioid alone, and is first-line. Reserve a short opioid course, added to (not instead of) first-line therapy, for pain not otherwise controlled.
| Drug | Dosage | Adverse effects | Drug interactions | Comments |
|---|---|---|---|---|
| Ibuprofen | Adults: 400 mg PO every 6-8 hours as needed with food, per product labelling | GI upset/bleeding risk, renal effects with prolonged use | Increased bleeding risk with anticoagulants/antiplatelets; avoid with other NSAIDs | First-line; combine with acetaminophen for a genuine additive analgesic effect. |
| Acetaminophen | Adults: 500-1000 mg PO every 6 hours as needed | Hepatotoxicity with overdose or chronic excess | Confirm total daily acetaminophen from all sources, including any combination product | First-line, alone or combined with an NSAID; do not exceed the labelled maximum daily dose. |
| Acetaminophen / codeine | Adults: Per the product's own Drug Database monograph | Sedation, constipation, nausea, respiratory depression with excessive use; dependence risk | Additive CNS depression with other sedatives, alcohol, or opioids | Reserve for pain not controlled by NSAID plus acetaminophen; use the lowest effective dose for the shortest duration, rarely more than a few days. |
References
- Dentistry List of Tests and Treatments to Question — Canadian Dental Association, in partnership with Choosing Wisely Canada and the Canadian Association of Hospital Dentists. CDA / Choosing Wisely Canada, developed 2018, CDA stewardship effective 2025
- Management of acute dental pain in adults — Canadian Family Physician (Sutherland S, Young J). Can Fam Physician 2026;72(6):395-397
- Evidence-based clinical practice guideline on antibiotic use for the urgent management of pulpal- and periapical-related dental pain and intraoral swelling: A report from the American Dental Association — The Journal of the American Dental Association (Lockhart PB, Tampi MP, Abt E, et al.). J Am Dent Assoc 2019;150(11):906-921.e12
- Ludwig Angina — StatPearls (AL Ghabra Y, Brizuela M, Winters R, Singhal M). StatPearls Publishing, updated 2025 Jun 22
- Root Canal Treatment — Canadian Dental Association, Your Oral Health. CDA Your Oral Health
- Periodontal Abscess — StatPearls (Yousefi Y, Meldrum J, Jan AH). StatPearls Publishing, updated 2023 Jun 12
- Odontogenic Orofacial Space Infections — StatPearls (Hoerter JE, Malkin BD). StatPearls Publishing, updated 2023 Jul 12
- Evidence-based clinical practice guidelines for the management of acute dental pain — American Journal of Emergency Medicine (Green VG, Polk DE, Turturro MA, Moore PA, Carrasco-Labra A). Am J Emerg Med 2024;89:247-253
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.