Viral Conjunctivitis
Clinical Snapshot
Viral conjunctivitis, usually caused by adenovirus, is the most common infectious cause of a red eye in adults.[1] It typically follows an upper respiratory tract infection and is highly contagious, especially in the first 3-7 days. The essential first task is not confirming a viral cause — it is confirming this is conjunctivitis at all and not a sight-threatening red-eye mimic (angle-closure glaucoma, iritis/uveitis, scleritis, keratitis, corneal ulcer), and not herpes simplex or herpes zoster ocular involvement, which — unlike adenoviral conjunctivitis — requires systemic antiviral treatment and ophthalmology co-management.[2]
Recognize the Condition
Typical (adenoviral) presentation
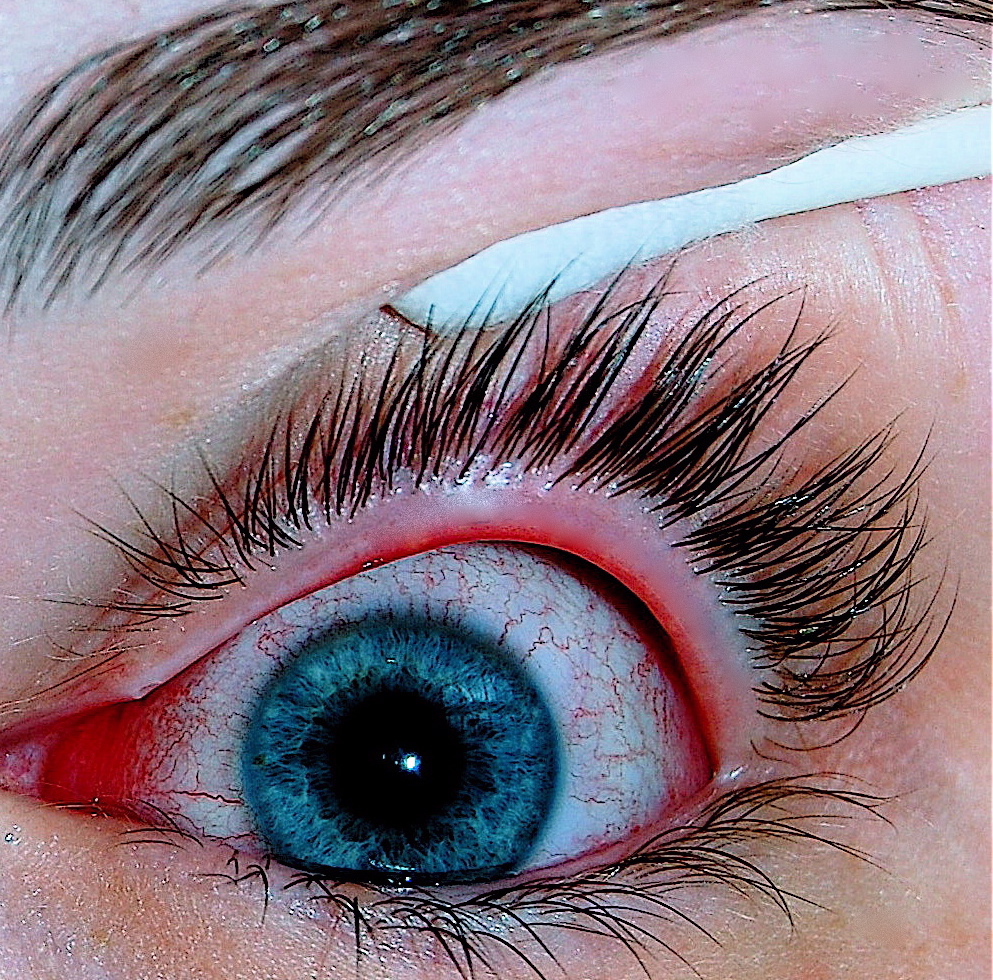
A very red eye with swollen lids, watery discharge, conjunctival membranes, and sometimes subconjunctival hemorrhage. Often follows or accompanies upper respiratory tract infection symptoms (cough, coryza, sore throat). Usually starts in one eye and spreads to the other within days. A preauricular lymph node is a helpful, though not universal, clue.
Herpetic ocular involvement (distinct from typical viral conjunctivitis)
Herpes simplex keratoconjunctivitis
Usually unilateral, often with visible vesicles on the eyelid or periorbital skin, and may show a dendritic (branching) corneal lesion on fluorescein staining. This is a corneal, not just conjunctival, process and needs ophthalmology involvement.
Herpes zoster ophthalmicus
Facial vesicles in a V1 (ophthalmic) trigeminal dermatome distribution with ocular involvement; a vesicle on the tip of the nose (Hutchinson's sign) predicts a higher likelihood of ocular involvement and should prompt urgent ophthalmology referral.
Risk Factors
- Exposure to a person with a red eye or a recent upper respiratory tract infection.
- Community/institutional settings with close contact (schools, daycare, healthcare settings) — adenoviral conjunctivitis spreads easily via hand-to-eye contact and contaminated surfaces.
- History of herpes labialis or prior ocular herpes simplex, for recurrent herpetic keratoconjunctivitis.
- History of varicella/shingles risk factors (older age, immunocompromise) for herpes zoster ophthalmicus.
Red Flags & Refer
Refer immediately to an ophthalmologist (or an optometrist if one is not available) for any of the following:
- Marked redness concentrated at the corneoscleral junction (limbal/ciliary injection), especially if one-sided.
- White corneal opacity or haze.
- Moderate-to-severe pain or photophobia not relieved by a test dose of topical anesthetic.
- Reduced visual acuity.
- An abnormal pupil.
- Recent trauma or chemical exposure.
- A contact-lens wearer with suspected corneal infiltrate/ulcer.
- Chronic unilateral conjunctivitis lasting over 3 weeks.
- Suspected herpes simplex ocular involvement (usually unilateral, eyelid vesicles, possible dendritic corneal lesion).
- Herpes zoster ophthalmicus (facial V1-dermatome vesicles ± Hutchinson's sign).
- Suspected COVID-19-associated conjunctivitis, per current local testing/isolation guidance.[2]
Assessment & Diagnosis
Differentiating bacterial, viral, and allergic conjunctivitis, and blepharitis
These four conditions are the most commonly confused causes of a red, irritated eye in community practice. Distinguishing them correctly determines whether the patient needs an antibiotic, supportive care, an antihistamine, or eyelid hygiene — and getting it wrong means either an unnecessary antibiotic or a missed diagnosis.



| Feature | Bacterial conjunctivitis | Viral conjunctivitis | Allergic conjunctivitis | Blepharitis |
|---|---|---|---|---|
| Laterality | Often one eye first, may spread to the other | Usually starts in one eye, spreads to the other within days | Bilateral, essentially always | Bilateral, essentially always |
| Discharge | Purulent, thick, yellow-green; lids stuck together on waking | Watery to mucoid; no true pus | Watery, stringy/mucoid | Greasy debris and crusting at the lash base, not a true discharge |
| Itching | Minimal or absent | Mild, if present | The dominant symptom — if the patient does not report itching, reconsider allergic conjunctivitis | Mild irritation/burning more than itching |
| Associated findings | May follow otitis media in children; no preauricular node in most cases | Preauricular lymph node, recent URTI, conjunctival membranes, subconjunctival hemorrhage | Chemosis (conjunctival swelling), lid edema, history of atopy/seasonal pattern | Lash crusting, missing/misdirected lashes, recurrent styes, meibomian gland dysfunction |
| Typical course | Self-limited over 1-2 weeks even without treatment; antibiotics modestly shorten this | Self-limited over 1-3 weeks; highly contagious for the first 3-7 days | Persists as long as allergen exposure continues; recurs seasonally | Chronic, relapsing; managed rather than cured |
| 1st-line management | Often no treatment needed; a topical antibiotic modestly shortens recovery | Supportive care only — cold compresses, lubricants | Remove/avoid the allergen; topical antihistamine/mast-cell stabilizer | Lid hygiene: warm compresses plus lid margin cleansing |
History
- Unilateral or bilateral onset, duration, and progression — viral conjunctivitis classically starts in one eye and spreads.
- Preceding or concurrent upper respiratory tract infection symptoms.
- Exposure to a person with a red eye.
- History of cold sores or prior ocular herpes, or facial vesicles in a dermatomal distribution.
Examination
- Best corrected visual acuity (with pinhole if glasses are unavailable).
- Inspect lids, conjunctiva, sclera, and cornea; fluorescein staining if corneal involvement is possible — look specifically for a dendritic pattern suggesting herpes simplex.
- Palpate for preauricular lymphadenopathy.
- Examine the periorbital skin and, for suspected zoster, the full V1 dermatome and nose tip (Hutchinson's sign).
Treatment Targets
- Preserve eyesight and prevent structural (corneal) damage.
- Limit spread of infection to others.
- Provide symptomatic relief.
Choose Initial Treatment
1st line, adenoviral conjunctivitis supportive care only — cold compresses and ocular lubricants.
No antiviral or antibiotic is indicated for typical adenoviral conjunctivitis — antibiotics do not treat a virus, and no antiviral has proven benefit for adenoviral conjunctivitis specifically.[3]
Herpes simplex/zoster ocular involvement requires systemic antiviral treatment (not the adenoviral supportive-care approach) and ophthalmology co-management — this is a fundamentally different disease process from typical viral conjunctivitis, even though it can present with a red, watery eye.
Do not use ophthalmic corticosteroids or antibiotic/corticosteroid combinations — may worsen undiagnosed herpetic keratitis, a serious and largely avoidable error.
Non-Pharmacologic Treatment
- Fastidious hand hygiene and avoiding eye touching — the single most effective way to limit spread.
- Use separate towels and pillowcases; avoid sharing eye makeup or contact lens supplies.
- Stay home from school/work for 3-7 days, or until discharge resolves, given high contagiousness in the first week.
- Cold compresses for comfort, applied as needed.
- Stop wearing contact lenses until fully resolved.
- Discard any eye makeup or contact lens solution used during the infection, given the risk of surface contamination and re-inoculation.
Special Populations
Pregnancy/breastfeeding
Cold compresses and lubricants have no systemic exposure concern. Oral acyclovir/valacyclovir for ocular herpetic disease should be discussed with the prescriber managing the pregnancy, but are generally considered reasonably safe when clinically indicated.
Immunocompromised patients
Have a lower threshold to consider herpetic or other atypical causes, and to involve ophthalmology, given a higher risk of severe or vision-threatening disease.
Children
Adenoviral conjunctivitis is common in children and spreads readily in daycare/school settings — reinforce hand hygiene and exclusion from school per local public health guidance until discharge resolves.
Monitoring & Follow-Up
If there is no improvement after 3-5 days, or if pain/photophobia develops (suggesting corneal involvement, which can follow adenoviral conjunctivitis in a minority of cases), refer to an ophthalmologist. Chronic unilateral redness should prompt reconsideration of the diagnosis rather than continued observation.
Common Errors to Avoid
- Prescribing a topical antibiotic for viral conjunctivitis — does not treat a virus and does not prevent secondary bacterial infection in typical cases.
- Using an ophthalmic corticosteroid or antibiotic/corticosteroid combination without specialist supervision — can worsen undiagnosed herpetic keratitis.
- Missing herpes simplex or herpes zoster ocular involvement by treating every watery red eye as typical adenoviral conjunctivitis.
- Missing a red-eye mimic (angle-closure glaucoma, iritis, scleritis, keratitis) by assuming every red eye is conjunctivitis.
- Overusing ophthalmic vasoconstrictors/decongestants — causes rebound hyperemia and tachyphylaxis; limit to occasional, short-term use (≤3-4 times per month, ≤3 days in a row).
- Underestimating contagiousness — not counselling on hand hygiene and exclusion from school/work during the infectious period.
Clinical Decision Algorithm
Drug Tables
How to use this table: Doses are adult doses and require patient-specific confirmation (renal/hepatic function, weight, allergy history). Pediatric dosing is weight-based per the current product monograph unless stated. Drug pricing is intentionally omitted. Select any drug name to open its complete Pharmasist Drug Database page.
Systemic antivirals — herpes simplex/zoster ocular involvement only
Manage jointly with ophthalmology.
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Acyclovir | Herpes zoster: 800 mg PO 5 times/day for 7 days Herpes simplex: 400 mg PO 5 times/day for 7-14 days | GI upset (uncommon); well tolerated | |
| Famciclovir | Herpes zoster: 500 mg PO TID for 7 days Herpes simplex: 250 mg PO TID for 7 days | GI upset (uncommon); well tolerated | |
| Valacyclovir | Herpes zoster: 1 g PO TID for 7 days Herpes simplex: 500 mg PO TID for 7 days | GI upset (uncommon); well tolerated |
Ophthalmic vasoconstrictors/decongestants
Occasional, short-term use only (≤3-4 times/month, ≤3 days in a row) — overuse causes rebound hyperemia and tachyphylaxis.
| Drug | Dosage | Adverse effects | Comments |
|---|---|---|---|
| Naphazoline | All ages: 1-2 drops Q3-4H PRN for 3-4 days | Minor stinging; pupillary dilation and angle-closure glaucoma risk in predisposed patients | For redness/edema in viral conjunctivitis, or minor irritation. |
| Brimonidine 0.025% | All ages: 1 drop Q6-8H PRN, maximum 4 times/day | Pain on instillation | Does not appear to cause significant rebound hyperemia or tachyphylaxis based on limited evidence. |
| Phenylephrine ophthalmic | All ages: 1-2 drops QID PRN for up to 3 days | Minor stinging; pupillary dilation and angle-closure glaucoma risk in predisposed patients | |
| Tetrahydrozoline | All ages: 1-2 drops BID-QID | Minor stinging; pupillary dilation and angle-closure glaucoma risk in predisposed patients |
References
- Conjunctivitis: a systematic review of diagnosis and treatment — JAMA (Azari AA, Barney NP). JAMA 2013;310(16):1721-1729
- Bedside diagnosis of the 'red eye': a systematic review — American Journal of Medicine (Narayana S, McGee S). Am J Med 2015;128(11):1220-1224
- Adenoviral keratoconjunctivitis — Survey of Ophthalmology (Jhanji V, Chan TC, Li EY, et al.). Surv Ophthalmol 2015;60(5):435-443
- Low-dose brimonidine for relief of ocular redness: integrated analysis of four clinical trials — Clinical and Experimental Optometry (Ackerman SL, Torkildsen GL, McLaurin E, et al.). Clin Exp Optom 2019;102(2):131-139
- Conjunctivitis Preferred Practice Pattern — American Academy of Ophthalmology (Hoskins Center for Quality Eye Care, PPP Cornea/External Disease Committee). 2023 update, published 2024
Professional reference only. Apply clinical judgment and verify patient-specific decisions against current authoritative guidance and product information.